Brain Aneurysm Understanding Critical Medical Insights
Table of Contents
- Medical Overview of Brain Aneurysms
- Anatomical and Physiological Definition of Brain Aneurysms
- Vascular Regions Prone to Aneurysm Formation
- Comparative Analysis: Ruptured vs. Unruptured Aneurysms
- Hemodynamic Stress and Endothelial Dysfunction in Aneurysm Formation
- Diagnostic Procedures and Tools for Brain Aneurysms
- Imaging Modalities in Brain Aneurysm Diagnosis
- Cerebrospinal Fluid Analysis in Subarachnoid Hemorrhage
- Pre-Procedural Preparations for Cerebral Angiography
- Surgical and Endovascular Interventions for Brain Aneurysm Treatment
- Comparison of Open Surgical Clipping and Endovascular Coiling
- Flow Diversion for Large or Complex Aneurysms
- Decision-Making Flowchart for Treatment Selection
- Post-Procedural Care Protocols
- Complications and Long-Term Outcomes in Brain Aneurysm Treatment
- Immediate and Delayed Complications of Aneurysm Treatment
- Functional Outcomes Stratified by Aneurysm Status and Treatment Modality
- Medical Therapies for Vasospasm Prevention: Comparative Efficacy
- Preventive Strategies and Risk Management in Brain Aneurysms
- Modifiable Risk Factors and Evidence-Based Mitigation Strategies
- Patient Education Infographic: Lifestyle Modifications to Reduce Aneurysm Progression
- Protect Your Brain: Lifestyle Strategies for Aneurysm Risk Reduction
- Control Blood Pressure
- Quit Smoking
- Exercise Regularly
- Eat a Heart-Healthy Diet
- Your 5-Step Plan
A brain aneurysm represents a critical vascular abnormality where localized dilation weakens arterial walls, posing severe risks of rupture and life-threatening complications. This condition primarily arises from hemodynamic stress, endothelial dysfunction, and congenital or acquired vulnerabilities in high-flow regions such as the Circle of Willis. With rupture rates ranging from 0.5% to 5% annually, early detection through advanced imaging and precise intervention remains pivotal in mitigating mortality and neurological deficits.
The interplay between anatomical predispositions, genetic factors, and lifestyle influences underscores the complexity of aneurysm management. From diagnostic modalities like CT angiography to minimally invasive endovascular techniques, modern medicine offers tailored approaches to stabilize or repair affected vessels. However, challenges persist in balancing treatment urgency with patient-specific risks, particularly in elderly or comorbid populations. This discussion explores the pathophysiological mechanisms, diagnostic protocols, therapeutic strategies, and long-term outcomes shaping contemporary aneurysm care.
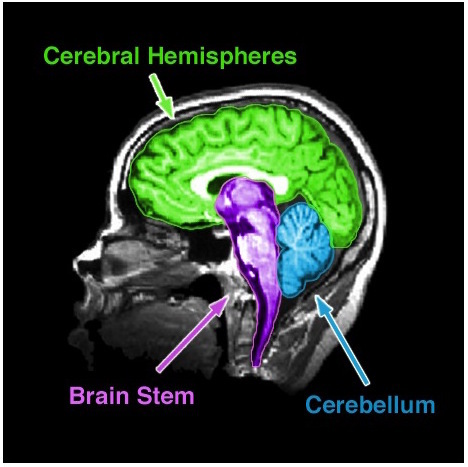
Medical Overview of Brain Aneurysms
Brain aneurysms represent focal dilations or outpouchings of cerebral arteries, arising from structural weaknesses in the arterial wall. These abnormalities occur due to a combination of genetic predispositions, hemodynamic forces, and degenerative changes in the vascular endothelium. The clinical significance lies in their potential to rupture, leading to subarachnoid hemorrhage (SAH), a condition with high morbidity and mortality. Understanding their anatomical variations, predilection sites, and underlying pathophysiological mechanisms is critical for accurate diagnosis, risk stratification, and therapeutic intervention.Anatomical and Physiological Definition of Brain Aneurysms
Brain aneurysms are classified based on their morphological characteristics, which influence their natural history and management strategies. The primary classifications include:The arterial wall in aneurysms exhibits three primary layers: the tunica intima (endothelial lining), tunica media (smooth muscle and elastic fibers), and tunica adventitia (fibrous connective tissue). Weaknesses in the tunica media, particularly at sites of high hemodynamic stress, predispose to aneurysm formation.
Vascular Regions Prone to Aneurysm Formation
The Circle of Willis, a polygonal arterial anastomosis at the base of the brain, is the most frequent site for aneurysm development due to its complex geometry and branching patterns. Key locations include:Anatomical variations, such as a hypoplastic A1 segment of the anterior cerebral artery (ACA), can alter blood flow distribution, increasing stress on compensatory arteries (e.g., AComA). Additionally, atherosclerotic plaques in the ICA or vertebral arteries may contribute to aneurysm formation via chronic endothelial damage.
Comparative Analysis: Ruptured vs. Unruptured Aneurysms
The clinical presentation and management priorities differ significantly between ruptured and unruptured aneurysms. Below is a comparative table summarizing key distinctions:| Feature | Unruptured Aneurysm | Ruptured Aneurysm |
|---|---|---|
| Symptoms |
|
|
| Diagnostic Imaging |
|
|
| Mortality Rates |
|
|
| Treatment Urgency |
|
|
Hemodynamic Stress and Endothelial Dysfunction in Aneurysm Formation
The development of brain aneurysms is driven by abnormal blood flow dynamics and endothelial dysfunction, leading to progressive arterial wall degradation. The following steps outline the pathophysiological process:1. Altered Hemodynamics at Bifurcations
2. Endothelial Activation and Inflammation
3. Smooth Muscle Cell
Diagnostic Procedures and Tools for Brain Aneurysms
Accurate diagnosis of brain aneurysms relies on advanced imaging modalities capable of visualizing vascular abnormalities with high precision. These tools enable clinicians to classify aneurysm morphology, assess rupture risk, and guide therapeutic interventions. The selection of diagnostic techniques depends on clinical presentation, suspected aneurysm location, and availability of specialized equipment. Below, the role of key imaging modalities—including their advantages, limitations, and interpretive criteria—is detailed, alongside standardized classification systems and procedural protocols for cerebrospinal fluid (CSF) analysis.Imaging Modalities in Brain Aneurysm Diagnosis
Computed Tomography Angiography (CTA)CTA is the first-line imaging modality for suspected aneurysms due to its widespread availability, rapid acquisition, and high sensitivity for detecting intracranial vascular abnormalities. This technique involves the intravenous administration of iodinated contrast followed by helical CT scanning, generating three-dimensional reconstructions of cerebral arteries. CTA excels in identifying aneurysms ≥3 mm in diameter, with a reported sensitivity of 95–98% for detecting ruptured aneurysms in subarachnoid hemorrhage (SAH) cases. However, its spatial resolution (typically 0.5–1 mm) may underestimate smaller aneurysms or those in complex anatomical regions (e.g., posterior circulation). Artifacts from dense bone structures or contrast extravasation can also obscure fine details.
Magnetic Resonance Angiography (MRA)
MRA provides superior soft-tissue contrast and avoids ionizing radiation, making it ideal for patients with renal impairment or contrast allergies. Time-of-flight (TOF) and contrast-enhanced MRA (CE-MRA) are commonly used, with CE-MRA offering higher sensitivity (approaching 90–95%) for aneurysms ≥5 mm. Limitations include longer scan times, susceptibility to motion artifacts, and lower resolution compared to CTA (voxel sizes typically 0.6–1.2 mm). MRA is particularly useful for follow-up imaging in patients with contraindications to CT or contrast agents.
Digital Subtraction Angiography (DSA)
Considered the gold standard for aneurysm diagnosis, DSA offers unparalleled spatial resolution (<0.1 mm) and is the definitive modality for pre-surgical planning. It involves catheter-based injection of contrast into cerebral arteries, with real-time fluoroscopic imaging to visualize blood flow dynamics. DSA can detect aneurysms as small as 1–2 mm and assess associated vascular pathologies (e.g., stenosis, arteriovenous malformations). However, it is invasive, carries risks of thromboembolic events (0.5–2% complication rate), and requires specialized interventional radiology facilities. DSA is reserved for complex cases or when endovascular treatment is planned.
Interpretation of Radiographic Findings
Clinicians classify aneurysms based on morphological features visible in imaging studies. The "berry aneurysm"—the most common type—appears as a saccular outpouching with a narrow neck, typically arising from arterial bifurcations (e.g., anterior communicating artery). Size thresholds are critical: aneurysms <5 mm are considered small, 5–12 mm medium, 13–25 mm large, and >25 mm giant. The Hunt-Hess scale (for SAH grading) and Fisher scale (for detecting blood in CSF) are used to stratify severity:
Cerebrospinal Fluid Analysis in Subarachnoid Hemorrhage
In patients with suspected SAH but non-diagnostic CT scans, lumbar puncture (LP) remains essential for detecting xanthochromia (yellow CSF due to hemoglobin breakdown) or red blood cells (RBCs). The procedure must be performed with caution to avoid herniation in cases of mass effect. Below are the standardized steps, contraindications, and CSF analysis criteria:Lumbar Puncture Procedural Steps for SAH Evaluation
1. Preparation: Position the patient laterally with knees flexed to the chest (fetal position). Sterilize the L3–L4 or L4–L5 interspace using antiseptic solution.
2. Needle Insertion: Advance a 20–22-gauge spinal needle at a 10–15° angle until CSF flow is confirmed (typically 3–5 cm depth).
3. Sample Collection: Collect 4 tubes (1 mL each) for:
Tube 1: RBC count (trauma vs. true SAH; >1,000 RBCs/mm³ suggests SAH). Tube 2–4: Centrifugation to detect xanthochromia (visible after 12–24 hours if bilirubin or oxyhemoglobin is present). 4. Contraindications: Absolute (e.g., increased intracranial pressure, coagulopathy) or relative (e.g., sepsis, spinal surgery history).
5. CSF Analysis:
RBCs: Gradual decline across tubes (e.g., Tube 1: 10,000/mm³; Tube 4: 1,000/mm³) suggests traumatic tap. Xanthochromia: Confirms SAH if present in tubes 2–4 (spectrophotometry can quantify bilirubin at 415 nm). Biochemistry: Elevated protein (>150 mg/dL) and normal glucose (unless infection is present).
Pre-Procedural Preparations for Cerebral Angiography
Cerebral angiography requires meticulous preparation to minimize complications and optimize image quality. Below is a checklist of critical steps, categorized by patient, equipment, and monitoring requirements:Pre-Procedural Checklist for Cerebral AngiographyTable: Comparative Summary of Imaging Modalities
Patient Preparation
Fasting: NPO for ≥6 hours to reduce aspiration risk. Medication Review: Discontinue antiplatelets (e.g., clopidogrel) 5–7 days pre-procedure; resume post-DSA if no intervention. Allergy Assessment: Confirm iodine/contrast allergy status; pre-treat with steroids/antihistamines if necessary. Hydration: Intravenous fluids (0.9% NaCl) to reduce contrast-induced nephropathy risk. Equipment and Contrast Protocols
Catheter Selection: Use a 5–6 French diagnostic catheter (e.g., Simmons, Verdant) for selective arterial access. Contrast Agent: Low-osmolar agents (e.g., iohexol) preferred; total dose ≤200 mL to limit nephrotoxicity. Imaging Parameters: Frame rates of 2–4 frames/sec with roadmap guidance for precision. Real-Time Monitoring
Vital Signs: Continuous ECG, blood pressure (target SBP <180 mmHg), and pulse oximetry. Neurological Checks: Pre- and post-procedure Glasgow Coma Scale (GCS) assessments. Complication Alerts: Immediate intervention for signs of thromboembolism (e.g., focal deficits) or contrast extravasation.
| Modality | Sensitivity (%) | Resolution | Advantages | Limitations |
|---|---|---|---|---|
| CTA | 95–98 (SAH) | 0.5–1 mm | Fast, high sensitivity for rupture | Radiation, contrast nephrotoxicity risk |
| MRA | 90–95 (≥5 mm) | 0.6–1.2 mm | No radiation, ideal for follow-up | Lower resolution, motion artifacts |
| DSA | Near 100% | <0.1 mm | Gold standard for treatment planning | Invasive, thromboembolic risk |

Surgical and Endovascular Interventions for Brain Aneurysm Treatment
The management of brain aneurysms has evolved significantly with advancements in neurosurgical and endovascular techniques, each offering distinct advantages based on aneurysm morphology, patient anatomy, and clinical risk factors. Traditional open surgical clipping remains the gold standard for select cases, while endovascular coiling has become the preferred modality for many ruptured and unruptured aneurysms due to its minimally invasive nature. Flow diversion represents an emerging paradigm for complex or large aneurysms, leveraging stent-based technologies to induce thrombosis while preserving parent artery patency. Treatment selection requires a multidisciplinary approach, integrating imaging data, procedural risks, and patient-specific comorbidities to optimize outcomes.Comparison of Open Surgical Clipping and Endovascular Coiling
Technical Steps and Procedural MechanicsOpen surgical clipping involves a craniotomy to expose the aneurysm, followed by the placement of a titanium clip across its neck to isolate it from the circulation. The procedure requires precise anatomical dissection to avoid neurovascular injury, with intraoperative neurophysiological monitoring (e.g., motor evoked potentials) to assess real-time functional integrity. In contrast, endovascular coiling is performed under fluoroscopic guidance via femoral artery access, with a microcatheter navigated to the aneurysm sac. Detachable coils are deployed to promote thrombosis, with adjunctive techniques (e.g., balloon remodeling, stent assistance) employed for wide-necked aneurysms to improve coil packing density.
Recovery Timelines and Hospitalization
Post-clipping patients typically require 5–7 days of hospitalization, with ICU monitoring for 24–48 hours to detect complications such as vasospasm, hydrocephalus, or delayed ischemia. Rehabilitation may extend for weeks, particularly if craniotomy-related swelling or neurological deficits occur. Endovascular coiling reduces hospitalization to 2–4 days, with ICU observation limited to high-risk cases (e.g., posterior circulation aneurysms or antiplatelet bridging). Early ambulation and discharge planning are prioritized, though follow-up imaging (e.g., MRA or CTA at 6–12 months) is mandatory to assess coil compaction or recanalization.
Complication Profiles
Clipping carries risks of surgical site infection (0.5–2%), cerebrospinal fluid (CSF) leak (1–5%), and cranial nerve palsies (e.g., III, IV, or VI nerve injury in 1–3% of cases). Endovascular coiling is associated with thromboembolic events (3–5%), coil protrusion (1–2%), and procedural rupture (1–3%), though the overall morbidity is lower for suitable aneurysms. Rupture-related subarachnoid hemorrhage (SAH) complicates ~20% of clipping procedures versus ~5% for coiling, with mortality rates of 10–15% versus 5–10%, respectively, in contemporary series.
Flow Diversion for Large or Complex Aneurysms
Materials and TechniquesFlow diversion utilizes low-porosity stent systems (e.g., Pipeline Embolization Device (PED), Silk, or FRED) to reconstruct the aneurysm sac by altering hemodynamics, promoting endothelialization, and inducing thrombosis. The PED, composed of a nitinol mesh with a porosity of 35%, is deployed across the aneurysm neck via a microcatheter, with antiplatelet therapy (dual antiplatelet aggregation [DAPT] for 6 months) to prevent in-stent thrombosis. For fusiform or dissecting aneurysms, multiple overlapping stents may be required to achieve complete coverage.
Device Deployment Mechanics
1. Pre-procedural Planning: High-resolution imaging (e.g., 3D rotational angiography) maps the aneurysm geometry, parent artery diameter, and branching vessels to select stent length and diameter (typically 1:1 to parent artery, with 2–3 mm overlap).
2. Catheter Navigation: A microcatheter (e.g., Headway 17 or Prowler Select Plus) is advanced through a guiding catheter (e.g., Neuroform 3) to the aneurysm origin, with roadmapping to confirm positioning.
3. Stent Deployment: The PED is deployed in a "push-and-hold" technique, with proximal anchoring in the parent artery and distal extension into the aneurysm dome. Post-deployment angiography assesses stent apposition and parent artery patency.
4. Adjunctive Coiling: In cases of incomplete flow diversion (e.g., wide-necked aneurysms), coils may be placed within the stent mesh to accelerate thrombosis.
Clinical Outcomes and Limitations
Flow diversion achieves occlusion rates of 70–90% at 12 months for large/giant aneurysms, with parent artery preservation in >95% of cases. However, complications include delayed rupture (0.5–2%), thromboembolic events (5–10%), and in-stent stenosis (1–3%). Patient selection excludes aneurysms with unfavorable neck geometry (e.g., acute angles) or high-flow collateral vessels that may predispose to parent artery occlusion.
Decision-Making Flowchart for Treatment Selection
The following flowchart integrates aneurysm characteristics, patient comorbidities, and procedural risks to guide therapeutic decision-making:-
Step 1: Aneurysm Morphology and Location
- Ruptured aneurysms (<5 mm): Endovascular coiling (first-line) unless wide-necked (>4 mm) or posterior circulation (consider stent assistance).
- Ruptured aneurysms (>10 mm or fusiform): Flow diversion or surgical clipping based on anatomy and surgeon expertise.
- Unruptured aneurysms (<7 mm): Conservative management unless symptomatic or high-risk features (e.g., posterior circulation, growth on follow-up).
- Unruptured aneurysms (>10 mm or giant): Flow diversion preferred; clipping reserved for complex geometries.
-
Step 2: Patient Comorbidities and Functional Status
- ASA III–IV or severe cardiopulmonary disease: Endovascular favored due to lower perioperative risk.
- Antiplatelet/anticoagulant use: Flow diversion contraindicated; coiling with temporary antiplatelet interruption may be considered.
- Poor neurological baseline (mRS ≥3): Conservative management unless life-threatening risk (e.g., imminent rupture).
-
Step 3: Procedural Feasibility and Expertise
- Wide-necked aneurysms (>4 mm): Stent-assisted coiling or flow diversion if endovascular access is feasible.
- Posterior circulation aneurysms: Clipping preferred for basilar tip aneurysms; coiling for vertebral or PICA aneurysms.
- Complex geometries (e.g., dissecting, mycotic): Multidisciplinary consensus required; flow diversion or surgical bypass may be necessary.
-
Step 4: Shared Decision-Making and Patient Preference
- Discuss procedural risks, recovery timelines, and long-term outcomes (e.g., recanalization rates for coiling vs. stent-related complications).
- Document informed consent, including alternatives (e.g., observation for low-risk unruptured aneurysms).
Post-Procedural Care Protocols
Neurocritical Monitoring ParametersPatients undergoing clipping or coiling require standardized monitoring to detect complications, with protocols tailored to the procedure type:
| Parameter | Clipping | Coiling | Flow Diversion | ||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ICU Stay Duration | 24–48 hours (extended for SAH or hydrocephalus) | 12–24 hours (unless thromboembolic event) | 24–48 hours (DAPT initiation monitoring) | ||||||||||||||||||||||||||||||||||||||||
| ICP Monitoring | Indicated for SAH (target <20 mmHg; consider external ventricular drain if elevated) | Reserved for delayed cerebral ischemia or rebleeding | Monitor for vasospasm (TCD or CTA if symptoms arise) | ||||||||||||||||||||||||||||||||||||||||
| GCS Trends | Hourly assessment; decline suggests hematoma, ischemia, or vasospasm | Q4h assessment; focal deficits may indicate thromboembolism | Q2h assessment; delayed neurological decline may indicate in-stent thrombosis | ||||||||||||||||||||||||||||||||||||||||
| Antiplatelet/Anticoagulation | None (unless pre-existing) | Dual antiplatelet therapy (DAPT) if stent-assisted; otherwise, aspirin for 3–6 months | DAPT for 6 months; transition to aspirin monotherapy | ||||||||||||||||||||||||||||||||||||||||
| Imaging Follow-Up | CT/CTA at 24Complications and Long-Term Outcomes in Brain Aneurysm TreatmentBrain aneurysm treatment, whether surgical or endovascular, carries a spectrum of immediate and delayed complications that significantly influence patient recovery and long-term functional status. Ruptured aneurysms introduce additional risks, including secondary brain injury from subarachnoid hemorrhage (SAH), while unruptured aneurysms may still pose challenges related to treatment invasiveness. Understanding these complications—ranging from neurovascular sequelae like vasospasm to cognitive and psychological sequelae—is critical for optimizing clinical management and patient counseling. This section examines pathophysiological mechanisms, statistical outcomes, and comparative efficacy of medical interventions, alongside the broader impact on quality of life.Immediate and Delayed Complications of Aneurysm TreatmentPathophysiological Mechanisms of Post-Treatment ComplicationsThe treatment of brain aneurysms, particularly after rupture, triggers a cascade of secondary injuries that can persist or emerge over time. Key mechanisms include: - Vasospasm: A delayed but severe complication following SAH, characterized by arterial narrowing due to smooth muscle contraction and endothelial dysfunction. The release of hemoglobin breakdown products (e.g., oxyhemoglobin, bilirubin) and inflammatory cytokines (e.g., interleukin-6, tumor necrosis factor-α) disrupts nitric oxide-mediated vasodilation, leading to cerebral ischemia. Statistical Incidence of Complications Functional Outcomes Stratified by Aneurysm Status and Treatment ModalityLong-term functional recovery is assessed using the modified Rankin Scale (mRS), where scores range from 0 (no disability) to 6 (death). Outcomes differ markedly between ruptured and unruptured aneurysms, as well as by age and treatment approach.Key Observations from Large-Scale Studies - Ruptured Aneurysms: Responsive Table: Functional Outcomes by Age and Treatment
Medical Therapies for Vasospasm Prevention: Comparative EfficacyPharmacological prophylaxis of vasospasm remains a cornerstone of SAH management, though evidence for efficacy varies. The Triple-H Therapy (hypertension, hypervolemia, hemodilution) is standard, while nimodipine and magnesium sulfate have undergone rigorous evaluation.Mechanisms of Action Preventive Strategies and Risk Management in Brain AneurysmsBrain aneurysms represent a significant global health burden, with rupture accounting for approximately 5% of all strokes and carrying a mortality rate exceeding 40% in acute cases. While not all aneurysms are preventable, targeted interventions addressing modifiable risk factors—such as hypertension, smoking, and genetic predispositions—can substantially reduce progression, rupture risk, and long-term morbidity. This section synthesizes evidence-based strategies for primary and secondary prevention, patient education frameworks, and structured clinical workflows to optimize risk management in high-risk populations.Modifiable Risk Factors and Evidence-Based Mitigation StrategiesThe majority of brain aneurysms develop due to a combination of hemodynamic stress, vascular wall degeneration, and systemic risk factors. Among these, hypertension, smoking, and polycystic kidney disease (PKD) are the most strongly associated with aneurysm formation and rupture. Interventions targeting these factors have demonstrated clinically significant reductions in aneurysm growth rates and rupture risk in observational and interventional studies."A 10-mmHg reduction in systolic blood pressure is associated with a 20% decrease in aneurysm rupture risk over 5 years, independent of other cardiovascular risk factors." — International Study of Unruptured Intracranial Aneurysms (ISUIA), 2003Key modifiable risk factors and interventions:
Patient Education Infographic: Lifestyle Modifications to Reduce Aneurysm ProgressionA visual infographic for patient education should combine text, icons, and actionable steps to enhance engagement. Below is a structured description for HTML implementation, including `` and ` Protect Your Brain: Lifestyle Strategies for Aneurysm Risk Reduction  Control Blood PressureTarget: <130/80 mmHg. Monitor daily with a home device.  Quit SmokingUse patches, gum, or counseling. Avoid secondhand smoke.  Exercise Regularly150 mins/week of moderate activity (e.g., brisk walking).  Eat a Heart-Healthy DietMediterranean diet: fish, nuts, olive oil, low salt. Your 5-Step Plan |
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.