What Is A Brain Aneurysm Explained Clearly

Published

Table of Contents

A brain aneurysm represents a critical yet often misunderstood vascular condition where weakened arterial walls bulge due to sustained blood pressure, posing a silent yet severe threat to neurological health. This pathological dilation occurs predominantly at high-pressure junctions, such as the Circle of Willis, where structural vulnerabilities—ranging from congenital defects to degenerative collagen loss—compromise vessel integrity. Unlike transient vascular fluctuations, aneurysms progress insidiously, demanding early recognition to prevent catastrophic rupture, which triggers subarachnoid hemorrhage with mortality rates exceeding 50% in untreated cases. Understanding their anatomical formation, risk stratification, and diagnostic nuances is essential for clinicians and patients alike to mitigate progression and optimize intervention timelines.

The interplay between biomechanical stress and genetic predispositions further complicates aneurysm development, with hypertension acting as a primary accelerator by degrading elastin fibers and expanding arterial diameters over time. Emerging research also highlights lesser-discussed triggers, including substance-induced vasospasm or connective tissue disorders, which amplify rupture risks in otherwise asymptomatic individuals. By dissecting these mechanisms—from molecular degradation to large-scale vascular remodeling—this analysis bridges anatomical precision with clinical relevance, equipping readers to distinguish high-risk presentations from benign findings.
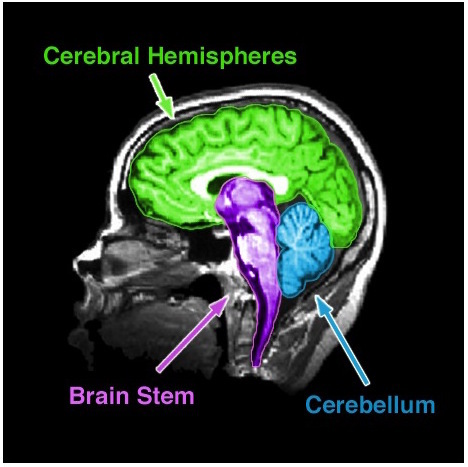
What Is A Brain Aneurysm

Definition and Basic Anatomy of a Brain Aneurysm

A brain aneurysm represents a localized dilation or bulging of a weakened arterial wall within the cerebral vasculature, typically resulting from structural compromise due to chronic hypertension, congenital defects, or degenerative changes in the vessel wall. These abnormalities primarily develop at branching points of major cerebral arteries, where hemodynamic stress is highest, often within the Circle of Willis, a critical arterial ring supplying blood to the brain. Understanding their anatomical formation, classification, and pathological distinctions from other vascular anomalies is essential for accurate diagnosis and management.

Anatomical Structure and Formation of a Brain Aneurysm

The formation of a brain aneurysm begins with degenerative weakening of the arterial wall, particularly in the tunica media (middle layer), where structural proteins such as collagen and elastin degrade due to chronic hypertension, genetic predispositions, or inflammatory processes. This degradation reduces the vessel’s ability to withstand pulsatile blood pressure, leading to progressive dilation. The intima (inner layer) may also exhibit endothelial dysfunction, further compromising integrity. Over time, the vessel wall thins and balloons outward, forming a sac-like structure filled with arterial blood under high pressure.

The Circle of Willis, a polygonal arterial network at the base of the brain, is a common site for aneurysm development due to its complex branching and high-flow dynamics. Key arteries involved include the anterior communicating artery (AComA), posterior communicating artery (PComA), and middle cerebral artery (MCA) bifurcations. The bulging aneurysm may remain asymptomatic for years but risks rupture if the weakened wall fails under sustained pressure, leading to subarachnoid hemorrhage (SAH), a life-threatening neurological emergency.

Types of Brain Aneurysms and Their Pathophysiological Features

Brain aneurysms are classified based on morphological characteristics, causative factors, and anatomical involvement. The three primary types—saccular, fusiform, and dissecting—differ in structure, etiology, and clinical implications. Below is a comparative analysis:
Type Description Causes Risk Factors Common Symptoms (Pre-Rupture)
Saccular (Berry Aneurysm) A small, spherical outpouching resembling a berry, typically arising from a single arterial wall defect. Accounts for ~90% of intracranial aneurysms. Degenerative weakening of the arterial wall (e.g., collagen/elastin fragmentation), congenital vascular malformations, or trauma. Hypertension, smoking, polycystic kidney disease, family history, connective tissue disorders (e.g., Ehlers-Danlos syndrome). Often asymptomatic; if symptomatic, may present with thunderclap headache, cranial nerve palsies (e.g., CN III compression), or focal neurological deficits.
Fusiform A symmetrical, spindle-shaped dilation affecting the entire circumference of the artery, often involving the basilar artery or vertebral arteries. Chronic hypertension, atherosclerosis, or fibromuscular dysplasia leading to diffuse arterial wall degeneration. Advanced age, long-standing hypertension, genetic predisposition (e.g., Marfan syndrome). Progressive symptoms include brainstem compression (e.g., ataxia, dysphagia), ischemic strokes due to luminal narrowing, or mass effect.
Dissecting An intramural tear in the arterial wall creates a false lumen, separating the intima from the media. Often involves the vertebrobasilar system or carotid arteries. Trauma, spontaneous dissection (e.g., due to cystic medial necrosis), or connective tissue disorders. Young to middle-aged adults, genetic disorders (e.g., Loeys-Dietz syndrome), or prior arterial manipulation (e.g., angiography). Sudden excruciating headache, Horner’s syndrome (ptosis, miosis, anhidrosis), or ischemic deficits from compromised blood flow.

Differentiating Brain Aneurysms from Other Vascular Abnormalities

Brain aneurysms must be distinguished from other cerebrovascular pathologies, as their management strategies and prognostic implications differ significantly. Key distinctions include:

- Arteriovenous Malformations (AVMs):

  • Pathology: Congenital tangles of abnormal arteries and veins without intervening capillaries, leading to high-flow shunting and vascular steal phenomena.
  • Progression: AVMs enlarge over time due to recruitment of feeder vessels and hemodynamic stress, whereas aneurysms result from localized wall weakness.
  • Symptoms: AVMs present with epilepsy, focal deficits, or hemorrhage, but their associated aneurysms (e.g., "flow-related" aneurysms) may develop secondary to altered hemodynamics.
  • - Cerebral Arterial Stenosis:

  • Pathology: Narrowing of arterial lumens due to atherosclerosis, vasculitis, or fibromuscular dysplasia, reducing blood flow without wall dilation.
  • Progression: Stenosis progresses via plaque buildup or intimal hyperplasia, whereas aneurysms involve wall thinning and bulging due to pressure.
  • Symptoms: Stenosis causes transient ischemic attacks (TIAs) or strokes from hypoperfusion, while aneurysms risk rupture and SAH.
  • - Cavernous Malformations (Cavernous Hemangiomas):

  • Pathology: Clusters of abnormal, thin-walled blood vessels separated by fibrous septa, lacking intervening brain parenchyma.
  • Progression: These lesions grow slowly and may calcify or hemorrhage, but they lack the sac-like dilation characteristic of aneurysms.
  • Symptoms: Seizures or focal deficits due to mass effect, but not typically associated with sudden rupture.
  • Brain aneurysms uniquely involve localized arterial wall weakness and bulging, distinct from the high-flow shunts of AVMs, luminal narrowing of stenosis, or multilobular clusters of cavernous malformations. Their rupture carries a high mortality rate (~50% without treatment), emphasizing the need for early detection via imaging modalities such as CT angiography (CTA), MR angiography (MRA), or digital subtraction angiography (DSA).

    Mechanisms of Aneurysm Rupture and Clinical Consequences

    The rupture of a brain aneurysm occurs when the degraded arterial wall can no longer withstand systemic blood pressure, leading to subarachnoid hemorrhage (SAH). Key factors contributing to rupture include:
  • Wall Thinning: Progressive loss of collagen and elastin fibers reduces tensile strength.
  • Hemodynamic Stress: High-flow regions (e.g., bifurcations) experience turbulence and shear stress, accelerating degeneration.
  • Inflammatory Mediators: Matrix metalloproteinases (MMPs) and cytokines further degrade extracellular matrix components.
  • Upon rupture, blood enters the subarachnoid space, triggering:

  • Vasospasm: Narrowing of adjacent arteries due to oxhemoglobin toxicity, increasing ischemic risk.
  • Increased Intracranial Pressure (ICP): Compression of brain tissue, leading to hydrocephalus or cerebral edema.
  • Re-bleeding Risk: Up to 40% of patients experience re-bleeding within 28 days, often fatal.
  • Preventive measures such as blood pressure control, smoking cessation, and surgical/endovascular intervention (e.g., clipping, coiling) are critical to mitigate rupture risks in high-risk aneurysms (>7 mm in diameter or growing >1 mm/year).
    What Is A Brain Aneurysm - Ilustrasi 2

    Causes and Risk Factors of Brain Aneurysms

    Brain aneurysms arise from a complex interplay of genetic predispositions, structural weaknesses in arterial walls, and external factors that exert mechanical or biochemical stress on cerebral vasculature. While some risk factors—such as age or family history—are inherent and non-modifiable, others, including hypertension and smoking, represent critical opportunities for intervention. Understanding these distinctions is essential for both clinical prevention and targeted management strategies. Hypertension, in particular, plays a dominant role by altering the biomechanical integrity of arterial walls, while lesser-known conditions like connective tissue disorders or substance use introduce additional, often overlooked, vulnerabilities.

    The development of brain aneurysms is influenced by a combination of congenital weaknesses, acquired damage, and systemic physiological stressors. These factors interact to weaken arterial walls, leading to localized dilations or ballooning that may eventually rupture. The following sections categorize these influences, emphasizing the distinction between modifiable and non-modifiable risks, while also exploring age-related trends in aneurysm incidence and rupture rates.

    Modifiable and Non-Modifiable Risk Factors

    Brain aneurysms are influenced by both inherent (non-modifiable) and acquired (modifiable) risk factors. Non-modifiable factors include genetic predispositions, age, and pre-existing conditions such as polycystic kidney disease (PKD), while modifiable factors encompass lifestyle choices like smoking, hypertension management, and substance use. The distinction between these categories is critical for clinical guidance, as interventions can effectively mitigate risks associated with modifiable factors.

    Non-modifiable risk factors include:

  • Genetic predisposition: A family history of aneurysms or subarachnoid hemorrhage (SAH) increases risk by up to 5–10 times, suggesting autosomal dominant inheritance patterns in some cases. Mutations in genes such as COL3A1 (associated with Ehlers-Danlos syndrome) or FBN1 (Marfan syndrome) further elevate susceptibility by impairing collagen and elastin synthesis.
  • Age: Incidence rises sharply after 40 years, with peak rupture rates occurring between 55–65 years. However, aneurysms in younger adults (under 40) are often linked to congenital weaknesses or trauma, while elderly patients may present with multiple, smaller aneurysms due to cumulative vascular aging.
  • Gender: Women exhibit a higher lifetime risk of aneurysm rupture, possibly due to hormonal influences (e.g., estrogen’s role in collagen degradation) and longer life expectancy. Postmenopausal women show a 2–3 times greater rupture risk than age-matched men.
  • Ethnicity: Sub-Saharan African and Hispanic populations demonstrate higher prevalence rates, though underlying mechanisms remain poorly understood. Studies suggest potential genetic or environmental contributors, including higher rates of hypertension in these groups.
  • Modifiable risk factors with proven or suspected influence:

  • Hypertension: The most significant modifiable risk factor, accounting for ~60% of aneurysm-related morbidity. Chronic elevation in blood pressure induces shear stress on arterial walls, degrading the internal elastic lamina and disrupting collagen fiber alignment. Over time, this leads to wall thinning and aneurysm formation. Uncontrolled hypertension increases rupture risk by ~50%.
  • Smoking: Tobacco use accelerates aneurysm growth and rupture through nicotine-induced vasoconstriction, endothelial dysfunction, and oxidative stress. Smokers face a 2–4 times higher risk of rupture compared to non-smokers, with dose-dependent effects observed.
  • Alcohol consumption: Heavy or binge drinking correlates with increased aneurysm prevalence, likely via chronic inflammation and impaired vascular repair mechanisms. A study in Stroke (2018) linked >14 drinks/week to a 30% higher risk of aneurysm detection.
  • Illicit drug use: Cocaine and amphetamines trigger acute hypertension and vasospasm, directly stressing arterial walls. Cocaine users exhibit a 4–5 times higher risk of SAH, often in younger patients without prior vascular history.
  • Biomechanical Role of Hypertension in Aneurysm Development

    Hypertension exerts its pathological effects through chronic mechanical stress on cerebral arteries, particularly at sites of congenital weakness. The Law of Laplace governs this relationship, stating that wall tension (T) in a cylindrical vessel is proportional to pressure (P) × radius (r), divided by wall thickness (t):
    T = (P × r) / (2t)
    In aneurysms, the localized dilation increases r, amplifying tension even at normal pressures. Hypertension further exacerbates this by:
  • Disrupting collagen and elastin fibers: Chronic high pressure degrades type III collagen (critical for arterial resilience) and reduces elastin content, weakening the media layer.
  • Promoting medial degeneration: The vasa vasorum (small vessels supplying the arterial wall) becomes compromised, leading to ischemic damage in the tunica media.
  • Inducing inflammatory responses: Hypertension activates matrix metalloproteinases (MMPs), enzymes that break down extracellular matrix proteins, accelerating aneurysm expansion.
  • Clinical correlation: Patients with systolic BP >140 mmHg demonstrate a 3–5 times higher rupture risk than normotensive individuals. Aggressive antihypertensive therapy (targeting <130/80 mmHg) post-aneurysm detection reduces rupture risk by ~50%, though medication selection must balance efficacy with cerebral perfusion risks.

    Lesser-Known Risk Factors and Physiological Mechanisms

    Beyond hypertension and smoking, several conditions and exposures contribute to aneurysm formation through distinct pathophysiological pathways. These factors often remain underdiagnosed but warrant attention due to their high-risk profiles.

    Conditions associated with elevated aneurysm risk:

  • Polycystic kidney disease (PKD): Linked to cerebral aneurysm risk via abnormal connective tissue metabolism and shared genetic pathways (e.g., PKD1 mutations affecting vascular smooth muscle cells). Patients with PKD exhibit a 10% lifetime risk of aneurysm, requiring early screening.
  • Ehlers-Danlos syndrome (EDS): Type IV EDS, caused by COL3A1 mutations, leads to fragile collagen fibers, increasing aneurysm risk by ~100 times. Rupture rates are ~80% by age 40 in untreated cases.
  • Marfan syndrome: FBN1 mutations impair fibrillin-1, a protein stabilizing elastin. Aneurysms in Marfan patients often involve the circle of Willis and carry a 5–10% annual rupture risk without intervention.
  • Fibromuscular dysplasia (FMD): A non-atherosclerotic arterial disease causing segmental wall thickening or thinning. ~20% of FMD patients develop cerebral aneurysms, often in the internal carotid artery.
  • Environmental and behavioral factors:

  • Cocaine and amphetamines: Trigger acute hypertensive crises (BP spikes to >200/120 mmHg), directly stressing aneurysm walls. Case reports document ruptures within minutes of use in previously asymptomatic patients.
  • Oral contraceptives: Combined estrogen-progestin pills increase rupture risk by ~2–3 times, particularly in women with pre-existing aneurysms. The mechanism involves estrogen-induced MMP activation and endothelial dysfunction.
  • Chronic kidney disease (CKD): Uremia and secondary hypertension contribute to vascular calcification and accelerated atherosclerosis, increasing aneurysm prevalence by ~40% in dialysis patients.
  • The incidence and rupture risk of brain aneurysms vary significantly across age groups, reflecting underlying biological and lifestyle differences. Younger adults (<40 years) often present with congenital or traumatic aneurysms, while elderly patients (>65 years) face higher multiple aneurysm burden and comorbidity-related risks.

    Incidence and rupture trends by age group:

    Age Group Incidence Rate (per 100,000) Rupture Risk (%) Key Risk Factors Clinical Presentation
    18–39 years 2–5 5–10% (per year) Genetic predisposition, trauma, cocaine use, PKD Sudden SAH ("worst headache of life"), often no prior symptoms
    40–59 years 9–12 1–3% (per year) Hypertension, smoking, oral contraceptives Subtle symptoms (e.g., cranial nerve palsies) or incidental detection on

    Symptoms and Warning Signs of Brain Aneurysms

    Brain aneurysms often present with a spectrum of symptoms that vary significantly depending on whether the aneurysm remains unruptured or has ruptured. Pre-rupture symptoms, though frequently subtle and nonspecific, may provide critical early warnings, while post-rupture signs are acute, severe, and life-threatening. Understanding these manifestations—rooted in their anatomical and pathophysiological origins—enables timely diagnosis and intervention. Below, the neurological basis of symptoms is explored, followed by a structured progression of warning signs and a location-specific analysis of clinical presentations.

    Pre-Rupture Symptoms and Their Neurological Basis

    Unruptured brain aneurysms may produce symptoms through mass effect, compression of adjacent structures, or vascular steal phenomena. These manifestations are often overlooked due to their similarity to benign conditions, but they can indicate impending rupture or the need for preventive treatment.

    Key mechanisms behind pre-rupture symptoms include:

  • Direct compression: Aneurysms exert pressure on cranial nerves, brain parenchyma, or vascular structures, leading to focal deficits.
  • Vascular steal: Blood flow is diverted from surrounding tissues, causing ischemic symptoms.
  • Inflammatory response: Chronic irritation of meninges or adjacent brain regions may trigger headaches or seizures.
  • Common pre-rupture symptoms and their neurological correlates:

    Subtle, progressive symptoms should prompt further investigation, particularly in patients with risk factors such as hypertension, smoking, or a family history of aneurysms.

    Progression of Warning Signs: Early Signs to Imminent Rupture

    Symptoms escalate as an aneurysm grows or approaches rupture. Below is a flowchart-style table outlining the progression from early warnings to acute rupture indicators, categorized by symptom, possible cause, and urgency level.
    Symptom Possible Cause Urgency Level
    Early Warning Signs (Weeks to Months Before Rupture)
    Persistent, dull headache (often worse in the morning) Chronic meningismus from aneurysm irritation or increased intracranial pressure (ICP) Moderate (requires evaluation if persistent)
    Visual disturbances (e.g., blurred vision, diplopia) Compression of cranial nerve III (oculomotor) or optic pathways (e.g., aneurysm at the posterior communicating artery) Moderate-High (may indicate rapid growth)
    Focal neurological deficits (e.g., hemiparesis, aphasia) Ischemia from vascular steal or mass effect on adjacent brain regions High (suggests critical compression)
    Seizures (new-onset) Irritation of cortical or subcortical structures by the aneurysm High (may precede rupture)
    Late Warning Signs (Days to Hours Before Rupture)
    Sudden, severe "thunderclap" headache (abrupt onset, peak intensity within minutes) Leakage of blood into subarachnoid space (premonitory SAH) or imminent rupture Emergency (requires immediate neuroimaging)
    Nausea/vomiting without preceding symptoms Rise in ICP or brainstem irritation High (often accompanies thunderclap headache)
    Photophobia and neck stiffness Meningeal irritation from blood products or inflammation High (suggests SAH or impending rupture)
    Altered mental status (confusion, lethargy) Hydrocephalus from obstructed CSF flow or cerebral edema Critical (may indicate mass effect or hemorrhage)
    The "thunderclap" headache—defined as an abrupt, excruciating headache reaching maximal intensity within seconds to minutes—is the hallmark of aneurysm rupture or premonitory SAH. Its presence demands urgent neuroimaging (CT angiography or lumbar puncture) to rule out hemorrhage.

    Post-Rupture Symptoms and the Physiological Cascade of Subarachnoid Hemorrhage

    Rupture of a brain aneurysm triggers a rapid, life-threatening cascade culminating in subarachnoid hemorrhage (SAH). Symptoms reflect both the acute bleeding event and secondary complications, including vasospasm, hydrocephalus, and cerebral edema.

    Immediate post-rupture manifestations:

  • Severe, sudden headache: Described as the "worst headache of my life," resulting from meningeal irritation and elevated ICP.
  • Neurological deficits: Focal deficits (e.g., hemiparesis, aphasia) due to compression or ischemia from blood clots or edema.
  • Meningismus: Neck stiffness, photophobia, and irritability from blood in the subarachnoid space.
  • Altered consciousness: Ranging from confusion to coma, depending on the volume of blood and brainstem involvement.
  • Seizures: Occur in ~5–10% of cases due to cortical irritation or metabolic disturbances.
  • Physiological mechanisms underlying post-rupture symptoms:
    1. Initial bleeding: Rupture releases blood into the subarachnoid space, triggering inflammation and vasospasm.
    2. Vasospasm: Smooth muscle contraction in cerebral arteries (peaking days 4–14 post-SAH) reduces perfusion, leading to delayed cerebral ischemia.
    3. Hydrocephalus: Blood obstructs CSF pathways, causing communicating hydrocephalus.
    4. Cerebral edema: Inflammatory mediators and blood breakdown products increase intracranial pressure.

    Post-rupture mortality without treatment exceeds 50%, with survivors often facing significant morbidity (e.g., cognitive deficits, epilepsy). Early surgical or endovascular intervention (clipping or coiling) is critical to prevent rebleeding and secondary complications.

    Location-Specific Symptom Variations in Brain Aneurysms

    Aneurysm symptoms vary by location, as different arteries supply distinct brain regions and cranial nerves. Below are case-based examples illustrating how anatomical position influences clinical presentation.

    1. Anterior Communicating Artery (AComA) Aneurysms

  • Common symptoms:
  • Bilateral frontal lobe compression: Apathy, memory deficits, or urinary incontinence (due to involvement of the cingulate gyrus).
  • Cranial nerve III palsy: Ptosis, dilated pupil, or "down-and-out" eye movement (if aneurysm compresses the nerve).
  • Psychiatric symptoms: Personality changes or depression (frontal lobe dysfunction).
  • Case example:
  • A 52-year-old hypertensive woman presents with progressive apathy, urinary incontinence, and a new-onset headache. MRI reveals an AComA aneurysm compressing the lamina terminalis. Her symptoms reflect frontal lobe dysfunction and hypothalamic irritation.

    2. Posterior Circulation Aneurysms (e.g., Basilar Tip, PICA)

  • Common symptoms:
  • Cranial nerve deficits: Dysphagia (CN IX/X), vertigo (vestibular nuclei), or ataxia (cerebellar compression).
  • Brainstem compression: Quadriparesis, crossed hemiplegia (alternating hemiplegia), or "locked-in syndrome" (if pontine involvement).
  • Visual disturbances: Bilateral blindness (if aneurysm compresses the optic chiasm or tracts).
  • Case example:
  • A 65-year-old smoker develops sudden vertigo, dysphagia, and left-sided weakness. Imaging shows a ruptured basilar tip aneurysm with fourth ventricle obstruction, causing hydrocephalus and brainstem compression.

    3. Posterior Communicating Artery (PComA) Aneurysms

  • Common symptoms:
  • Cranial nerve III palsy: Classic "down-and-out" eye deviation due to direct compression.
  • Oculomotor nerve dysfunction: Ptosis, miosis, or loss of pupillary light reflex.
  • Contral
  • Diagnosis and Medical Imaging Techniques for Brain Aneurysms

    Accurate diagnosis of brain aneurysms relies on advanced imaging modalities capable of detecting vascular abnormalities with high sensitivity and specificity. The choice of imaging technique depends on factors such as aneurysm size, patient comorbidities, and clinical urgency. Non-invasive methods, including computed tomography angiography (CTA) and magnetic resonance angiography (MRA), are often preferred for initial screening, while invasive digital subtraction angiography (DSA) remains the gold standard for definitive diagnosis and pre-surgical planning. Advanced imaging techniques, such as 3D rotational angiography and intraprocedural imaging, further refine treatment strategies by providing detailed anatomical and hemodynamic data.

    The diagnostic process integrates clinical suspicion, imaging findings, and patient risk stratification to guide therapeutic decisions. Below, the key imaging techniques—non-invasive, invasive, and advanced—are examined in detail, including their technical principles, clinical applications, and limitations.

    Non-Invasive Imaging Techniques

    Non-invasive imaging plays a pivotal role in the early detection and risk stratification of brain aneurysms, offering rapid, safe, and widely accessible diagnostic options. These techniques avoid direct arterial access, reducing procedural risks while maintaining high diagnostic accuracy for most clinical scenarios.

    Computed Tomography Angiography (CTA)
    CTA is the most commonly employed first-line imaging modality for suspected aneurysms due to its speed, availability, and high spatial resolution. The technique involves the intravenous administration of iodinated contrast, followed by helical CT scanning to visualize cerebral vasculature. Key advantages include:

  • Rapid acquisition (typically <30 seconds), making it ideal for acute settings (e.g., subarachnoid hemorrhage).
  • High spatial resolution (0.5–1.0 mm), enabling detection of aneurysms ≥3 mm with >95% sensitivity.
  • Wide availability and compatibility with critically ill patients, including those with pacemakers or claustrophobia.
  • Interpreting a CTA Scan for Aneurysm Detection
    Aneurysm identification on CTA hinges on recognizing specific visual markers:
    1. Contrast pooling: A localized outpouching filled with contrast, distinct from the parent vessel’s lumen.
    2. Vessel dilation: Abnormal bulging or sac-like formation along a cerebral artery, often at bifurcations (e.g., anterior communicating artery).
    3. Signs of rupture: Hyperdense subarachnoid blood (suggestive of SAH) or intraparenchymal hematoma.
    4. Artifacts to exclude:

  • Motion artifacts (blurring due to patient movement).
  • Beam hardening (dark streaks near bony structures, e.g., skull base).
  • Partial volume averaging (underestimation of small aneurysms due to slice thickness).
  • Aneurysms <5 mm may require multiplanar reconstructions (MPR) or maximum intensity projection (MIP) to enhance visualization. 3D volume-rendered reconstructions further aid in surgical planning by providing a comprehensive view of aneurysm geometry and relation to surrounding structures.

    Magnetic Resonance Angiography (MRA)

    MRA leverages magnetic resonance principles to generate high-contrast images of cerebral vasculature without ionizing radiation. It is particularly useful in patients with renal impairment (contraindication to iodinated contrast) or those requiring repeated imaging. Two primary MRA techniques exist:
  • Time-of-Flight (TOF) MRA: Relies on blood flow to create contrast; limited by in-plane saturation of slow-flow vessels.
  • Contrast-Enhanced MRA (CE-MRA): Uses gadolinium-based contrast for improved spatial resolution and detection of small aneurysms.
  • Advantages:

  • No ionizing radiation, making it safer for repeated scans or pediatric patients.
  • Superior soft-tissue contrast, useful for detecting aneurysms near the skull base or in complex geometries.
  • Functional imaging capabilities (e.g., perfusion studies) to assess collateral circulation.
  • Limitations:

  • Lower spatial resolution compared to CTA (typically 0.8–1.2 mm), reducing sensitivity for aneurysms <3 mm.
  • Longer scan times (3–10 minutes), increasing susceptibility to motion artifacts.
  • Contraindications for patients with gadolinium allergies or severe renal dysfunction (risk of nephrogenic systemic fibrosis).
  • Invasive Imaging: Digital Subtraction Angiography (DSA)

    DSA remains the gold standard for aneurysm diagnosis and pre-surgical planning due to its unparalleled spatial and temporal resolution. The procedure involves catheter-based arterial cannulation and real-time contrast injection, followed by digital subtraction to isolate vascular structures. Key applications include:
  • Definitive diagnosis of small or complex aneurysms missed by non-invasive methods.
  • Pre-surgical mapping for endovascular coiling or clipping, including assessment of aneurysm neck width, dome-to-neck ratio, and parent vessel dominance.
  • Intraprocedural guidance during embolization or stenting.
  • Technical Workflow:
    1. Femoral or radial artery access under fluoroscopic guidance.
    2. Catheter navigation to the internal carotid or vertebral arteries using roadmap imaging.
    3. Contrast injection (5–10 mL/s) with serial angiographic images (typically 1–3 frames/second).
    4. Subtraction technique: Post-processing to remove bony and soft-tissue structures, isolating the vasculature.

    Risks and Complications:

  • Procedure-related risks: Vascular injury (0.5–2%), stroke (1–2%), or contrast-induced nephropathy (up to 5% in high-risk patients).
  • Radiation exposure: Cumulative dose may exceed 50 mGy, requiring shielding for staff and patients.
  • Allergic reactions to iodinated contrast (1–5% incidence).
  • Comparison of Imaging Modalities for Aneurysm Detection

    The choice of imaging technique depends on aneurysm size, clinical urgency, and patient-specific factors. Below is a comparative analysis of CTA, MRA, and DSA for detecting aneurysms <10 mm, including resolution limits and patient suitability.
    Modality Spatial Resolution (mm) Sensitivity (<10 mm) Specificity Key Advantages Limitations Patient Suitability
    CT Angiography (CTA) 0.5–1.0 90–95% 98–100%
    • Rapid acquisition (<30 sec).
    • High resolution for aneurysms ≥3 mm.
    • Wide availability.
    • Ionizing radiation exposure.
    • Contrast nephropathy risk.
    • Artifacts in complex geometries.
    • Acute stroke/SAH evaluation.
    • Patients with pacemakers or claustrophobia.
    • Renal impairment (if low-contrast protocols used).
    MR Angiography (MRA) 0.8–1.2 80–85% 95–97%
    • No ionizing radiation.
    • Superior soft-tissue contrast.
    • Functional imaging (perfusion).
    • Lower resolution for small aneurysms.
    • Longer scan times (motion artifacts).
    • Gadolinium contraindications.
    • Renal impairment (non-contrast MRA).
    • Pediatric or pregnant patients.
    • Follow-up imaging.
    Digital Subtraction Angiography (DSA) 0.1–0.3 98–100% 99–100%
    • Gold standard resolution.
    • Real-time guidance for interventions.
    • Assessment of complex anatomies.

    Treatment Options and Interventional Procedures for Brain Aneurysms

    Brain aneurysms require timely and precise intervention to prevent rupture and mitigate neurological deficits. Treatment strategies are tailored based on aneurysm size, location, patient comorbidities, and risk tolerance. The two primary interventional approaches—surgical clipping and endovascular coiling—represent the gold standard, each with distinct mechanisms, efficacy profiles, and recovery trajectories. Emerging techniques, such as flow diversion and stent-assisted embolization, expand therapeutic options for complex or recurrent cases, though their adoption remains contingent on clinical trial validation and long-term outcomes.

    The choice between surgical and endovascular methods hinges on factors including aneurysm morphology, vascular accessibility, and patient-specific risks. Below, a comparative analysis of these modalities is presented, followed by detailed procedural descriptions and an overview of innovative therapies under investigation.

    Comparative Analysis of Surgical Clipping and Endovascular Coiling

    The selection between surgical clipping and endovascular coiling is determined by aneurysm characteristics, patient health, and institutional expertise. The following table summarizes key differences in mechanism, success rates, complications, and recovery timelines, derived from meta-analyses and large-scale studies (e.g., ISAT trial, CLARITY trial).
    Parameter Surgical Clipping Endovascular Coiling
    Mechanism

    Direct occlusion of the aneurysm neck via titanium or platinum clip applied during open craniotomy. Preserves normal blood flow through parent artery.

    Intra-aneurysmal embolization using platinum coils delivered via microcatheter. Promotes thrombus formation and isolates the aneurysm sac from circulation.

    Success Rates (Complete Occlusion)

    90–95% for anterior circulation aneurysms; lower for posterior circulation or complex geometries (e.g., fusiform).

    Note: Long-term recurrence rates (~5–10% at 10 years) may require re-treatment.

    70–90% for anterior circulation; 50–80% for posterior circulation. Higher recurrence risk with wide-neck or large aneurysms.

    Note: ISAT trial demonstrated 23.7% reintervention rate at 1 year for coiling vs. 12.6% for clipping.
    Major Complications
    • Cerebral edema (5–10%), ischemia (3–7%), or hematoma due to retraction or clip malposition.
    • Cranial nerve palsies (e.g., III, IV, VI) in basilar tip or cavernous sinus aneurysms.
    • Infection or CSF leak (~1–2%).
    • Thromboembolic events (5–10%), leading to stroke or transient deficits.
    • Coil protrusion or aneurysm regrowth (10–20% at 5 years).
    • Procedure-related hemorrhage (<1%) or vasospasm.
    Recovery Timeline

    Hospital stay: 5–10 days. Neurological recovery may take weeks to months, with ~50% of patients achieving full independence by 6 months.

    Note: Elderly or comorbid patients may experience prolonged cognitive or motor deficits.

    Hospital stay: 1–3 days. Most patients resume daily activities within 2–4 weeks, though fatigue or mild headaches may persist.

    Note: Antiplatelet therapy (e.g., aspirin/clopidogrel) is required for 3–6 months post-procedure.
    Indications
    • Large or giant aneurysms (>25 mm).
    • Complex geometries (e.g., wide-neck, bifurcation).
    • Posterior circulation aneurysms (e.g., basilar tip).
    • Patients with contraindications to antiplatelet therapy.
    • Small to medium aneurysms (<20 mm).
    • Accessible aneurysms with favorable neck-to-sac ratios.
    • High surgical risk (e.g., elderly, comorbidities).
    • Recurrent or residual aneurysms post-clipping.

    Step-by-Step Process of Endovascular Coiling

    Endovascular coiling is a minimally invasive technique performed under general anesthesia with real-time imaging guidance. The procedure involves precise catheter navigation, coil deployment, and post-procedural monitoring to ensure aneurysm exclusion while preserving parent artery patency.

    Pre-procedural Preparation:

  • Patient Workup: Non-contrast CT or MRI to rule out acute hemorrhage; angiography to confirm aneurysm morphology.
  • Anticoagulation: Heparin administered intra-arterially to maintain ACT >250 seconds; antiplatelet therapy (e.g., aspirin 325 mg + clopidogrel 600 mg) initiated 24–48 hours pre-procedure.
  • Equipment: Guide catheter (6–8 Fr), microcatheter (e.g., Excelsior SL-10), and detachable coils (e.g., Target, Axium Prime).
  • Intra-procedural Steps:
    1. Femoral Artery Access:

  • Puncture under ultrasound guidance; insertion of a long sheath into the common femoral artery.
  • Technique: Seldinger technique with wire-guided advancement to avoid arterial dissection.
  • 2. Catheter Navigation:

  • Guide catheter positioned in the internal carotid or vertebral artery under roadmap imaging (pre-subtracted angiographic images).
  • Microcatheter advanced coaxially through the guide, navigating tortuous vessels (e.g., petrous carotid) using 3D rotational angiography for spatial orientation.
  • 3. Aneurysm Selectivity:

  • Microcatheter tip positioned at the aneurysm dome, confirmed via microcatheter angiography.
  • Challenge: Wide-neck aneurysms may require balloon or stent assistance to prevent coil herniation into the parent artery.
  • 4. Coil Deployment:

  • Detachable coils (pre-loaded in the microcatheter) released in a "pushing" or "pulling" technique to fill the aneurysm sac.
  • Dense Packing: Aim for >20% volume occupancy to minimize recurrence; coils may be deployed in stages with intermediate angiograms.
  • Real-Time Imaging: Fluoroscopy and digital subtraction angiography (DSA) used to monitor coil compaction or protrusion.
  • 5. Post-Deployment Assessment:

  • Final angiogram to confirm aneurysm occlusion (Raymond-Roy Classification: Class I = complete filling; Class V = residual neck).
  • Complication Check: Evaluation for thromboembolic events (e.g., delayed ischemia) or coil migration.
  • Post-Procedural Monitoring:

  • ICU Observation: 24–48 hours for neurological changes or signs of vasospasm (e.g., elevated blood pressure, focal deficits).
  • Antiplatelet Therapy: Dual antiplatelet agents (DAPT) for 3–6 months; aspirin monotherapy thereafter.
  • Follow-Up Imaging: MRA or CTA at 6 months, 1 year, and annually to assess recurrence or coil compaction.
  • Surgical Clipping Technique and Intraoperative Neuromonitoring

    Surgical clipping remains the definitive treatment for complex aneurysms, offering durable occlusion with immediate anatomical control. The procedure involves craniotomy, aneurysm exposure, clip application, and neuromonitoring to preserve neural function.

    Preoperative Planning:

  • Imaging: 3D rotational angiography or CT angiography to assess aneurysm geometry, parent artery dominance, and surrounding vasculature.
  • Surgical Approach: Tailored based on aneurysm location (e.g.,

    Brain aneurysms exemplify the delicate balance between vascular resilience and pathological fragility, where early detection and targeted intervention can drastically alter patient outcomes. From the subtle warnings of pre-rupture symptoms to the decisive moments in surgical or endovascular repair, each stage demands a multidisciplinary approach rooted in advanced imaging and evidence-based protocols. As therapeutic innovations—such as flow diversion and liquid embolics—continue to refine treatment paradigms, the imperative remains clear: proactive education, rigorous diagnostic evaluation, and personalized management strategies are indispensable in reducing the devastating impact of this condition. By synthesizing anatomical insights with clinical actionability, this overview underscores the urgency of addressing aneurysms before rupture transforms a treatable abnormality into a life-threatening emergency.

  • What Is A Brain Aneurysm - Kesimpulan