Vitamin B 1 Deficiency Symptoms and Their Critical Health Impacts
Table of Contents
- Clinical Manifestations of Vitamin B1 (Thiamine) Deficiency
- Early-Stage Physical Symptoms and Subtle Indicators
- Advanced Deficiency Symptoms: Neurological and Cardiovascular Complications
- Comparison of Acute vs. Chronic Thiamine Deficiency Symptoms
- Pathophysiological Progression in Alcohol-Dependent Individuals
- Diagnostic Approaches for Identifying Thiamine (Vitamin B1) Deficiency
- Laboratory Tests for Thiamine Deficiency Confirmation
- Clinical Assessment Tools and Their Integration with Laboratory Results
- Diagnostic Flowchart: From Patient History to Confirmatory Tests
- Step 1: Risk Stratification and Clinical Suspicion
- Step 2: Initial Clinical Assessment
- Step 3: Laboratory Confirmation
- Population-Specific Risk Factors and Vulnerabilities in Thiamine (Vitamin B1) Deficiency
- Demographic and Medical Risk Factors for Thiamine Deficiency
- Mechanisms of Impaired Thiamine Absorption in Specific Conditions
- Neurological and Cardiovascular Complications of Thiamine Deficiency
- Pathophysiological Mechanisms Linking Thiamine Deficiency to Beriberi and Heart Failure
- Comparison of Neurological Damage in Wernicke Encephalopathy and Korsakoff Psychosis
- Exacerbation of Pre-Existing Conditions by Thiamine Deficiency
- Nutritional Interventions and Thiamine Repletion Strategies
- Recommended Dietary Allowance (RDA) for Thiamine by Life Stage
- Thiamine-Rich Foods and Bioavailability by Food Group
- Animal Sources (High Bioavailability)
- Plant-Based Sources (Variable Bioavailability)
- Fermented and Processed Foods
- Comparison of Oral vs. Intravenous Thiamine Supplementation Protocols
- Preventive Measures and Public Health Initiatives for Thiamine (Vitamin B1) Deficiency
- Global Strategies for Thiamine Fortification and Their Effectiveness
- Community-Based Interventions and Measurable Outcomes
- Behavioral Modifications to Prevent Thiamine Deficiency
- Integration of Thiamine Awareness into Broader Malnutrition Prevention Campaigns
Vitamin B1 or thiamine plays a pivotal role in energy metabolism and neurological function yet remains overlooked in global nutritional discussions. Its deficiency triggers a spectrum of symptoms ranging from subtle fatigue to severe neurological and cardiovascular disorders. Early recognition of these manifestations is essential as progression can lead to irreversible complications such as Wernicke-Korsakoff syndrome or beriberi. This exploration examines the clinical presentations, diagnostic pathways, and high-risk populations vulnerable to thiamine depletion.
The consequences of thiamine deficiency extend beyond individual health to public health challenges particularly in regions reliant on refined grains or populations with metabolic disorders. Understanding the pathophysiological mechanisms and preventive strategies is critical for clinicians and policymakers alike. From laboratory diagnostics to nutritional interventions this analysis provides a comprehensive framework for addressing a often underdiagnosed yet preventable condition.

Clinical Manifestations of Vitamin B1 (Thiamine) Deficiency
Vitamin B1, or thiamine, plays a critical role in carbohydrate metabolism, nerve function, and energy production. Its deficiency disrupts these processes, leading to a spectrum of symptoms ranging from mild systemic complaints to severe, life-threatening neurological and cardiovascular complications. Early-stage deficiencies often present subtly, masking the underlying metabolic dysfunction, while advanced stages reveal irreversible organ damage. This section systematically examines the progression of thiamine deficiency, emphasizing its clinical manifestations across different organ systems and populations, particularly in high-risk groups such as alcohol-dependent individuals.The clinical presentation of thiamine deficiency varies depending on the duration, severity, and underlying causes of the deficiency. In early stages, symptoms are non-specific and may be attributed to other conditions, delaying diagnosis. As deficiency progresses, organ-specific dysfunction becomes evident, particularly in the nervous system, cardiovascular system, and gastrointestinal tract. Below, the manifestations are categorized by stage—acute and chronic—with a focus on their pathophysiological mechanisms and diagnostic implications.
Early-Stage Physical Symptoms and Subtle Indicators
The initial symptoms of thiamine deficiency are often overlooked due to their non-specific nature, but they serve as critical early warning signs. These manifestations arise from impaired cellular energy metabolism, particularly in tissues with high energy demands such as the nervous system and skeletal muscles. Fatigue and generalized weakness are among the first indicators, reflecting reduced ATP production in mitochondria. Irritability and mild cognitive dysfunction, such as forgetfulness or difficulty concentrating, may also emerge due to thiamine’s role in neurotransmitter synthesis and neuronal signaling.Peripheral nerve dysfunction manifests as paresthesia (tingling or numbness), typically in the hands and feet, resulting from axonal degeneration in sensory nerves. Gastrointestinal symptoms, including anorexia, nausea, and abdominal discomfort, are common and may be attributed to impaired smooth muscle function in the gastrointestinal tract. Muscle cramps or tenderness, particularly in the calves, further indicate mitochondrial dysfunction in skeletal muscle. These early symptoms often resolve with thiamine supplementation but may progress to severe complications if untreated.
Advanced Deficiency Symptoms: Neurological and Cardiovascular Complications
Prolonged thiamine deficiency leads to severe, often irreversible, damage to the nervous and cardiovascular systems. The most critical syndromes include Wernicke-Korsakoff syndrome (WKS), beriberi, and acute thiamine deficiency encephalopathy. Each syndrome reflects distinct pathophysiological pathways but shares a common underlying mechanism: impaired thiamine-dependent enzyme activity (e.g., transketolase, pyruvate dehydrogenase, and α-ketoglutarate dehydrogenase).### Wernicke-Korsakoff Syndrome (WKS)
WKS is a neuropsychiatric disorder primarily observed in alcohol-dependent individuals but can occur in any population with severe thiamine deficiency. It consists of two overlapping phases:
1. Wernicke’s Encephalopathy (WE) – An acute, potentially reversible condition characterized by:
2. Korsakoff’s Psychosis – A chronic, irreversible memory disorder developing in ~85% of untreated WE cases. Key features include:
### Beriberi
Beriberi presents in two main forms:
- Dry Beriberi: A neurological and muscular syndrome featuring:
### Acute Thiamine Deficiency Encephalopathy
This rare but severe condition presents as acute confusion, seizures, and coma, often mimicking stroke or metabolic encephalopathy. It is linked to rapid thiamine depletion (e.g., after bariatric surgery or hyperemesis gravidarum) and involves cerebral edema and neuronal death in the thalamus, brainstem, and cerebellum.
Comparison of Acute vs. Chronic Thiamine Deficiency Symptoms
The progression of thiamine deficiency can be stratified by duration and affected organ systems. Below is a comparative table summarizing key differences between acute and chronic manifestations:| Feature | Acute Deficiency (Weeks to Months) | Chronic Deficiency (Months to Years) |
|---|---|---|
| Primary Organ Systems Affected | Nervous system (rapid onset), cardiovascular (high-output failure) | Nervous system (permanent damage), cardiovascular (chronic heart failure), gastrointestinal (malabsorption) |
| Neurological Symptoms |
|
|
| Cardiovascular Symptoms |
|
|
| Gastrointestinal Symptoms | Anorexia, nausea, mild abdominal discomfort |
|
| Reversibility | Partially reversible with early thiamine replacement (if no permanent damage) | Permanent neurological damage (e.g., Korsakoff’s syndrome) despite treatment |
| Pathophysiological Mechanism | Rapid depletion of thiamine pyrophosphate (TPP) → impaired pyruvate dehydrogenase and α-ketoglutarate dehydrogenase → lactic acidosis, ATP depletion, and oxidative stress. |
Chronic TPP deficiency → axonal degeneration (peripheral neuropathy), thalamic/mammillary body necrosis (WKS), and cardiac myocyte dysfunction (beriberi). |
Pathophysiological Progression in Alcohol-Dependent Individuals
Alcohol dependence is the leading cause of thiamine deficiency due to reduced dietary intake, impaired absorption, and increased metabolic demand. The progression in these individuals follows a metabolic and neurological cascade with distinct stages:1
Diagnostic Approaches for Identifying Thiamine (Vitamin B1) Deficiency
Thiamine deficiency presents with a spectrum of clinical manifestations ranging from subclinical impairment to severe syndromes such as beriberi and Wernicke-Korsakoff syndrome. Accurate diagnosis requires a multimodal approach integrating patient history, clinical assessment, and laboratory confirmation. Laboratory tests play a critical role in identifying biochemical abnormalities, while clinical tools like the Medical Research Council (MRC) scale for neuropathy provide functional correlation. However, diagnostic challenges arise due to limitations in test sensitivity, atypical presentations in vulnerable populations (e.g., infants, elderly), and overlapping symptoms with other deficiencies. This section outlines evidence-based diagnostic methodologies, their clinical integration, and alternative strategies for high-risk groups.Laboratory Tests for Thiamine Deficiency Confirmation
Biochemical assays remain the gold standard for diagnosing thiamine deficiency, though their interpretation must account for physiological variability and assay-specific limitations. The most widely used tests include erythrocyte transketolase activity (ETKA), whole-blood thiamine levels, and urinary thiamine excretion. Each method targets distinct metabolic pathways affected by thiamine deficiency, but none are universally definitive due to preanalytical factors, false positives/negatives, or population-specific thresholds.Key Laboratory Assays and Their Mechanisms
Thiamine functions as a cofactor for enzymes in carbohydrate metabolism, particularly the transketolase pathway in the pentose phosphate cycle. Deficiency impairs this pathway, leading to measurable biochemical changes:
- Erythrocyte Transketolase Activity (ETKA)
ETKA measures the activity of transketolase, an enzyme dependent on thiamine pyrophosphate (TPP). The ETKA activation coefficient (ETKAC) is calculated as the ratio of enzyme activity before and after in vitro TPP supplementation. A coefficient > 1.25 indicates deficiency, though values may vary with hemolytic conditions or recent blood transfusions. Limitations include:
- Whole-Blood Thiamine Levels
Direct measurement of thiamine (primarily thiamine pyrophosphate and thiamine monophosphate) via high-performance liquid chromatography (HPLC) or microbiological assays provides a quantitative assessment. Reference ranges typically fall between 7–21 ng/mL, but cutoffs must be adjusted for:
- Urinary Thiamine Excretion
24-hour urinary thiamine excretion < 50 µg/day suggests deficiency, though this test is less sensitive than ETKA or blood assays. Key considerations include:
Clinical Note: No single laboratory test is definitive for thiamine deficiency. A combined approach—e.g., low ETKA activation coefficient and low blood thiamine—strengthens diagnostic confidence. Functional assays (e.g., lactate/pyruvate ratios) may complement biochemical tests in ambiguous cases.
Clinical Assessment Tools and Their Integration with Laboratory Results
Clinical evaluation bridges biochemical abnormalities with functional impairment, particularly in neurological and cardiovascular presentations. The Medical Research Council (MRC) scale for neuropathy and Wernicke-Korsakoff syndrome (WKS) diagnostic criteria are widely used to quantify deficits and guide thiamine supplementation. These tools are most valuable when correlated with laboratory findings, as they address the functional consequences of deficiency rather than its biochemical presence.Integration of Clinical and Laboratory Data
A structured diagnostic workflow ensures that laboratory results are interpreted in the context of clinical suspicion. For example:
- Neurological Assessment (MRC Scale for Neuropathy)
The MRC scale evaluates muscle strength (0–5) and reflexes (0–4) in peripheral neuropathy, a hallmark of dry beriberi. A score ≤ 3/5 in key muscle groups (e.g., dorsiflexion, knee extension) with reduced reflexes suggests severe deficiency. When combined with:
- Wernicke-Korsakoff Syndrome (WKS) Criteria
WKS diagnosis relies on the Caine criteria (2007), requiring two of four features (confusion, ocular abnormalities, ataxia, memory deficits) with no alternative explanation. Laboratory support includes:
Diagnostic Algorithm Principle:
Laboratory confirmation should support clinical suspicion rather than replace it. For instance, a patient with ataxia, confusion, and nystagmus (suggestive of WKS) may have normal ETKA due to recent thiamine supplementation, but low blood thiamine would still warrant treatment.
Diagnostic Flowchart: From Patient History to Confirmatory Tests
The diagnostic process for thiamine deficiency follows a risk-stratified, stepwise approach, prioritizing high-yield clinical tools before proceeding to laboratory confirmation. Below is a structured flowchart outlining the evaluation pathway:Step 1: Risk Stratification and Clinical Suspicion
-
Identify high-risk populations based on:
- Dietary factors: Chronic alcohol use, malabsorption (e.g., celiac disease, bariatric surgery), or thiamine-poor diets (e.g., polished rice-dependent populations).
- Metabolic demands: Hyperemesis gravidarum, dialysis-dependent renal failure, or HIV/AIDS with malabsorption.
- Medications: Long-term diuretic use (e.g., furosemide), chemotherapy (e.g., cisplatin), or antiretrovirals.
-
Screen for clinical red flags:
- Neurological: Symmetrical peripheral neuropathy, confusion, ophthalmoplegia, or memory deficits.
- Cardiovascular: High-output heart failure (wet beriberi) or dilated cardiomyopathy in the absence of ischemic heart disease.
- Gastrointestinal: Anorexia, nausea, or abdominal discomfort (common in early deficiency).
Step 2: Initial Clinical Assessment
-
Neurological evaluation:
- Administer the MRC scale for neuropathy (focus on distal muscle groups).
- Assess for WKS features using the Caine criteria (confusion, nystagmus, ataxia, confabulation).
-
Cardiovascular assessment:
- Evaluate for high-output heart failure (tachycardia, peripheral edema, warm extremities) in suspected wet beriberi.
- Exclude other causes (e.g., thyroid dysfunction, anemia) via ECG (e.g., low voltage, nonspecific ST-T changes).
Step 3: Laboratory Confirmation
-
First-line tests (prioritize based on clinical presentation):
- ETKA activation coefficient for neurological/cardiovascular symptoms.
- Whole-blood thiamine levels in malnourished patients or those with atypical presentations.
-
Second-line tests (for ambiguous cases):
- Urinary thiamine excretion (if blood tests are unavailable).
- Lactate/pyruvate ratio (elevated in severe deficiency due to impaired pyruvate dehydrogenase activity).
- Maternal deficiency linked to infant beriberi (Wernicke-Korsakoff syndrome in neonates).
- Breastfeeding mothers may deplete stores if dietary intake is insufficient.
- Alcohol-related malnutrition accelerates deficiency in this group.
- Chronic kidney disease increases thiamine loss via hemodialysis.
- Ethanol metabolism competes for NAD+, depleting cofactors needed for thiamine activation.
- Poor nutrition (empty calorie intake) further reduces dietary thiamine.
- Diabetic ketoacidosis exacerbates deficiency by increasing TPP requirements for pyruvate dehydrogenase.
- Peripheral neuropathy in diabetics may reflect subclinical thiamine deficiency.
- Post-surgery malabsorption of fat-soluble vitamins (e.g., A, D, E) may coincide with thiamine deficiency.
- Lack of routine supplementation in some clinics.
- Thiamine content in plant foods is lower than in animal sources (e.g., 0.05 mg/100g in lentils vs. 0.6 mg in pork).
- Ketogenic diets increase thiamine requirements for fatty acid metabolism.
- Celiac Disease: Inflammation and villous atrophy destroy enterocytes expressing thiamine transporters, reducing absorption by 60–80%.
- Inflammatory Bowel Disease (IBD): Chronic diarrhea and mucosal damage in Crohn’s disease or ulcerative colitis lead to malabsorption, with 30–50% of patients exhibiting subclinical deficiency.
- Short Bowel Syndrome: Bypass of the jejunum (primary absorption site) results in <20% thiamine bioavailability without supplementation.
- Roux-en-Y Gastric Bypass: Exclusion of the duodenum/jejunum reduces thiamine absorption by 40–60%, with 10–30% of patients developing deficiency post-surgery.
- Sleeve Gastrectomy: While preserving the duodenum, rapid gastric emptying may limit contact time for
- Accumulation of pyruvate and lactate, causing metabolic acidosis and cellular hypoxia.
- Impaired ATP production, particularly in high-energy-demand tissues like the heart and brain.
- Oxidative stress due to mitochondrial dysfunction, exacerbating tissue damage.
- Sympathetic overactivity secondary to lactic acidosis and reduced ATP availability.
- Myocardial dysfunction, progressing to dilated cardiomyopathy with systolic impairment.
- Edema and congestive heart failure, driven by increased capillary permeability and sodium retention.
- Pyruvate dehydrogenase (PDH) inhibition → Pyruvate → Lactate (↑ lactic acidosis).
- α-Ketoglutarate dehydrogenase (α-KGDH) inhibition → TCA cycle blockade (↓ ATP).
- Transketolase pathway impairment → Altered pentose phosphate pathway (↓ NADPH, ↑ oxidative stress).
Population-Specific Risk Factors and Vulnerabilities in Thiamine (Vitamin B1) Deficiency
Thiamine deficiency disproportionately affects certain populations due to physiological, behavioral, or socioeconomic factors that disrupt absorption, utilization, or dietary intake. High-risk groups exhibit unique vulnerabilities, often compounded by underlying medical conditions, dietary restrictions, or environmental influences. Understanding these risk factors enables targeted prevention and early intervention strategies.The susceptibility to thiamine deficiency varies significantly across demographics, with chronic alcohol use, metabolic disorders, and gastrointestinal impairments emerging as primary contributors. Mechanisms of impaired absorption—such as reduced thiamine transporter activity or malabsorption syndromes—further exacerbate deficiencies in specific clinical contexts. Socioeconomic and cultural practices, including reliance on refined staple foods, also play a critical role in regional outbreaks, particularly in low-resource settings.
Demographic and Medical Risk Factors for Thiamine Deficiency
Thiamine deficiency is not uniformly distributed; certain age groups, medical histories, and lifestyles increase susceptibility due to altered metabolism, dietary patterns, or physiological changes. Below is a structured breakdown of high-risk populations, organized by demographic and clinical criteria.
Key Principle:
Thiamine requirements vary by life stage (e.g., pregnancy, lactation) and metabolic demand, while conditions like diabetes or alcoholism accelerate depletion through increased urinary excretion or impaired absorption.Demographic/Lifestyle Medical History Mechanism of Risk Example Populations Age Groups Pregnancy/Lactation Increased thiamine demand (1.4x higher in pregnancy) and reduced intake due to dietary restrictions or nausea. Pregnant women in regions with polished rice diets (e.g., Southeast Asia), adolescent mothers. Elderly (≥65 years) Reduced dietary intake (poor appetite, polypharmacy), malabsorption (atrophic gastritis), and decreased thiamine stores. Institutionalized elderly, individuals on thiamine-depleting medications (e.g., diuretics). Chronic Alcohol Use Alcoholic Liver Disease Direct inhibition of thiamine absorption in the jejunum, reduced phosphorylation to active thiamine pyrophosphate (TPP), and increased urinary excretion. Chronic alcoholics with ≥15 years of heavy consumption, homeless populations. Wernicke-Korsakoff Syndrome Thiamine deficiency in alcoholics leads to acute encephalopathy (confusion, ataxia) and chronic memory deficits due to neuronal damage in the mamillary bodies and thalamus. Patients presenting with ophthalmoplegia, confabulation, or global cognitive decline. Binge Drinking Patterns Acute thiamine depletion from repeated alcohol binges, even without chronic use, due to rapid glycogen depletion and lactic acidosis. Young adults in social drinking cultures (e.g., college students, festival attendees). Metabolic Disorders Type 1 and Type 2 Diabetes Increased thiamine excretion via glycosuria (glucose competes with thiamine for renal reabsorption) and impaired glucose metabolism. Long-standing diabetics on high-dose insulin or sulfonylureas. Hyperthyroidism Elevated metabolic rate increases thiamine turnover, while malabsorption (e.g., celiac disease) may coexist. Patients with Graves’ disease or untreated thyrotoxicosis. Gastrointestinal and Nutritional Factors Bariatric Surgery (Roux-en-Y, Sleeve Gastrectomy) Reduced intestinal surface area and bypass of thiamine-rich duodenal/jejunal segments. Post-bariatric patients with persistent nausea, fatigue, or neuropathy. Celiac Disease Villous atrophy in the small intestine impairs thiamine absorption, compounded by dietary restrictions (e.g., avoidance of whole grains). Undiagnosed celiac patients with chronic diarrhea or weight loss. Fad/Restrictive Diets Thiamine-poor diets (e.g., raw foodism, veganism without fortification) or prolonged fasting. Individuals adhering to unbalanced macrobiotic or crash diets. Mechanisms of Impaired Thiamine Absorption in Specific Conditions
Thiamine absorption primarily occurs in the proximal small intestine via active transport (SLC19A2 and SLC19A3 transporters) and passive diffusion. Disruptions in these processes—whether due to structural, enzymatic, or competitive inhibition—underlie deficiency in high-risk groups.
Critical Pathways:
Gastrointestinal Disorders:
1. Active Transport: SLC19A2 (ThTr-1) mediates thiamine uptake in the duodenum/jejunum; mutations or downregulation reduce absorption.
2. Phosphorylation: Thiamine kinase converts thiamine to TPP; alcohol and diabetes impair this step.
3. Competitive Inhibition: High glucose or ethanol levels saturate renal reabsorption pathways, increasing urinary loss.
Bariatric Surgery:
Neurological and Cardiovascular Complications of Thiamine Deficiency
Thiamine (vitamin B1) deficiency disrupts critical metabolic pathways, leading to severe neurological and cardiovascular disorders. The enzyme thiamine pyrophosphate (TPP) is essential for pyruvate dehydrogenase and α-ketoglutarate dehydrogenase complexes, which regulate energy metabolism in neurons and cardiac myocytes. Disruption of these pathways results in lactic acidosis, oxidative stress, and mitochondrial dysfunction, manifesting as beriberi (wet/dry forms) and Wernicke-Korsakoff syndrome (WKS). Cardiovascular complications arise from impaired ATP production in the heart, while neurological damage stems from neurotransmitter dysregulation and neuronal degeneration in specific brain regions.The pathological mechanisms underlying thiamine deficiency involve both direct enzymatic dysfunction and secondary metabolic derangements. In the cardiovascular system, energy depletion in myocardial cells leads to systolic dysfunction, dilated cardiomyopathy, and high-output heart failure—characteristic of wet beriberi. Neurologically, thiamine deficiency impairs glucose metabolism in the brain, particularly in regions dependent on aerobic respiration, such as the mammillary bodies, thalamus, periaqueductal gray matter, and cerebellum, resulting in WKS. Below, the interplay between metabolic disruptions and systemic complications is explored, followed by comparative analyses of neurological syndromes and case studies demonstrating exacerbation of pre-existing conditions.
Pathophysiological Mechanisms Linking Thiamine Deficiency to Beriberi and Heart Failure
Thiamine deficiency disrupts pyruvate oxidation and the Krebs cycle, leading to:
In wet beriberi, peripheral vasodilation and high cardiac output result from:
Key metabolic disruptions in thiamine deficiency:
The heart is particularly vulnerable due to its reliance on oxidative phosphorylation. Thiamine deficiency reduces myocardial contractility via: - Decreased calcium handling (impaired sarcoplasmic reticulum function).
- Mitochondrial swelling and cristae disorganization, leading to apoptosis.
- Endothelial dysfunction, contributing to vasodilation and edema in wet beriberi.
- Acute thiamine deficiency with metabolic crisis (e.g., alcohol withdrawal, malnutrition).
- Neuroinflammation and excitotoxicity due to GABA/glutamate imbalance.
- Mammillary body necrosis (most sensitive to thiamine deficiency).
- Persistent thiamine deficiency with chronic neuronal loss in limbic and diencephalic regions.
- Synaptic plasticity impairment (e.g., reduced BDNF, altered hippocampal function).
- Thalamic and frontal lobe atrophy, contributing to memory deficits.
- Confusion/delirium (due to thiamine-dependent neurotransmitter dysfunction).
- Oculomotor dysfunction (nystagmus, ophthalmoplegia from cranial nerve III/IV/VI involvement).
- Ataxia (cerebellar and vestibular dysfunction).
- Anterograde amnesia (inability to form new memories).
- Confabulation (filling memory gaps with fabricated details).
- Executive dysfunction (poor judgment, apathy).
- Mammillary bodies (hypothalamic nuclei critical for memory consolidation).
- Thalamus (relay station for sensory/motor pathways).
- Periventricular gray matter (brainstem nuclei regulating autonomic function).
- Cerebellum (coordination and balance).
- Dorsomedial thalamus (memory circuit disruption).
- Hippocampus (long-term memory formation).
- Prefrontal cortex (executive function and decision-making).
- Basal forebrain (cholinergic neuron degeneration).
- Patient Profile: A 62-year-old male with type 2 diabetes (HbA1c 9.2%) and long-standing peripheral neuropathy (symptoms: burning pain, numbness in lower extremities).
- Exacerbating Factor: Poor dietary intake (restricted carbohydrate diet) and chronic alcohol use (30g/day for 15 years).
- Pathophysiology:
- Diabetes → Polyol pathway activation (↓ NADPH, ↑ oxidative stress) + advanced glycation end-products (AGEs) → Neuropathic damage.
- Thiamine deficiency → PDH inhibition → Lactic acidosis → Nerve hypoxia and mitochondrial dysfunction in dorsal root ganglia.
- Outcome: Progressive sensory ataxia and autonomic dysfunction (orthostatic hypotension), unresponsive to gabapentin until thiamine (300mg IV daily) + insulin adjustment were initiated.
- Patient Profile: A 55-year-old male with chronic alcoholism (200g/day for 20 years) presenting with dyspnea, edema, and tachycardia.
- Exacerbating Factor: Malnutrition (thiamine intake <0.5mg/day) and recent gastroenteritis (reduced absorption).
- Pathophysiology:
- Alcohol → Direct myocardial toxicity (↓ cardiac output) + malnutrition → Thiamine deficiency.
- Wet beriberi → High-output heart failure (↑ cardiac workload due to vasodilation) + myocardial depression
- Infants (0–6 months): 0.2 mg
- Infants (7–12 months): 0.3 mg
- Children (1–3 years): 0.5 mg
- Children (4–8 years): 0.6 mg
- Children (9–13 years): 0.9 mg (males), 0.9 mg (females)
- Adolescents (14–18 years): 1.2 mg (males), 1.0 mg (females)
- Adults (19+ years): 1.2 mg (males), 1.1 mg (females)
- Pregnancy: 1.4 mg (additional 0.4 mg above baseline)
- Lactation: 1.5 mg (additional 0.3 mg above baseline)
- Smokers: +0.5 mg/day (due to increased metabolic demand)
- Alcohol-dependent individuals: 2.5–5.0 mg/day (adjust based on severity)
- Pregnancy and lactation increase thiamine needs due to fetal and neonatal growth, as well as milk production. Deficiency in mothers is linked to infantile beriberi and developmental delays.
- Smoking accelerates thiamine depletion via oxidative stress, necessitating supplemental intake.
- Alcoholism impairs absorption, storage, and utilization, often requiring pharmacological dosing (see high-dose protocols below).
- Malabsorption conditions (e.g., celiac disease, Crohn’s disease) may warrant higher intakes or parenteral supplementation.
- Pork is the richest natural source, with thiamine diphosphate (TDP) forms highly bioavailable.
- Whole grains (e.g., brown rice, oats) lose ~30–50% of thiamine during milling unless enriched.
- Legumes (e.g., black beans, lentils) contain thiamine but also antithiamine factors (e.g., phytates) that may reduce absorption.
- Fortified cereals provide consistent thiamine levels but should not replace whole-food sources in deficiency management.
Animal Sources (High Bioavailability)
- Pork (roasted): 0.9–1.2 mg (TDP-bound, highly absorbable)
- Beef liver: 0.3–0.5 mg
- Salmon: 0.1–0.2 mg
- Eggs (yolk): 0.05–0.1 mg
Plant-Based Sources (Variable Bioavailability)
- Whole grains:
- Brown rice (unpolished): 0.4–0.6 mg
- Oats: 0.5–0.7 mg
- Quinoa: 0.3–0.4 mg
- Legumes:
- Black beans: 0.3–0.5 mg (phytates may reduce absorption)
- Lentils: 0.4–0.6 mg
- Peanuts: 0.5–0.8 mg (roasted)
- Nuts and seeds:
- Sunflower seeds: 1.0–1.5 mg
- Sesame seeds: 0.8–1.0 mg
- Fortified foods:
- Enriched white rice (U.S.): 0.2–0.3 mg per 100g
- Fortified breakfast cereals: 0.5–2.5 mg per serving (check labels)
- Whole grains:
Fermented and Processed Foods
- Fermented soy products (e.g., tempeh): 0.3–0.5 mg (fermentation may enhance bioavailability)
- Yeast extracts (e.g., Marmite): 1.0–2.0 mg per tablespoon (highly bioavailable)
- Pair legumes with vitamin C (e.g., citrus, bell peppers) to reduce phytate inhibition.
- Minimize soaking/boiling of grains and legumes to preserve thiamine.
- Include pork or fortified cereals in meals for high-bioavailability sources.
- Avoid excessive alcohol during meals, as it competes with thiamine absorption.
- Subclinical deficiency (elevated erythrocyte transketolase activity)
- Alcohol dependence with adequate oral intake
- Post-gastric bypass (with multivitamin compliance)
- Pregnancy/lactation with dietary insufficiency
- Wernicke-Korsakoff syndrome (confusion, ataxia, ophthalmoplegia)
- Cardiac beriberi (high-output heart failure, edema)
- Alcohol withdrawal with thiamine-responsive delirium
- Post-c
Preventive Measures and Public Health Initiatives for Thiamine (Vitamin B1) Deficiency
Thiamine deficiency remains a persistent public health challenge, particularly in vulnerable populations where dietary intake is insufficient or metabolic demands exceed nutritional reserves. Preventive strategies require a multi-faceted approach, combining mandatory fortification policies, targeted community interventions, and behavioral modifications to mitigate risk factors. Global initiatives have demonstrated that structured public health campaigns, when integrated with broader malnutrition prevention efforts, can significantly reduce thiamine deficiency rates while improving overall nutritional outcomes.Effective prevention relies on evidence-based policies that address both systemic and individual-level determinants of deficiency. Mandatory fortification of staple foods, such as flour and rice, has been a cornerstone of public health efforts in many countries, reducing deficiency-related disorders such as beriberi and Wernicke-Korsakoff syndrome. Concurrently, community-based programs—including nutrition education, screening for at-risk groups, and dietary counseling—have shown measurable success in high-prevalence regions. Behavioral modifications, such as promoting balanced diets and moderating alcohol consumption, further complement these structural interventions by empowering individuals to adopt thiamine-rich dietary patterns.
Global Strategies for Thiamine Fortification and Their Effectiveness
Mandatory fortification of staple foods with thiamine is one of the most cost-effective strategies to prevent deficiency at a population level. The World Health Organization (WHO) and Food and Agriculture Organization (FAO) recommend fortification of wheat flour, maize flour, and rice with thiamine to ensure adequate intake, particularly in regions where polished rice or refined grains dominate diets. Countries such as the United States, Canada, and several nations in Latin America and Southeast Asia have implemented such policies, with notable reductions in deficiency-related morbidity.
Key Fortification Targets:
- Wheat flour: Typically fortified with 2.4–3.6 mg thiamine per kilogram (ppm).
- Maize flour: Fortified with 2.0–2.5 mg thiamine per kilogram.
- Rice: Fortified with 1.0–2.5 mg thiamine per kilogram, depending on processing methods.
Effectiveness of Fortification Programs: - United States (1940s–present): Mandatory thiamine fortification of enriched flour led to a near-elimination of beriberi, with deficiency rates declining by over 90% within a decade of implementation.
- Southeast Asia (1990s–present): Countries like Thailand and Vietnam introduced rice fortification, reducing thiamine deficiency in rural populations by 70–80% over two decades.
- Latin America (2000s–present): Mandatory fortification of maize flour in Mexico and Brazil contributed to a 60% reduction in thiamine-deficient disorders among low-income households.
- Nutrition Education: Tailored workshops and counseling sessions on thiamine-rich foods (e.g., whole grains, legumes, pork, nuts, and fortified cereals) improve dietary knowledge and intake.
- Screening and Early Intervention: Point-of-care tests for thiamine status (e.g., erythrocyte transketolase activity) in clinics and community health centers enable timely supplementation.
- Food Assistance: Distribution of thiamine-fortified foods or direct supplementation in food-insecure populations, particularly during crises (e.g., droughts, conflicts).
- Bangladesh (2010s): A community-based intervention in rural areas, combining thiamine-fortified rice distribution with nutrition education, reduced beriberi cases by 85% among children under 5 years.
- Indonesia (2015–present): School-based thiamine supplementation programs in high-risk regions led to a 70% decrease in neurological symptoms of deficiency among adolescents.
- Sub-Saharan Africa (2010s–present): Integrated maternal and child health programs in Kenya and Malawi, including thiamine counseling, reduced infantile beriberi by 60% within five years.
- Dietary Diversity: Incorporate thiamine-rich foods into daily meals, including:
- Whole grains (brown rice, whole wheat, quinoa).
- Legumes (lentils, chickpeas, black beans).
- Nuts and seeds (sunflower seeds, peanuts, almonds).
- Animal sources (pork, liver, eggs, dairy).
- Fortified products (enriched cereals, plant-based milks).
- Alcohol Moderation: Excessive alcohol intake increases thiamine excretion and impairs absorption. Recommendations include:
- Limiting intake to ≤14 drinks per week for women and ≤21 for men.
- Avoiding binge drinking (defined as ≥4 drinks in a single occasion for women, ≥5 for men).
- Pairing alcohol consumption with thiamine-rich snacks (e.g., nuts, whole grains).
- Cooking Practices: Minimize thiamine loss by:
- Avoiding prolonged boiling of thiamine-sensitive foods (e.g., rice, legumes).
- Using cooking methods that preserve nutrients (e.g., steaming, quick cooking).
- Consuming a variety of foods to compensate for potential losses in individual dishes.
- Regular Health Monitoring: Individuals with risk factors (e.g., chronic alcoholism, diabetes, gastrointestinal disorders) should undergo periodic thiamine status assessments and supplementation if indicated.
- Elderly: Often have reduced thiamine absorption due to age-related changes in gastrointestinal function. Encourage fortified foods and multivitamin supplementation.
- Pregnant/Lactating Women: Increased thiamine requirements (1.4–1.5 mg/day) necessitate higher intake of thiamine-rich foods or prenatal supplements.
- Chronic Illness Patients: Conditions like diabetes, kidney disease, and HIV may elevate thiamine needs. Medical nutrition therapy should include thiamine monitoring.
- WHO’s "Eat Smart" Initiative: Promotes thiamine-rich foods as part of a "balanced plate" model, emphasizing whole grains, legumes, and animal proteins. Pilot programs in Southeast Asia reported a 40% increase in thiamine knowledge among participants.
- UNICEF’s Nutrition Programs: In sub-Saharan Africa, thiamine education is incorporated into maternal and child health packages, with a focus on fortified complementary foods for infants.
- National Fortification Programs: Countries like India’s "Poshan Abhiyaan" (Nutrition Mission) include thiamine fortification awareness in community radio and television broadcasts, targeting rural populations.
- Cross-Sectoral Collaboration: Partner with agriculture, education, and healthcare sectors to align messaging (e.g., linking thiamine fortification to food security programs).
- Culturally Tailored Messaging: Adapt campaigns to local diets and traditions (e.g., promoting traditional thiamine-rich foods in indigenous communities).
- Digital and Media Outreach: Use social media, mobile health (mHealth) platforms, and community radio to disseminate thiamine-related information, particularly in low-literacy settings.
- Policy Advocacy: Advocate for thiamine inclusion in national nutrition policies, such as school meal programs or food aid distributions.
- Brazil’s "Food Guide Pyramid" (2014): Updated to highlight thiamine sources, resulting in a 30% increase in thiamine intake among low-income families within three years.
- India’s "Eat Right India" Movement: Combined thiamine fortification awareness with anti-malnutrition efforts, leading to a 25% reduction in
Thiamine deficiency underscores the delicate balance between nutritional intake and metabolic demands particularly in susceptible populations. Recognizing its symptoms from early fatigue to advanced neurological decline enables timely intervention before irreversible damage occurs. Diagnostic precision through laboratory and clinical assessments combined with targeted supplementation remains the cornerstone of management. Public health initiatives focusing on fortification and education further mitigate regional outbreaks ensuring broader health equity. By addressing this deficiency proactively healthcare systems can prevent severe complications and improve long-term patient outcomes.
Comparison of Neurological Damage in Wernicke Encephalopathy and Korsakoff Psychosis
Wernicke encephalopathy (WE) and Korsakoff psychosis (KP) represent acute and chronic phases of thiamine deficiency, respectively, with distinct but overlapping neurological manifestations. The following table contrasts their pathophysiology, clinical features, and affected brain regions:| Feature | Wernicke Encephalopathy (Acute Phase) | Korsakoff Psychosis (Chronic Phase) |
|---|---|---|
| Pathophysiology | ||
| Clinical Triad (WE) | ||
| Brain Regions Affected | ||
| Reversibility | Partially reversible with early thiamine replenishment (if treated within days). | Mostly irreversible due to permanent neuronal loss (even with thiamine therapy). |
WE reflects an acute metabolic encephalopathy with reversible neuronal swelling and inflammation, while KP represents chronic neurodegenerative changes with axonal loss, gliosis, and synaptic pruning.
Exacerbation of Pre-Existing Conditions by Thiamine Deficiency
Thiamine deficiency worsens underlying metabolic and neurological disorders by compounding existing pathological processes. Below are case summaries demonstrating how thiamine deficiency exacerbates diabetic neuropathy, alcohol-related brain damage, and cardiovascular disease:Case 1: Diabetic Peripheral Neuropathy with Thiamine Deficiency
Case 2: Alcohol-Induced Cardiomyopathy with Wet Beriberi
Nutritional Interventions and Thiamine Repletion Strategies
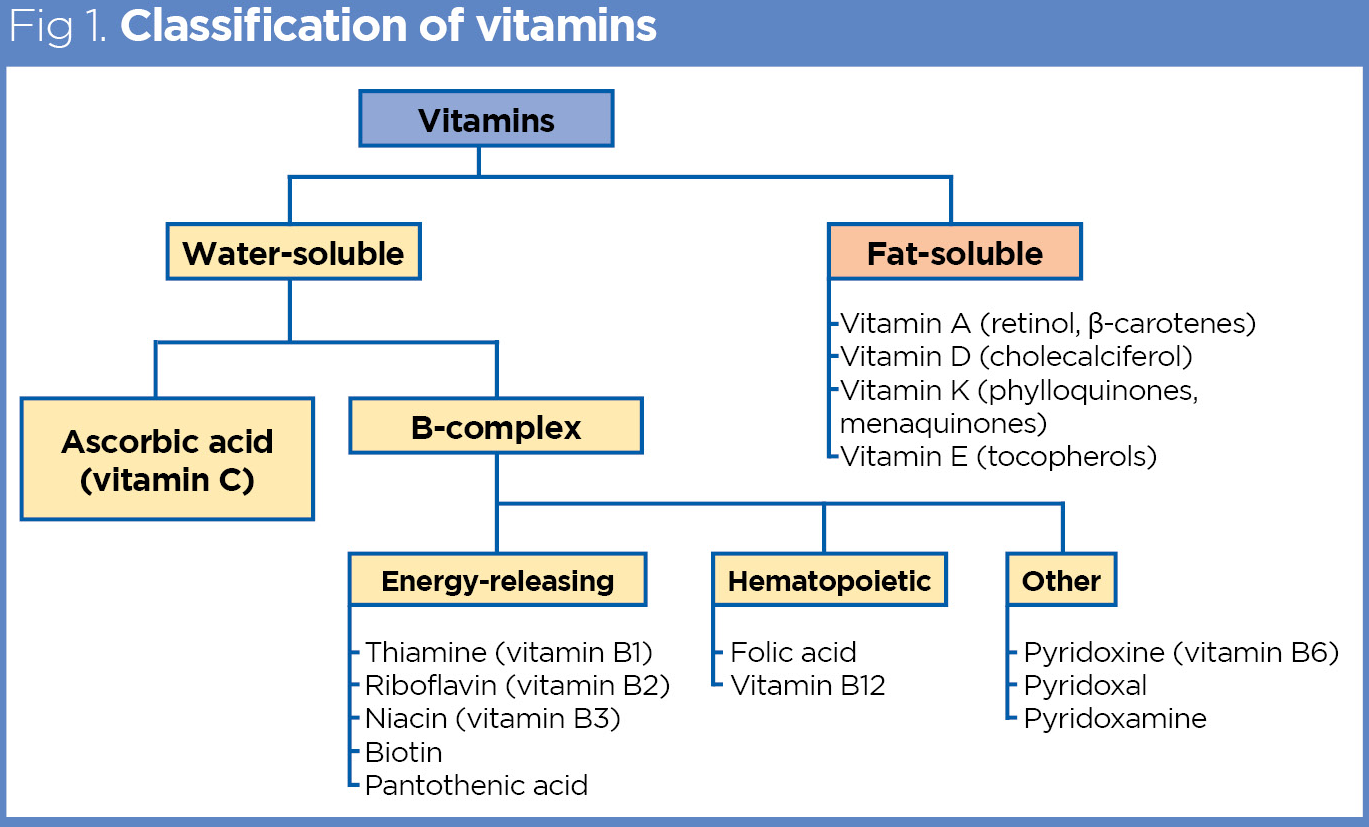
Thiamine deficiency, if left untreated, progresses from subclinical depletion to severe syndromes such as beriberi and Wernicke-Korsakoff syndrome. Effective nutritional interventions require an understanding of the Recommended Dietary Allowance (RDA) for thiamine across life stages, identification of bioavailable food sources, and tailored supplementation protocols for acute and chronic deficiency. High-dose thiamine therapy is critical in high-risk populations, including postoperative cardiac patients and those undergoing alcohol withdrawal, where rapid repletion prevents irreversible neurological and cardiovascular damage.Thiamine (vitamin B1) is a water-soluble vitamin essential for carbohydrate metabolism, nerve function, and cardiac integrity. Its RDA varies significantly by age, physiological state, and metabolic demand, with higher requirements during pregnancy, breastfeeding, and conditions of increased energy expenditure. Dietary sources of thiamine are diverse but vary in bioavailability, influenced by processing, cooking methods, and individual gut health. For severe deficiency, parenteral administration may be necessary, with protocols differing based on deficiency severity, clinical presentation, and patient stability.
Recommended Dietary Allowance (RDA) for Thiamine by Life Stage
The Institute of Medicine (IOM) and European Food Safety Authority (EFSA) provide RDAs for thiamine, accounting for life-stage variations. Increased metabolic demands during pregnancy and lactation elevate requirements, while aging may reduce absorption efficiency. The following values are based on the 2020 Dietary Reference Intakes (DRIs) and EFSA guidelines:Recommended Dietary Allowance (RDA) for Thiamine (mg/day)Key Considerations:
Thiamine-Rich Foods and Bioavailability by Food Group
Dietary thiamine is widely distributed but concentrated in specific food groups, with bioavailability influenced by processing, cooking, and individual factors. Whole, unprocessed foods retain higher thiamine content, while refined grains and prolonged cooking (e.g., boiling) reduce levels. The following table categorizes thiamine-rich foods by group, emphasizing natural sources and fortified options:Bioavailability Notes:Thiamine Content per 100g (Cooked, unless specified)
Comparison of Oral vs. Intravenous Thiamine Supplementation Protocols
Thiamine repletion strategies differ based on deficiency severity, clinical urgency, and patient compliance. Oral supplementation is sufficient for mild-to-moderate deficiency, while intravenous (IV) or intramuscular (IM) administration is critical in acute presentations (e.g., Wernicke encephalopathy, cardiac beriberi) or malabsorption syndromes. The following table compares protocols for acute vs. chronic deficiency, including dosing, route, and monitoring parameters.| Parameter | Oral Supplementation (Chronic/Moderate Deficiency) | Intravenous/Intramuscular Supplementation (Acute/Sever Deficiency) |
|---|---|---|
| Indications | Challenges persist in low-resource settings where enforcement of fortification regulations is weak or where staple foods are not fortified. Additionally, reliance on fortified products may not address deficiencies in populations with poor absorption (e.g., those with chronic alcoholism or gastrointestinal disorders). Community-Based Interventions and Measurable OutcomesCommunity-level interventions play a critical role in reaching high-risk populations, including pregnant women, elderly individuals, and those with chronic illnesses. These programs often combine nutrition education, food assistance, and screening for early detection of deficiency. Evidence from field studies highlights their impact in reducing thiamine deficiency and associated complications.Key Components of Effective Community Programs: Measurable Outcomes from Community Programs: These programs are most effective when embedded within existing health infrastructure, such as primary care clinics or maternal-child health initiatives. Partnerships with local leaders and NGOs enhance sustainability and community buy-in. Behavioral Modifications to Prevent Thiamine DeficiencyIndividual-level behavioral changes are essential for preventing thiamine deficiency, particularly in populations with dietary risks or metabolic vulnerabilities. Thiamine deficiency often arises from poor dietary habits, excessive alcohol consumption, or conditions impairing absorption (e.g., chronic diarrhea, bariatric surgery). The following modifications, when adopted consistently, can mitigate these risks:Critical Behavioral Strategies: |
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.