Virus Sincitial Respiratory Explained Comprehensively
Table of Contents
- Scientific Classification and Biological Overview of Respiratory Syncytial Virus (RSV)
- Taxonomic Classification and Key Viral Characteristics
- Replication Cycle of RSV: Host Cell Entry to Viral Egress
- Comparative Analysis of RSV Subtypes A and B
- Flowchart: RSV Lifecycle with Immune Evasion Annotations
- Epidemiology and Transmission Dynamics of Respiratory Syncytial Virus
- Global and Regional Incidence Patterns (2010–2023)
- Transmission Routes and Environmental Stability
- WHO/CDC Guidelines for RSV Outbreak Control in Healthcare Settings
- Timeline of Major RSV Epidemics and Milestones in Vaccine Development
- Clinical Manifestations and Pathophysiology of Respiratory Syncytial Virus Infection
- Spectrum of RSV Disease: Asymptomatic Infection to Severe LRTI
- Immune Responses to RSV: Innate vs. Adaptive Mechanisms and Cytokine Storms
- Age-Specific Clinical Manifestations of RSV Infection
- Diagnostic Methods and Laboratory Techniques for Respiratory Syncytial Virus Detection
- Conventional Diagnostic Assays for RSV Detection
- Molecular Diagnostic Assays for RSV Detection
- Diagnostic Algorithms for Outpatient vs. Hospitalized Patients
- Regulatory Criteria for RSV Confirmation: CDC/NIH Guidelines
The Respiratory Syncytial Virus (RSV), commonly referred to as Virus Sincitial, remains one of the most significant pathogens affecting global respiratory health, particularly among vulnerable populations. With its complex biological mechanisms and widespread epidemiological impact, RSV drives severe seasonal outbreaks annually, resulting in substantial morbidity and mortality. This virus not only challenges clinical diagnostics through its diverse subtypes and adaptive immune evasion tactics but also underscores the critical need for targeted interventions, including vaccination and infection control strategies. Understanding its taxonomic classification, replication cycle, and transmission dynamics is essential for developing effective public health responses and advancing therapeutic innovations.
From its structural intricacies—such as its segmented negative-sense RNA genome and fusion proteins—to its socioeconomic burden, RSV exemplifies the intersection of virology, epidemiology, and clinical medicine. The virus’s ability to induce cytokine storms and exacerbate chronic respiratory conditions further complicates its management, necessitating a multidisciplinary approach. By dissecting its pathophysiology, diagnostic methodologies, and evolving epidemiological trends, this analysis provides a rigorous framework for clinicians, researchers, and policymakers to address its persistent threat. The interplay between viral adaptation and host immunity also highlights the urgency of refining diagnostic tools and vaccine formulations to mitigate its global impact.
Scientific Classification and Biological Overview of Respiratory Syncytial Virus (RSV)
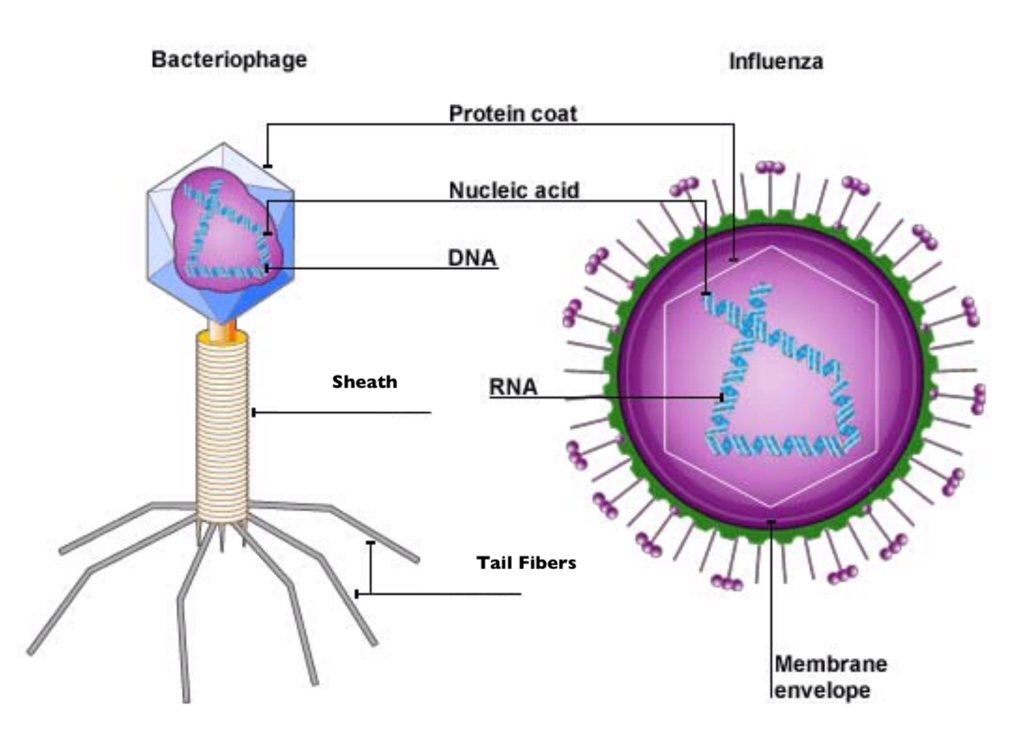
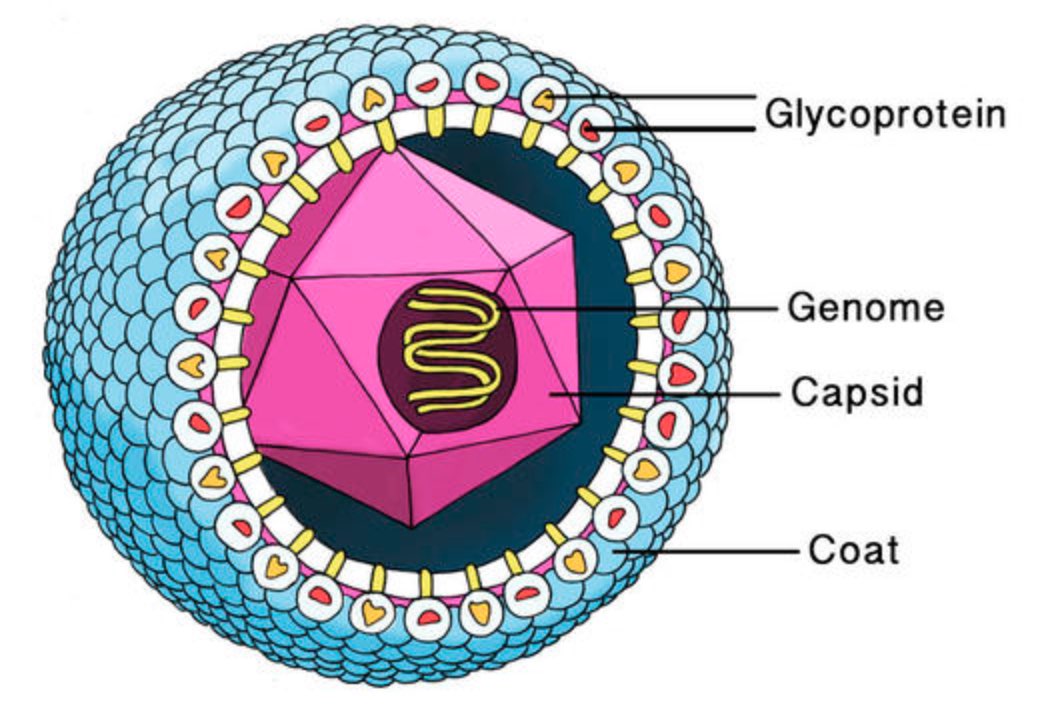
Respiratory Syncytial Virus (RSV) is a leading cause of lower respiratory tract infections in infants, the elderly, and immunocompromised individuals, with global health significance due to its high morbidity and mortality rates. Taxonomically, RSV belongs to the Pneumoviridae family, a subgroup of the Paramyxoviridae order, reflecting its unique genetic and structural features distinct from other paramyxoviruses. Understanding its biological classification, genomic organization, and replication mechanisms is critical for developing targeted therapeutic and prophylactic strategies.RSV exhibits a negative-sense, single-stranded RNA genome of approximately 15,200 nucleotides, encoding 11 proteins through a complex transcription and replication process. Its enveloped virion structure includes surface glycoproteins (G and F) that mediate host cell attachment and fusion, while the matrix (M), nucleocapsid (N), and polymerase complex (L, P, M2-1) orchestrate genomic replication and assembly. The virus’s ability to evade immune surveillance through antigenic variability and immune modulation further complicates intervention efforts.
Taxonomic Classification and Key Viral Characteristics
RSV is classified under the following taxonomic hierarchy:The virion structure comprises:
The F glycoprotein undergoes proteolytic cleavage into F1 and F2 subunits, exposing a hydrophobic fusion peptide that inserts into host membranes, facilitating viral entry. The G glycoprotein binds to cellular receptors, including CX3CR1 and Nectin-4, though its exact receptor remains debated.
Replication Cycle of RSV: Host Cell Entry to Viral Egress
The RSV replication cycle is a tightly regulated process involving multiple stages of host-virus interaction, immune evasion, and assembly. Below is a structured overview of the cycle, followed by a comparative table of subtypes and a flowchart description for visualization.Stages of the Replication Cycle:
1. Attachment and Entry
RSV initiates infection by binding to host cell receptors via the G glycoprotein, followed by F glycoprotein-mediated fusion at the plasma membrane or endosomal compartments. The F protein’s conformational changes expose the fusion peptide, merging viral and host membranes to release the nucleocapsid into the cytoplasm.
Key receptors: CX3CR1 (chemokine receptor), Nectin-4 (Ig-like cell adhesion molecule), and heparin sulfate proteoglycans (low-affinity binding).2. Transcription and Translation
The viral RNA-dependent RNA polymerase (L-P complex) transcribes the negative-sense genome into positive-sense mRNA, with a gradient of transcription favoring early genes (NS1, NS2, N, P, M2-1) over late genes (SH, G, F, M, L). Ribosomes translate these mRNAs into structural and non-structural proteins, with NS1 and NS2 inhibiting host interferon responses.
3. Replication and Assembly
The N protein encapsidates newly synthesized genomic RNA, forming nucleocapsids that associate with M proteins at the Golgi apparatus. Viral glycoproteins (F, G) are trafficked via the secretory pathway, while the SH (small hydrophobic) protein may modulate immune signaling. Assembly occurs at the Golgi, where budding virions acquire their envelope.
4. Egress and Immune Evasion
Mature virions exit via exocytosis, often exploiting host cell apoptosis or syncytia formation (multinucleated giant cells) to spread. RSV employs immune evasion tactics such as:
Comparative Analysis of RSV Subtypes A and B
RSV subtypes A and B exhibit distinct antigenic and epidemiological profiles, influencing vaccine design and surveillance strategies. The following table summarizes key differences:| Subtype | Antigenic Drift Rate | Clinical Severity Trends | Geographic Prevalence | Vaccine Strain Compatibility |
|---|---|---|---|---|
| A | Higher drift in G glycoprotein (hypervariable regions), with GON.1 and GA2 lineages showing rapid evolution. Recombination events (e.g., A/BA lineage) introduce novel epitopes. | Associated with more severe disease in infants, particularly in first-time infections. Higher hospitalization rates in epidemics dominated by A. | Global dominance in outbreaks, with A/B alternation in seasonal patterns. A subtypes often predominate in temperate climates (e.g., U.S., Europe). | Current vaccines (e.g., RSVpreF, mRNA-1345) target conserved F protein epitopes but may require subtype-specific G glycoprotein updates for broad coverage. |
| B | Lower drift than A, but BA lineage (e.g., BA.9, BA.10) exhibits unique G glycoprotein sequences with duplication of hypervariable regions, enhancing immune escape. | Generally less severe than A in infants, but BA lineages have been linked to increased disease in adults/elderly (e.g., 2018–2019 outbreaks in Australia). | More prevalent in tropical/subtropical regions (e.g., Latin America, Asia) and may co-circulate with A in temperate zones. BA lineages are emerging as dominant in some areas. | BA lineages pose challenges due to unique G glycoprotein epitopes; ongoing trials evaluate bivalent vaccines (A/B strains) or pan-pneumovirus approaches. |
Note: Subtype classification is based on G glycoprotein sequencing, but F protein conservation (~90% identity between A/B) supports cross-subtype immunity via neutralizing antibodies.
Flowchart: RSV Lifecycle with Immune Evasion Annotations
Below is a step-by-step description for implementing a flowchart in HTML/CSS, including annotations for immune evasion mechanisms. The flowchart should visually depict the following stages with corresponding annotations:1. Attachment
2. Fusion and Entry
3. Uncoating and Transcription
4. Translation and Replication
5. Assembly and Egress
Epidemiology and Transmission Dynamics of Respiratory Syncytial Virus
Respiratory Syncytial Virus (RSV) remains a leading cause of acute lower respiratory infections (ALRI) globally, with significant morbidity and mortality across all age groups, though disproportionately affecting infants, the elderly, and immunocompromised populations. Epidemiological patterns reveal distinct seasonal trends, regional variations in incidence, and critical transmission pathways influenced by environmental stability and human behavior. Understanding these dynamics is essential for targeted public health interventions, outbreak preparedness, and resource allocation in healthcare settings.The global burden of RSV has been systematically documented through surveillance systems, including the WHO Global RSV Surveillance Network and CDC’s Respiratory and Enteric Virus Surveillance System (REVSS). Data from 2010 to 2023 highlight persistent seasonal epidemics, with peak activity occurring during winter months in temperate climates and during rainy seasons in tropical regions. Age-specific attack rates demonstrate that nearly all children experience RSV infection by age 2, with reinfections occurring throughout life, particularly in high-risk groups.
Global and Regional Incidence Patterns (2010–2023)
Annual RSV-related hospitalizations and mortality rates vary by region, reflecting differences in healthcare infrastructure, surveillance capacity, and demographic factors. The WHO estimates that RSV causes 33 million acute lower respiratory infections (ALRI), 3.6 million hospital admissions, and 101,400 in-hospital deaths annually in children under 5 years old, with the highest burden in Sub-Saharan Africa and South Asia. In high-income countries, RSV accounts for 1–2% of all-cause mortality in adults ≥65 years, with immunocompromised individuals facing elevated risks of severe disease.Seasonal Trends:
Age-Specific Attack Rates:
High-Risk Populations:
Transmission Routes and Environmental Stability
RSV primarily transmits through direct contact, large respiratory droplets, and fomites, with environmental persistence influencing secondary transmission. The virus exhibits moderate stability on surfaces and in aerosols, necessitating stringent infection control measures in healthcare and community settings.Primary Transmission Mechanisms:
Quantitative Risk Factors:
Environmental Stability Data:
WHO/CDC Guidelines for RSV Outbreak Control in Healthcare Settings
Healthcare-associated RSV outbreaks pose significant risks to vulnerable populations, particularly in pediatric wards, neonatal intensive care units (NICUs), and long-term care facilities. The following protocols, endorsed by the World Health Organization (WHO) and Centers for Disease Control and Prevention (CDC), emphasize source control, environmental hygiene, and cohorting strategies to mitigate transmission.WHO/CDC Core Recommendations for RSV Outbreak Control:
1. Isolation and Cohorting:
Implement strict respiratory hygiene/cough etiquette (e.g., masks for symptomatic individuals, dedicated patient areas). Cohort patients by diagnosis (RSV-positive vs. RSV-negative) to limit cross-contamination. Delay elective procedures during peak RSV seasons to reduce hospital exposure. 2. Environmental and Hand Hygiene:
Disinfect high-touch surfaces (e.g., beds, equipment, toys) daily with EPA-approved virucides (e.g., bleach, quaternary ammonium compounds). Enforce hand hygiene compliance (>90%) among staff, with alcohol-based sanitizers (60–95% ethanol) for RSV inactivation. Ultraviolet (UV) germicidal irradiation (UVGI) in HVAC systems may reduce airborne viral load. 3. Personal Protective Equipment (PPE):
Healthcare personnel (HCP) caring for RSV-positive patients should use: Surgical masks (for droplet precautions). N95 respirators if performing aerosol-generating procedures (e.g., intubation, nebulization). Gloves and gowns for contact precautions with diapered infants or incontinent patients. 4. Surveillance and Reporting:
Enhance laboratory testing via rapid antigen tests or PCR to confirm cases promptly. Report outbreaks (≥2 cases in a 7-day period) to public health authorities for contact tracing and resource allocation. Exclude symptomatic HCP from patient care until 24 hours after symptom resolution. 5. Vaccination and Prophylaxis:
Administer palivizumab (monoclonal antibody) to high-risk infants (e.g., <29 weeks gestation, chronic lung disease). Pilot maternal RSV vaccines (e.g., Pfizer’s RSVpreF) in pregnant women to confer passive immunity to newborns. Encourage annual influenza and COVID-19 vaccination to reduce co-infection risks and healthcare burden. 6. Staff Training and Education:
Conduct quarterly training on RSV transmission, PPE use, and outbreak response protocols. Simulate drills for rapid cohorting, disinfection, and patient flow adjustments during surges.
Timeline of Major RSV Epidemics and Milestones in Vaccine Development
Clinical Manifestations and Pathophysiology of Respiratory Syncytial Virus Infection
Respiratory Syncytial Virus (RSV) exhibits a broad spectrum of clinical presentations, ranging from asymptomatic or mild upper respiratory tract infections (URTI) to severe lower respiratory tract illnesses (LRTI), including bronchiolitis and pneumonia. The severity of disease correlates with age, immune status, and underlying comorbidities, with infants, elderly individuals, and immunocompromised patients at highest risk for complications. Pathophysiologically, RSV disrupts airway epithelial integrity, triggers excessive inflammatory responses, and induces structural remodeling, particularly in susceptible populations. Immune dysregulation, including aberrant cytokine production and impaired adaptive immunity, further exacerbates disease progression and long-term respiratory morbidity.The clinical manifestations of RSV infection are highly age-dependent, with distinct symptom profiles and prognostic implications. Immune responses to RSV involve a complex interplay between innate and adaptive immunity, where dysregulated cytokine storms—particularly involving interleukin-6 (IL-6) and interferon-gamma (IFN-γ)—contribute to tissue damage and disease severity. Reinfection in later life often results in persistent airway inflammation and immune dysregulation, predisposing individuals to recurrent exacerbations of chronic respiratory conditions.
Spectrum of RSV Disease: Asymptomatic Infection to Severe LRTI
The clinical presentation of RSV infection varies significantly across the lifespan, with asymptomatic or mild symptoms observed in approximately 30–50% of infected individuals, particularly in older children and adults. However, severe disease—characterized by bronchiolitis, pneumonia, or respiratory failure—predominantly affects infants (<6 months), elderly adults (>65 years), and immunocompromised patients. The progression from URTI to LRTI involves viral replication in nasal epithelial cells, followed by dissemination to the lower respiratory tract, where immune-mediated damage to the airway epithelium and alveoli occurs.Key mechanisms of organ-specific damage in RSV infection include:
In immunocompromised patients, RSV can disseminate beyond the respiratory tract, causing hemorrhagic pneumonia, hepatitis, or encephalitis, with mortality rates exceeding 10–20% in transplant recipients or HIV-infected individuals.
Immune Responses to RSV: Innate vs. Adaptive Mechanisms and Cytokine Storms
The immune response to RSV is biphasic, involving an initial innate immune activation followed by a delayed adaptive response, both of which can become dysregulated. Innate immunity relies on pattern recognition receptors (PRRs) such as TLR3, TLR4, and RIG-I, which detect RSV nucleocapsid and fusion proteins, triggering the production of type I/III interferons (IFNs). However, RSV employs immune evasion strategies, including NS1 and NS2 proteins, which inhibit IFN signaling and promote viral persistence.Adaptive immunity is characterized by:
Cytokine storms are a critical pathological feature of severe RSV disease, particularly in infants and elderly patients. Excessive production of:
Chronic exposure to RSV in reinfected individuals leads to immune exhaustion, where repeated Th2-biased responses contribute to airway hyperreactivity, mucus hypersecretion, and structural remodeling, akin to asthma or COPD.
Age-Specific Clinical Manifestations of RSV Infection
The following table compares the clinical features of RSV infection across key age groups, highlighting symptom frequency, duration, and complications. Data are derived from pediatric and geriatric cohorts, with adjustments for immunocompromised populations.| Symptom | Infants (<6 months) | Children (6–24 months) | Adults (>65 years) | Immunocompromised Patients |
|---|---|---|---|---|
| Fever | 80–90% Duration: 3–7 days |
60–70% Duration: 2–5 days |
40–60% Duration: 1–3 days |
50–70% Duration: ≥7 days (persistent) |
| Rhinitis/Coryza | 95% Duration: 5–10 days |
90% Duration: 4–7 days |
70–80% Duration: 3–5 days |
60–80% Duration: ≥10 days |
| Cough | 100% Duration: 10–14 days |
95% Duration: 7–10 days |
80% Duration: 5–7 days |
90% Duration: ≥14 days (paroxysmal) |
| Wheezing | 70–80% Duration: 5–10 days Complications: Apnea (preterm), respiratory failure |
40–50% Duration: 3–7 days Complications: Recurrent wheezing |
20–30% Duration: 3–5 days Complications: Exacerbation of COPD |
30–50% Duration: ≥10 days Complications: Progressive pneumonia |
| Tachypnea/Respiratory Distress | 60–70% Duration: 3–7 days Complications: Hypoxemia, ICU admission (10–15%) |
20–30% Duration: 2–5 days Complications: Bronchiolitis obliterans (rare) |
30–40% Duration: 1–3 days Complications: Exacerbation of heart failure |
50–70% Duration: ≥7 days Complications: ARDS (10–20%) |
| Pneumonia | 10–15% Duration: 7–14 days Complications: Bacterial superinfection |
5–10% Duration: 5–10 days |
10–20% Duration: 7–14 days Com Diagnostic Methods and Laboratory Techniques for Respiratory Syncytial Virus DetectionRespiratory Syncytial Virus (RSV) infection requires precise and timely diagnosis to guide clinical management, particularly in vulnerable populations such as infants, elderly individuals, and immunocompromised patients. Diagnostic approaches range from rapid point-of-care tests to highly sensitive molecular assays, each with distinct advantages in terms of turnaround time, cost, and applicability in different healthcare settings. The selection of diagnostic method depends on clinical presentation, patient risk factors, and resource availability, with outpatient and hospitalized patients often requiring different testing strategies.The evolution of RSV diagnostics has transitioned from serological methods to advanced molecular techniques, while emerging technologies continue to redefine detection limits and accessibility. This section explores conventional and molecular assays, their performance characteristics, and diagnostic algorithms tailored to clinical scenarios, alongside regulatory criteria for RSV confirmation and the role of innovative technologies in expanding diagnostic capabilities. Conventional Diagnostic Assays for RSV DetectionConventional diagnostic methods for RSV primarily rely on antigen detection and serological testing, which remain valuable in resource-limited settings or as adjuncts to molecular confirmation. These assays are characterized by their rapid execution, low cost, and ease of use, though they often exhibit lower sensitivity compared to nucleic acid amplification techniques.Rapid Antigen Detection Tests (RADTs) Serological Methods (IgM/IgG Titers) Virus Isolation in Cell Culture Molecular Diagnostic Assays for RSV DetectionNucleic acid amplification techniques (NAATs) have become the gold standard for RSV detection due to their superior sensitivity, ability to quantify viral load, and capacity to detect non-infectious virus. These assays are particularly valuable in hospitalized patients, immunocompromised individuals, and during outbreaks where early diagnosis influences infection control measures.Conventional Polymerase Chain Reaction (PCR) Real-Time Reverse Transcription PCR (rRT-PCR) Digital PCR (dPCR) Diagnostic Algorithms for Outpatient vs. Hospitalized PatientsThe selection of diagnostic tests for RSV depends on the clinical setting, patient risk, and resource constraints. Algorithms integrate clinical presentation, epidemiological context, and test performance to optimize diagnostic efficiency.Outpatient Settings 2. High-risk patient with symptoms: Perform rapid antigen test. Hospitalized Patients 2. Moderate symptoms with comorbidities: Use rapid antigen test; if positive, confirm with PCR. 3. Immunocompromised patients: Perform PCR with extended duration of viral shedding in mind (up to 30 days post-symptom onset). Resource-Limited Settings Regulatory Criteria for RSV Confirmation: CDC/NIH GuidelinesDiagnostic standards for RSV vary between clinical and research settings, with the Centers for Disease Control and Prevention (CDC) and National Institutes of Health (NIH) providing distinct criteria for confirmation. These differences reflect the need for precision in epidemiological studies versus practical patient care.CDC Criteria for RSV Confirmation (Clinical Settings) |
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.