| Sensory Dermatomes |
e.g., L4: Medial malleolus; S1: Lateral foot |
Assess radicul
Exam-Specific Study Techniques for Anatomy in Nursing
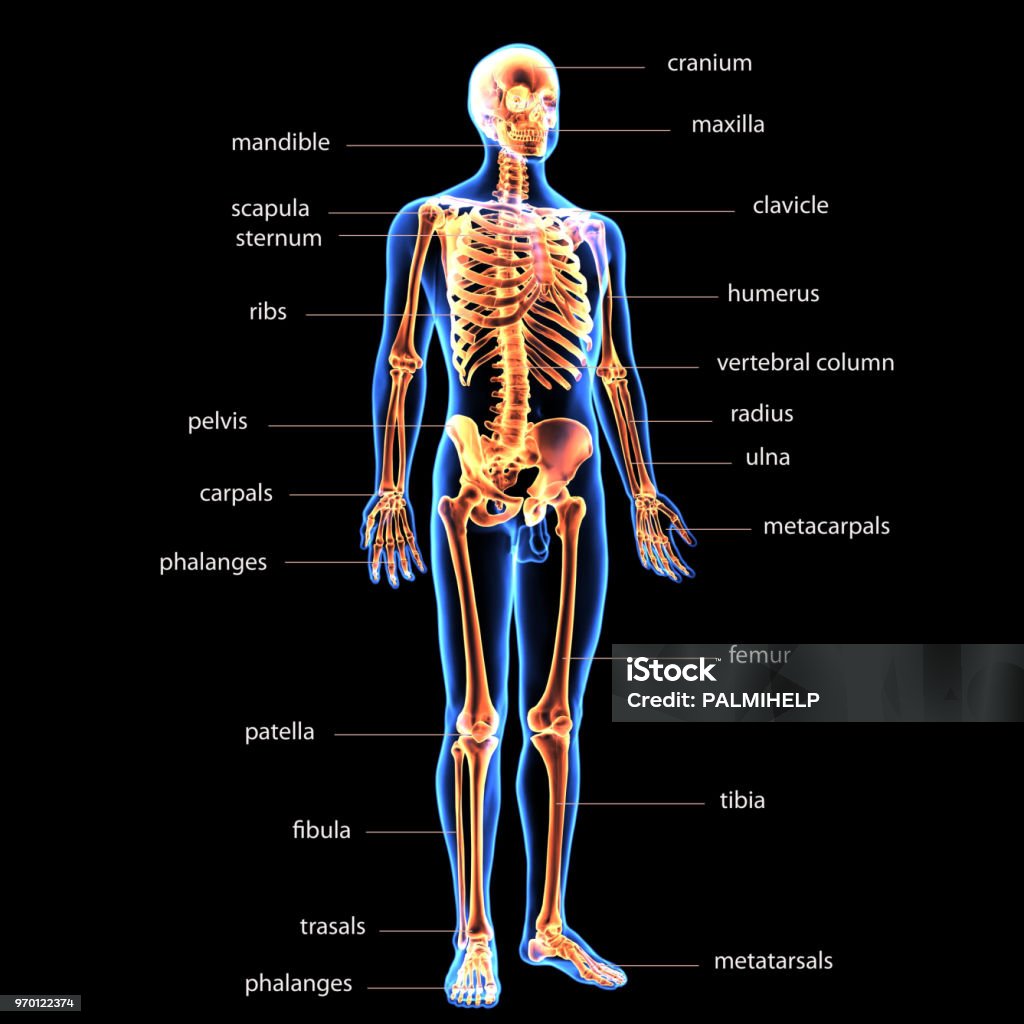
Anatomy in nursing requires precise memorization of complex structures, pathways, and clinical applications, making targeted study techniques essential for exam success. Active recall methods, digital tools, and cognitive aids enhance retention and application skills, particularly in high-stakes assessments like the Anatomi Eksamen Sykepleie. This section provides structured techniques, comparative analyses, and practical templates to optimize learning efficiency and accuracy.
Active Recall Methods for Memorizing Anatomical Terms and Structures
Active recall—retrieving information from memory rather than passive review—strengthens neural pathways and improves long-term retention. Below are evidence-based techniques tailored for nursing-relevant anatomy, with step-by-step implementation.Flashcards (Physical or Digital)
Flashcards leverage the testing effect, where self-quizzing improves memory consolidation. For anatomy, focus on:
Terminology: Latin/Greek roots (e.g., cardio- for heart, gastr- for stomach).
Structures: Labels with brief descriptions (e.g., "Biceps brachii: Origin—coracoid process; Insertion—radial tuberosity").
Clinical Correlations: Pair anatomy with conditions (e.g., "Median nerve injury → Ape hand deformity").Implementation Steps:
1. Create High-Yield Cards: Prioritize structures frequently tested (e.g., cranial nerves, major blood vessels, muscle groups).
2. Use the Leitner System: Organize cards into boxes based on recall difficulty; review weaker cards more frequently.
3. Add Visual Cues: Include simple sketches (e.g., nerve pathways) or color codes (e.g., red for arteries, blue for veins).
4. Active Recall Sessions: Shuffle cards and test yourself without peeking; aim for 3–5 correct answers in a row before moving to the next set.
5. Review Timing: Space sessions using the 24-hour rule (review within 24 hours of initial learning) and weekly intervals for long-term retention. Spaced Repetition Software (Anki, Quizlet)
Spaced repetition algorithms optimize review timing based on individual forgetting curves. For anatomy:
Decks: Use pre-built nursing anatomy decks or create custom ones with cloze deletions (e.g., "The ______ nerve innervates the diaphragm" → "phrenic").
Fields: Add tags for categories (e.g., #Musculoskeletal, #Neurology) to filter reviews.
Audio/Visual Media: Embed pronunciation guides (e.g., "Say ‘splenius capitis’") or 3D model links.Implementation Steps:
1. Input High-Frequency Terms: Start with 50–100 critical terms (e.g., all cranial nerves, major lymph nodes).
2. Set Review Intervals: Default to 1 day, then adjust based on recall accuracy (e.g., easy = 7 days; difficult = 1 day).
3. Add Contextual Clues: Include mnemonics or clinical tips (e.g., "CN XII (Hypoglossal) → ‘Hypo’ = tongue").
4. Mobile Sync: Enable offline access for review during commutes or breaks.
5. Weekly Analytics: Track weak areas (e.g., "I consistently miss the brachial plexus branches"). Interleaving Practice
Interleaving—mixing different topics in a single study session—enhances discrimination between similar concepts (e.g., distinguishing the femoral nerve from the sciatic nerve). For anatomy:
Example Session: Alternate between labeling a diagram of the abdominal quadrants, memorizing the layers of the skin, and recalling the pathway of the vagus nerve.
Benefit: Reduces illusion of mastery (thinking you know a topic after passive review).Implementation Steps:
1. Block Topics by System: Group related systems (e.g., cardiovascular, respiratory) but interleave subtopics (e.g., heart anatomy → lung volumes → blood vessels).
2. Use Timed Drills: Spend 10–15 minutes per interleaved topic to maintain focus.
3. Apply to Clinical Scenarios: "A patient presents with ptosis. Which cranial nerve is likely affected?" (Answer: CN III).
Comparative Analysis: Traditional Textbooks vs. Interactive Digital Tools
Textbooks and digital tools serve distinct learning needs, with trade-offs in engagement, depth, and accessibility. Below is a structured comparison for nursing anatomy students, focusing on efficiency, retention, and clinical relevance.
| Feature |
Traditional Textbooks (e.g., Gray’s Anatomy for Students, Netter’s Atlas) |
Interactive Digital Tools (e.g., Visible Body Suite, Complete Anatomy, AnatomyZone) |
|---|
| Strengths |
- Comprehensive Depth: Detailed explanations, historical context, and research citations for advanced learners.
- Portability: Physical copies allow offline study without screen fatigue.
- Structured Progression: Logical chapter organization (e.g., systemic → regional anatomy).
- Clinical Correlations: Integrated case studies and pathology links (e.g., "How a ruptured Achilles tendon affects gait").
- Cost-Effective: Used copies or library access reduce expenses for long-term reference.
|
- Visual Engagement: 3D rotatable models, animations (e.g., muscle contractions, blood flow), and AR/VR simulations.
- Active Learning: Quizzes with adaptive difficulty, labeling exercises, and scenario-based questions.
- Real-Time Feedback: Immediate corrections for mislabeled diagrams or incorrect pathways.
- Clinical Integration: Tools like Complete Anatomy link structures to procedures (e.g., "Where to palpate the radial pulse").
- Accessibility: Cloud-based access on multiple devices; some offer offline modes.
|
| Weaknesses |
- Static Content: Limited interactivity; requires supplementary resources (e.g., flashcards) for active recall.
- Outdated Illustrations: Some editions lack modern imaging (e.g., MRI/CT correlations).
- Passive Learning Risk: Highlighting text without testing may lead to false confidence.
- Bulkiness: Carrying multiple textbooks is impractical for clinical rotations.
|
- Subscription Costs: Annual fees for premium features (e.g., $50–$100/year).
- Screen Overload: Excessive visual stimuli may reduce focus on core concepts.
- Learning Curve: Some tools (e.g., Primal Pictures) require time to navigate menus.
- Distraction Risk: Gamification (e.g., points, badges) may prioritize engagement over depth.
|
| Best For |
- Students who prefer linear, detailed study (e.g., reviewing for comprehensive exams).
- Those needing offline access in clinical settings (e.g., no Wi-Fi).
- Learners who benefit from writing notes (e.g., hand-drawn diagrams).
|
- Visual and kinesthetic learners who retain information through movement and interaction.
- Students with limited study time who need efficient recall tools.
- Those preparing for OSCEs or practical exams with hands-on anatomy components.
|
| Hybrid Approach Recommendation |
Use textbooks for foundational knowledge and clinical context, then reinforce with digital tools for active practice. Example:- Read a
Clinical Applications of Anatomy in Nursing Practice
Anatomy serves as the foundational framework for nursing interventions, particularly in emergency and procedural care, where precise knowledge of anatomical landmarks ensures patient safety and efficacy. Nurses rely on anatomical structures to perform life-saving techniques, administer treatments, and adapt care plans to individual patient variations. This section explores critical anatomical structures in emergency interventions, procedural adaptations across populations, and the impact of anatomical variations on standard assessments. Additionally, it examines how anatomical knowledge enhances patient education, bridging clinical expertise with patient understanding.
Top 10 Anatomical Structures Nurses Must Recognize in Emergency Interventions
During emergencies, anatomical landmarks guide rapid and accurate interventions. Misidentification can lead to complications such as nerve damage, vascular injury, or ineffective treatment. Below are the 10 most critical structures, their clinical significance, and associated procedures:Anatomical knowledge in emergencies prioritizes structures that influence airway management, circulation, and access to vital regions. Errors in identifying these landmarks can result in delayed care or iatrogenic harm. For example, incorrect placement of a central venous catheter (CVC) near the brachiocephalic vein or right atrium may cause pneumothorax or cardiac tamponade, whereas proper identification of the jugular venous pulse aids in assessing volume status.
-
Sternoclavicular Joint and Suprasternal Notch
- Clinical Significance: Landmark for tracheostomy tube placement, cricothyroidotomy, and central line insertion via the internal jugular vein.
- Procedure Context: The suprasternal notch aligns with the second thoracic vertebra (T2), guiding needle insertion for internal jugular access. Misplacement risks carotid artery puncture.
- Emergency Use: Critical in airway emergencies (e.g., laryngeal edema) where tracheostomy may be required.
-
Xiphoid Process and Costal Cartilages (5th–7th Ribs)
- Clinical Significance: Reference point for cardiopulmonary resuscitation (CPR) hand placement and pericardiocentesis.
- Procedure Context: The xiphoid process marks the lower sternal border; compressions above it avoid liver/spleen injury. In obese patients, palpation may require deeper pressure.
- Emergency Use: Improper hand placement during CPR can cause rib fractures or abdominal organ damage.
-
Carotid Pulse Points (Anterior to Sternocleidomastoid Muscle)
- Clinical Significance: Primary site for assessing circulatory status in cardiac arrest or shock.
- Procedure Context: Palpation of the common carotid artery (midway between sternal head and clavicular head of SCM) avoids compression of the internal jugular vein.
- Emergency Use: Absent pulse here indicates need for immediate defibrillation or advanced airway management.
-
Antecubital Fossa (Median Cubital Vein, Basilic/Brachial Veins)
- Clinical Significance: Primary site for intravenous (IV) access, blood draws, and central line insertion.
- Procedure Context: The median cubital vein lies superficial to the brachial artery; ultrasound guidance may be needed in obese or dehydrated patients.
- Emergency Use: Rapid IV access is critical in sepsis or anaphylaxis to administer fluids/medications.
-
Femoral Triangle (Femoral Artery, Vein, and Nerve)
- Clinical Significance: Landmark for intraosseous (IO) access (in emergencies) and femoral line placement.
- Procedure Context: The femoral artery lies lateral to the inguinal ligament; IO needles target the medial femoral condyle (avoiding the adductor canal).
- Emergency Use: IO access is used when IV access fails (e.g., burn patients or cardiac arrest).
-
Lateral Malleolus (Posterior Tibial and Dorsalis Pedis Arteries)
- Clinical Significance: Sites for peripheral pulse checks and arterial blood gas sampling.
- Procedure Context: The posterior tibial artery runs behind the medial malleolus; the dorsalis pedis artery is palpable lateral to the extensor hallucis longus tendon.
- Emergency Use: Absent pulses here may indicate acute limb ischemia or shock.
-
Cricoid Cartilage and Thyrocricoid Membrane
- Clinical Significance: Landmark for cricothyroidotomy in airway obstruction.
- Procedure Context: The cricoid ring is the only complete cartilage ring of the trachea; incision here avoids esophageal puncture.
- Emergency Use: Used in upper airway obstruction (e.g., angioedema) when endotracheal intubation fails.
-
Iliac Crest and Anterior Superior Iliac Spine (ASIS)
- Clinical Significance: Guides spinal needle insertion (e.g., lumbar puncture) and pelvic assessments.
- Procedure Context: The iliac crest aligns with the L4 vertebra; spinal taps avoid the cauda equina (below L2).
- Emergency Use: Critical in meningitis or subarachnoid hemorrhage for CSF analysis.
-
Axillary Artery and Brachial Plexus (Erb’s Point)
- Clinical Significance: Landmark for axillary artery catheterization and assessing brachial plexus injuries.
- Procedure Context: Erb’s point (where the upper, middle, and lower trunks of the brachial plexus emerge) is palpated 2 cm above the clavicle.
- Emergency Use: Used in shoulder dislocations or stroke rehabilitation assessments.
-
Umbilicus and Rectus Abdominis Muscle
- Clinical Significance: Landmark for peritoneal dialysis catheter insertion and assessing abdominal trauma.
- Procedure Context: The umbilicus overlies the aorta and inferior vena cava; blind catheter insertion risks vascular injury.
- Emergency Use: Critical in peritonitis or end-stage renal disease for fluid drainage.
Anatomical Basis of Common Nursing Procedures Across Patient Populations
Nursing procedures must account for anatomical differences in pediatric, geriatric, obese, and pregnant populations. Variations in tissue density, vascular accessibility, and organ positioning necessitate adjustments to standard techniques. Below are comparisons for urinary catheterization, wound care, and IV insertion, with population-specific considerations.Standard urinary catheterization relies on anatomical landmarks such as the urethral meatus, pubic symphysis, and bladder neck. However, these landmarks vary significantly across populations due to differences in pelvic structure, muscle tone, and hormonal influences. For instance, prostate enlargement in older males alters urethral angles, while pelvic organ prolapse in postpartum women may obscure the urethral opening.
Key Principle: "Anatomical adaptations in procedures must prioritize patient safety, minimize discomfort, and maintain sterility."
-
Urinary Catheterization
-
Pediatric Patients (Infants/Children)
- Anatomical Adjustment: Shorter urethra (3–4 cm in females, 1–2 cm in males) increases risk of urethral trauma during insertion.
- Technique Modification: Use smaller catheters (5–8 Fr), sterile lubricant, and gentle traction on the penis in males to align the urethra.
- Rationale: Over-insertion can cause false passages or bladder perforation.
-
Geriatric Patients (Males with BPH)
- Anatomical Adjustment: Enlarged prostate compresses the urethra, creating a narrowed lumen and acute angle at the bladder neck.
- Technique Modification: Coude-tip catheter
Common Pitfalls and Misconceptions in Anatomy Exams for Nursing Students
Anatomy exams in nursing education often reveal persistent misconceptions that stem from oversimplifications, ambiguous terminology, or misapplied clinical correlations. These errors frequently result in lost marks, particularly in high-stakes assessments where precision is critical. Addressing these pitfalls requires a structured approach to clarify anatomical principles, identify high-risk topics, and refine exam question interpretation. This section focuses on debunking five widespread misconceptions, outlining high-risk anatomical areas prone to errors, and providing strategies to avoid ambiguity in exam questions.
Five Common Misconceptions in Anatomy and Their Corrections
Misconceptions in anatomy often arise from conflating functional similarities with structural differences or misremembering exceptions. Below are five frequent errors, framed as actionable corrections to reinforce accurate understanding.
-
Misconception: "All veins carry deoxygenated blood."
Correction: While most systemic veins transport deoxygenated blood to the heart, pulmonary veins carry oxygenated blood from the lungs to the left atrium. Additionally, umbilical veins in fetal circulation carry oxygenated blood from the placenta to the fetus.
Nursing relevance: This distinction is critical when assessing oxygen saturation in different vascular systems (e.g., central venous vs. arterial lines) or interpreting fetal monitoring data.
-
Misconception: "The aorta is the only artery supplying the heart."
Correction: The heart receives blood primarily via the coronary arteries (left and right), which branch from the aortic root. The aorta itself is a conduit for systemic circulation and does not directly supply cardiac tissue.
Nursing relevance: Confusion here can lead to misdiagnosis of coronary artery disease (CAD) or improper placement of coronary artery bypass grafts (CABG). Always specify the coronary arteries when discussing cardiac perfusion.
-
Misconception: "The diaphragm is the primary muscle of respiration."
Correction: While the diaphragm initiates inhalation by contracting and flattening, the external intercostal muscles (and accessory muscles like the sternocleidomastoid during exertion) also play essential roles in expanding the thoracic cavity. Exhalation is typically passive but involves internal intercostal muscles during forced expiration.
Nursing relevance: Patients with diaphragm paralysis (e.g., due to phrenic nerve injury) rely on intercostal muscle function, requiring tailored respiratory support strategies.
-
Misconception: "Lymph nodes filter all lymph fluid before it returns to circulation."
Correction: Lymph nodes filter lymph selectively, removing pathogens, debris, and cancer cells via immune surveillance. However, not all lymph passes through nodes; some bypasses nodes entirely (e.g., lymph from the gastrointestinal tract via lacteals drains into the thoracic duct but may not encounter all nodes).
Nursing relevance: Understanding this helps in interpreting lymph node biopsies (e.g., sentinel node mapping in breast cancer) and assessing lymphatic obstruction (e.g., lymphedema post-mastectomy).
-
Misconception: "The sympathetic and parasympathetic nervous systems have equal influence on all organs."
Correction: The autonomic nervous system exhibits organ-specific dominance. For example:- Sympathetic: Predominates in "fight-or-flight" responses (e.g., increased heart rate, bronchodilation).
- Parasympathetic: Dominates "rest-and-digest" functions (e.g., salivation, digestion via vagus nerve).
- Exceptions: Sweat glands receive only sympathetic innervation (cholinergic), while blood vessels have sympathetic-only control (adrenergic).
Nursing relevance: Misapplying this can lead to errors in pharmacology (e.g., administering beta-blockers for hypertension without considering parasympathetic rebound) or patient assessment (e.g., misinterpreting bradycardia as parasympathetic dominance vs. drug-induced).
High-Risk Anatomical Topics and Exam Question Patterns
Certain anatomical systems and question types consistently result in lost marks due to their complexity or ambiguity. Below is a checklist of high-risk areas, common exam question patterns, and strategies to mitigate errors.
-
Anatomical Systems with High Error Rates:
-
Cardiovascular System:
- Coronary artery anatomy (e.g., left anterior descending [LAD] vs. right coronary artery [RCA] territories).
- Valvular function (e.g., aortic vs. pulmonary valve closure timing in heart sounds).
- Fetal circulation shunts (e.g., ductus arteriosus vs. foramen ovale).
-
Nervous System:
- Cranial nerve pathways (e.g., distinguishing CN IX [glossopharyngeal] vs. CN X [vagus] in swallowing).
- Spinal cord injury levels (e.g., C4 vs. T6 paraplegia implications for respiratory support).
- Autonomic plexuses (e.g., celiac vs. superior mesenteric plexus in visceral innervation).
-
Respiratory System:
- Bronchial tree divisions (e.g., right vs. left lung lobes and their clinical relevance in pneumonia or lobectomy).
- Gas exchange surfaces (e.g., alveoli vs. respiratory bronchioles in COPD pathology).
-
Renal/Urinary System:
- Nephron anatomy (e.g., loop of Henle vs. collecting duct in concentrating urine).
- Ureteral pathways (e.g., retroperitoneal location and implications for kidney stone passage).
-
Musculoskeletal System:
- Joint stability vs. mobility (e.g., ball-and-socket [hip] vs. hinge [elbow] joints in fracture management).
- Muscle innervation (e.g., femoral vs. obturator nerve palsies in hip surgery).
-
Common Exam Question Patterns Leading to Errors:
-
Scenario-Based Identification:
"A patient presents with left-sided weakness and slurred speech. Identify the most likely anatomical structure affected."
Pitfall: Overlooking the right middle cerebral artery (MCA) territory involvement in stroke (contralateral deficits due to decussation in the brainstem).
Strategy: Use the mnemonic "FAST" (Face, Arm, Speech, Time) to correlate clinical signs with vascular territories.
-
Labeling Diagrams Without Context:
"Label the following structures in the provided cross-section of the thigh."
Pitfall: Misidentifying the femoral nerve (lateral compartment) vs. sciatic nerve (posterior compartment) due to superficial similarities.
Strategy: Memorize anatomical landmarks (e.g., femoral nerve lies within the iliopsoas muscle).
-
Ambiguous Terminology:
"Describe the innervation of the diaphragm."
Pitfall: Forgetting the phrenic nerve (C3–C5) while recalling only the intercostal nerves (which assist with forced respiration).
Strategy: Use the phrase "C3, 4, 5 keeps the diaphragm alive" for motor innervation.
-
Clinical Correlation Without Specificity:
*"Explain why a patient with a fractured clavicle may
Interdisciplinary Connections: Anatomy in Nursing Curricula
Anatomy serves as the foundational framework for nursing practice, bridging biological sciences with clinical applications across multiple disciplines. Its integration into nursing curricula ensures that students develop a holistic understanding of human physiology, enabling them to apply anatomical knowledge in pharmacology, pathology, patient assessment, and ethical decision-making. This section explores how anatomy intersects with other nursing subjects through structured case studies, interdisciplinary mappings, and clinical workflows, while addressing cultural and anatomical diversity in patient care.
Mapping Anatomy Across Nursing Disciplines: A Case Study Framework
Anatomy’s relevance extends beyond standalone study; it is a critical lens through which pharmacology, pathology, and patient education are examined. Below is a structured table illustrating how anatomical systems (e.g., renal, cardiovascular) correlate with key nursing topics, including drug mechanisms, disease processes, and patient-centered interventions.Anatomy’s role in interdisciplinary learning is reinforced through case-based integration, where students analyze how anatomical structures influence therapeutic outcomes and patient responses. For example:
- Anatomy of the kidney → Diuretic mechanisms (e.g., loop vs. thiazide diuretics targeting the nephron’s ascending limb) → Patient teaching for chronic kidney disease (fluid restrictions, medication adherence).
- Cardiac conduction system → Antiarrhythmic drug classes (e.g., sodium channel blockers for ventricular tachycardia) → Post-procedure monitoring for ablation therapy.
- Gastrointestinal motility → Prokinetic agents (e.g., metoclopramide) → Nutritional counseling for gastroparesis.
| Anatomical System |
Pharmacology Connection |
Pathophysiology Link |
Clinical/Nursing Application |
|---|
| Respiratory (alveoli, bronchi) |
Bronchodilators (β2-agonists, anticholinergics) |
COPD exacerbations, asthma pathophysiology |
Inhaler technique education, oxygen therapy protocols |
| Endocrine (pancreas, adrenal glands) |
Insulin analogs, glucocorticoids |
Type 2 diabetes, Cushing’s syndrome |
Blood glucose monitoring, steroid tapering plans |
| Neuromuscular (motor units, neurotransmitters) |
Neuromuscular blockers (e.g., succinylcholine) |
Myasthenia gravis, spinal cord injuries |
Post-op ventilation management, mobility assessments |
| Hematologic (bone marrow, coagulation cascade) |
Anticoagulants (warfarin, DOACs) |
Deep vein thrombosis, hemophilia |
INR monitoring, fall prevention strategies |
Progression of Anatomical Knowledge: From Basic Science to Clinical Practice
The evolution of anatomical understanding in nursing follows a spiral curriculum, where foundational concepts are revisited and applied in increasingly complex clinical scenarios. Below is a flowchart outlining the progression, with milestones that emphasize active learning and clinical relevance.Flowchart Structure:
1. Basic Science Phase (Theory)
- Lab dissections (e.g., cadaveric or synthetic models of the heart, brain).
- Histology studies (microscopic examination of tissue samples).
- Anatomical terminology (e.g., directional terms, planes of section).
- Outcome: Ability to identify structures and describe their functions.
2. Simulated Learning Phase (Application)
- Simulated patient assessments (e.g., auscultating heart murmurs, palpating pulses).
- Virtual reality (VR) anatomy modules (e.g., navigating laparoscopic procedures).
- Pathophysiology case simulations (e.g., "What anatomical changes occur in heart failure?").
- Outcome: Integration of anatomy with assessment skills and diagnostic reasoning.
3. Clinical Rotations Phase (Integration)
- Procedure-based rotations (e.g., central line insertion, lumbar punctures).
- Patient teaching tied to anatomy (e.g., "Why does this medication affect your blood pressure?").
- Interprofessional rounds (collaborating with physicians on anatomical diagnoses).
- Outcome: Clinical decision-making rooted in anatomical principles.
4. Advanced Practice Phase (Specialization)
- Specialized anatomy reviews (e.g., pelvic anatomy for obstetrics, cranial nerves for neurology).
- Research applications (e.g., studying anatomical variations in surgical outcomes).
- Ethical/legal considerations (e.g., anatomical risks in informed consent).
- Outcome: Expert-level synthesis of anatomy across nursing specialties.
Visual Representation (Descriptive):
- The flowchart would depict a circular or upward-spiraling path, with arrows connecting each phase. For example:
- Lab dissection → Simulated auscultation → Clinical assessment of a patient with mitral valve disease → Teaching a patient about valve replacement risks.
- Histology of synovial joints → VR arthroscopy simulation → Pre-op teaching for knee replacement → Post-op mobility planning.
Cultural and Anatomical Diversity in Nursing Care
Anatomical and physiological variations—shaped by genetics, ethnicity, and environmental factors—directly impact drug responses, disease presentation, and patient outcomes. Nursing curricula must incorporate these diversities to ensure culturally competent care. Below are key considerations, supported by evidence-based examples.Genetic Variations in Drug Metabolism:
- Cytochrome P450 enzymes (e.g., CYP2D6, CYP2C19) exhibit polymorphic activity across populations, affecting drug efficacy and toxicity.
- Example: Sickle cell trait (HbAS) alters oxygen affinity, influencing pain management in vaso-occlusive crises. Patients may require higher opioid doses due to altered receptor sensitivity.
- Example: Lactose intolerance (lactase deficiency) is more prevalent in East Asian and African populations, necessitating alternative calcium sources in dietary teaching.
Anatomical Adaptations and Disease Risk:
- Body mass index (BMI) and fat distribution: Higher visceral fat in some ethnic groups (e.g., South Asians) increases cardiovascular risk, requiring tailored lipid-lowering therapy.
- Bone density variations: African Americans have higher peak bone mass but may still face secondary osteoporosis due to dietary deficiencies, necessitating calcium/vitamin D supplementation.
Cultural Perceptions of Anatomy and Health:
- Beliefs about pain: Some cultures may underreport pain due to stigma (e.g., stoicism in certain Asian communities), requiring anatomical explanations (e.g., "This is how your nerves signal pain") to encourage disclosure.
- Body modifications: Practices like cupping or coining may leave anatomical marks (e.g., petechiae), which nurses must differentiate from abuse or pathological bruising.
"Anatomical diversity is not merely a biological variation but a clinical imperative. For instance, the warfarin dosing algorithm must account for differences in vitamin K metabolism among ethnic groups, as seen in studies where African Americans require lower initial doses due to higher sensitivity."
— Source: Adapted from FDA Pharmacogenomic Biomarkers in Drug Labeling (2021).
Curricular Integration:
- Genetic testing scenarios in pharmacology labs (e.g., "How would you adjust morphine dosing for a patient with a CYP2D6 poor metabolizer genotype?").
- Cultural competency modules pairing anatomy with health disparities data (e.g., "Why do Hispanic patients have higher diabetes complications? Link to genetic predisposition and access to care").
Anatomy and Ethical/Legal Considerations in Nursing Practice
Anatomical knowledge intersects with ethical principles and legal standards, particularly in informed consent, procedural risks, and patient autonomy. Nurses must correlate anatomical structures with potential complications to ensure transparent communication and compliance with regulations.Framework for Ethical-Anatomical Correlation:
1. Informed Consent for Procedures
- Anatomical Risk: Procedures like lumbar punctures carry
Mastering Anatomi Eksamen Sykepleie is not merely about passing an exam—it is about equipping nurses with the anatomical expertise to deliver safer, more effective care. By synthesizing core concepts with clinical applications, this guide ensures learners recognize the relevance of anatomy in every facet of nursing, from emergency interventions to patient education. The integration of interdisciplinary connections further underscores how anatomical knowledge intersects with pharmacology, pathology, and ethical considerations, reinforcing its foundational role in nursing curricula. As candidates refine their study techniques and confront common pitfalls, they emerge not only exam-ready but also better prepared to apply anatomical principles in diverse patient scenarios, ultimately elevating the standard of nursing practice.
|
|


Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.