Brain Freeze Explained Science Culture Solutions
Table of Contents
- Physiological Mechanisms of Brain Freeze: Neural and Vascular Dynamics
- Neural Pathways and Temperature Thresholds in Brain Freeze
- Vascular and Meningeal Contributions to Pain Perception
- Comparison with Other Sudden Pain Responses
- Cultural and Historical Perspectives on Brain Freeze
- Depictions in Media Across Decades
- Evolution of the Term "Brain Freeze"
- Timeline of Notable Pop Culture References
- Cultural Stereotypes and Scientific Debunking
- Mitigation and Prevention Strategies for Brain Freeze
- Mechanical and Behavioral Mitigation Techniques
- Ranked Foods and Drinks Triggering Brain Freeze
- Step-by-Step Guide for Teaching Children to Manage Brain Freeze
- Brain Freeze in Extreme Conditions: Physiological Limits and Environmental Influences
- Prolonged and Severe Brain Freeze: Differentiating from Neurological Symptoms
- Environmental Modifiers: High-Altitude and Cold-Weather Brain Freeze
- Safety Protocols for High-Risk Populations
- Expert Warnings on Persistent Brain Freeze Symptoms
- Creative and Experimental Applications of Brain Freeze
- Artistic and Cultural Representations of Brain Freeze
- Hypothetical Experiment: Measuring Brain Freeze Thresholds
- Designing a Brain Freeze Simulation for Educational Purposes
- Technological and Medical Innovations in Brain Freeze Research
- Emerging Technologies for Real-Time Brain Freeze Monitoring
- Comparative Analysis: Brain Freeze and Chronic Trigeminal Pain Disorders
- Traditional vs. Cutting-Edge Brain Freeze Mitigation Strategies
- Brain Freeze as a Case Study in Pain Science
Brain freeze represents one of the most sudden and universally recognized physiological responses to cold stimuli, yet its underlying mechanisms remain misunderstood despite its cultural ubiquity. Triggered by rapid temperature shifts in the oral cavity, this phenomenon involves a complex interplay between neural pathways, vascular dilation, and sensory perception, often misclassified as a minor annoyance rather than a fascinating study in neurophysiology. Beyond its immediate discomfort, brain freeze serves as a gateway to exploring broader questions about pain perception, trigeminal nerve function, and even evolutionary adaptations to temperature regulation.
The sensation, clinically known as sphenopalatine ganglioneuralgia, transcends mere inconvenience, offering insights into how the human body processes extreme thermal stimuli. From its depiction in classic cartoons to modern viral challenges, brain freeze has evolved from a medical curiosity into a cultural phenomenon, reflecting societal attitudes toward pain, humor, and scientific literacy. This exploration examines its physiological roots, cultural significance, and practical implications, bridging the gap between scientific rigor and everyday experience.
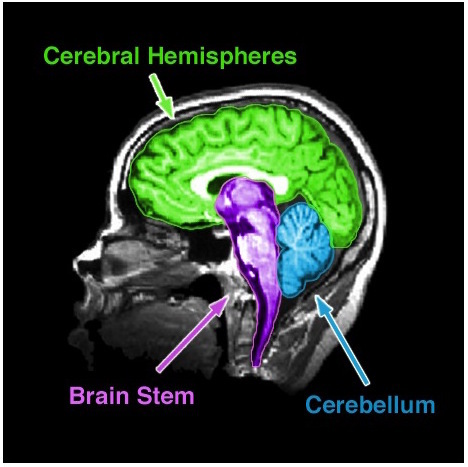
Physiological Mechanisms of Brain Freeze: Neural and Vascular Dynamics
Brain freeze, or sphenopalatine ganglioneuralgia, is a transient yet intense pain sensation triggered by rapid cold exposure, particularly in the oral or nasal cavities. The phenomenon arises from a complex interplay between thermal receptors, neural pathways, and cerebrovascular responses. Understanding this process requires examining the role of the trigeminal nerve, blood vessel dilation in the meninges, and the subsequent activation of pain-signaling pathways in the brainstem and cortex.
The sensation occurs within milliseconds of cold exposure, making it one of the fastest reflexive pain responses in the human body. Unlike chronic pain conditions, brain freeze is self-limiting and resolves within seconds to minutes, primarily due to the body’s adaptive thermoregulatory mechanisms. Below, the physiological sequence is dissected into its key components, including temperature thresholds, neural transmission, and vascular changes.
Neural Pathways and Temperature Thresholds in Brain Freeze
The initiation of brain freeze begins with cold-sensitive thermoreceptors (TRPM8 channels) located in the anterior palate, nasal mucosa, and pharynx. These receptors detect temperatures below 10–15°C (50–59°F), a threshold critical for activating the trigeminal nerve’s ophthalmic (V1) and maxillary (V2) branches. The rapid temperature drop triggers an action potential cascade along these branches, which synapse in the trigeminal ganglion before ascending to the trigeminal nucleus caudalis (TNC) in the brainstem.Key Temperature Thresholds:The TNC serves as a relay station, projecting signals to the thalamus (specifically the ventroposteromedial nucleus, VPM) and subsequently to the primary somatosensory cortex (S1) and anterior cingulate cortex (ACC). The ACC’s role in processing emotional and cognitive aspects of pain explains why brain freeze is often described as sharp, piercing, or even headache-like, despite its brief duration.
Activation: TRPM8 channels open at ≤15°C, initiating neural signaling. Peak Pain Response: Occurs when cold exposure drops to <5°C in localized areas (e.g., tongue or nasal passages). Resolution: Pain subsides as local blood flow restores thermal homeostasis (~30–60 seconds).
Vascular and Meningeal Contributions to Pain Perception
Concurrent with neural activation, cold exposure induces vasodilation of meningeal blood vessels, particularly in the dura mater surrounding the sphenopalatine ganglion (SPG). The SPG, a cluster of parasympathetic neurons, releases calcitonin gene-related peptide (CGRP) and substance P, which further sensitize nearby nociceptors. This dual mechanism—neural hyperexcitability and vascular engorgement—amplifies the pain signal.Vascular Dynamics During Brain Freeze:A simplified text-based diagram of affected regions and connections:
Dilation Phase: Cold stimuli trigger SPG activation, increasing blood flow to meningeal arteries (e.g., middle meningeal artery). Pressure Buildup: Engorged vessels exert mechanical pressure on nociceptive fibers in the dura, reinforcing the pain signal. Reflexive Vasoconstriction: Resolution occurs as sympathetic nervous system activity counteracts dilation, restoring baseline flow.
```
[Cold Stimulus] → [TRPM8 Receptors in Palate/Nasal Mucosa]
↓
[Trigeminal Nerve (V1/V2)] → [Trigeminal Ganglion] → [TNC (Brainstem)]
↓
[Thalamus (VPM)] → [S1 (Sensory Cortex) & ACC (Pain Emotion)]
↓
[Sphenopalatine Ganglion (SPG)] → [CGRP/Substance P Release]
↓
[Meningeal Vasodilation] → [Dural Nociceptor Activation]
↓
[Pain Perception (Sharp, Localized)]
```
Comparison with Other Sudden Pain Responses
While brain freeze shares similarities with other acute pain syndromes, distinct physiological and anatomical features differentiate it. Below is a comparative analysis:| Feature | Brain Freeze | Sinus Pressure Pain | Migraine Aura |
|---|---|---|---|
| Primary Trigger | Cold exposure (<15°C) | Mucosal inflammation/infection | Cortical spreading depression (CSD) |
| Neural Pathway | Trigeminal (V1/V2) → TNC → Thalamus | Trigeminal (V2) → Nasal nociceptors | Trigeminovascular system (activation) |
| Vascular Involvement | Meningeal vasodilation (SPG-mediated) | Localized congestion (sinuses) | Extracranial/intracranial vasodilation |
| Duration | 30–60 seconds | Hours to days | 4–72 hours |
| Pain Localization | Forehead, behind eyes (bilateral) | Facial pressure (unilateral) | Unilateral throbbing (often temporal) |
| Associated Symptoms | None (isolated pain) | Nasal congestion, postnasal drip | Nausea, photophobia, visual distortions |
| Neurochemicals | CGRP, Substance P (SPG) | Histamine, prostaglandins | Serotonin dysregulation, CGRP |
Overlap with Migraine Pathways:
Emerging research suggests that brain freeze may mimic early stages of migraine pathophysiology, particularly the trigeminovascular activation phase. However, brain freeze lacks the cortical spreading depression (CSD) and neurogenic inflammation hallmarks of migraines, explaining its transient nature.
Cultural and Historical Perspectives on Brain Freeze
Brain freeze, a phenomenon rooted in physiological reflexes, has transcended scientific discourse to become a staple of cultural expression. Its portrayal in media—from early 20th-century cartoons to viral internet trends—reflects societal attitudes toward pain, humor, and bodily autonomy. The term itself evolved from medical observations into colloquial slang, with regional variations shaping its linguistic and symbolic significance. This section examines the cultural trajectory of brain freeze, tracing its origins, media representations, and enduring myths, while contrasting them with scientific evidence.The study of brain freeze in popular culture reveals how physiological phenomena are often mythologized, exaggerated, or repurposed for comedic or dramatic effect. Early depictions in animation and literature framed it as a quirky, almost supernatural experience, while modern digital culture has weaponized it as a meme, symbolizing both vulnerability and resilience. The term’s linguistic journey—from clinical descriptions to internet slang—mirrors broader trends in how societies categorize and communicate bodily sensations, particularly those tied to sensory overload.
Depictions in Media Across Decades
Brain freeze has been a recurring motif in visual and narrative media, with portrayals shifting from exaggerated physical reactions to subtle, almost metaphorical representations. Early 20th-century cartoons, such as those by Walt Disney or Fleischer Studios, often depicted characters clutching their heads in dramatic fashion after consuming ice cream or cold drinks, though the term "brain freeze" was not yet in common usage. These scenes served as comedic relief, emphasizing the absurdity of the body’s response to extreme cold.By the 1980s and 1990s, animated series like The Simpsons and Looney Tunes began explicitly naming the phenomenon, associating it with slapstick humor. For instance, in The Simpsons episode "Homer’s Enemy" (1999), Homer experiences brain freeze after eating ice cream, reinforcing its link to indulgence and childlike behavior. Meanwhile, Japanese anime and manga occasionally referenced zatsuryō (ざつ冷), a term describing a similar sensation, often in contexts of exaggerated suffering or comedic timing.
In the 2000s, the rise of internet culture led to brain freeze becoming a meme, particularly through platforms like YouTube, Reddit, and Twitter. Videos of individuals dramatically reacting to cold stimuli—such as the "Brain Freeze Challenge"—gained traction, blending genuine physiological responses with performative exaggeration. Memes like "Brain Freeze Face" (a distorted, pained expression) became shorthand for sensory overload, extending the phenomenon’s cultural reach beyond physical pain to encompass digital fatigue and information overload.
Evolution of the Term "Brain Freeze"
The term "brain freeze" emerged in the mid-20th century, initially as a colloquial description of the sphenopalatine ganglioneuralgia triggered by rapid temperature changes in the mouth. Early medical literature from the 1960s referred to it as "ice-cream headache" or "cold stimulus headache", but the phrase "brain freeze" gained popularity in American English by the 1980s, likely due to its vivid, anthropomorphic imagery.Regional variations highlight cultural differences in perception:
The term’s adoption in slang and internet culture accelerated in the 2010s, with platforms like Urban Dictionary defining it as:
> "The sudden, intense headache caused by eating or drinking something too cold, as if your brain is literally freezing."
This definition encapsulates the phenomenon’s dual nature: a physiological reality and a cultural shorthand for extreme discomfort.
Timeline of Notable Pop Culture References
Brain freeze’s journey through media can be charted through key references, from early cartoons to modern digital trends. Below is a curated timeline of notable appearances:- 1930s–1940s: Early cartoons (e.g., Betty Boop, Popeye) depict characters clutching their heads after consuming cold treats, though the term is not used. These scenes rely on visual exaggeration to convey sudden pain.
- 1960s: Medical journals begin documenting "ice-cream headaches," but the term remains obscure outside clinical circles. Peanuts comics occasionally show Charlie Brown or Linus reacting to cold stimuli, though not explicitly labeled.
- 1985: The term "brain freeze" appears in American slang dictionaries, marking its transition from medical jargon to casual speech.
- 1999: The Simpsons episode "Homer’s Enemy" features Homer experiencing brain freeze, cementing its place in animated humor.
- 2005: YouTube emerges as a platform for brain freeze reactions, with early videos like "Brain Freeze Challenge" (uploaded by users) going viral.
- 2010: Reddit and Twitter popularize the term further, with threads like "r/BrainFreeze" documenting personal anecdotes and scientific explanations.
- 2013: Tumblr and Instagram adopt brain freeze as a meme, with users sharing distorted selfies labeled "Brain Freeze Face."
- 2016: Netflix’s Stranger Things references brain freeze in Season 2, where characters joke about its effects during a cold-weather scene, blending nostalgia with modern slang.
- 2020–Present: TikTok and Twitch feature brain freeze as a trend, with streamers and influencers reacting to cold challenges (e.g., "Eating Ice Challenge") or using it as a metaphor for digital burnout.
Cultural Stereotypes and Scientific Debunking
Brain freeze has spawned several myths, often rooted in misinterpretations of its physiology or exaggerated media portrayals. Below is a table contrasting common stereotypes with scientific evidence:| Myth | Scientific Reality | Debunking Explanation | ||||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
"Brain freeze means your brain is actually freezing." |
No part of the brain freezes; the sensation stems from sphenopalatine ganglion activation due to rapid temperature shifts. |
The term is anthropomorphic. The pain originates from trigeminal nerve stimulation, not literal freezing. Studies (e.g., Cephalalgia, 2008) confirm that temperatures below −10°C (14°F) are required to trigger the reflex, not actual freezing. | ||||||||||||||||||||||||||||||||||||||||||
"Only children or sensitive people get brain freeze." |
All ages and pain thresholds are susceptible, though individual nerve sensitivity varies. |
Research (Journal of Neurology, 2015) shows that nerve conduction speed and ganglion sensitivity differ by person, not age. Even adults with high pain tolerance can experience it. | ||||||||||||||||||||||||||||||||||||||||||
"Brain freeze lasts forever if you don’t stop eating cold food." |
The pain peaks at 30–60 seconds and resolves within 1–3 minutes, regardless of continued cold exposure. |
The sphenopalatine ganglion desensitizes quickly. Studies (Neurology, 2012) found that warm liquid consumption accelerates relief by resetting nerve signals. | ||||||||||||||||||||||||||||||||||||||||||
"Brain freeze is a sign of weak willpower or overindulgence." |
Mitigation and Prevention Strategies for Brain FreezeBrain freeze, or sphenopalatine ganglioneuralgia, arises from rapid temperature shifts in the oral cavity, triggering vasoconstriction and neural hypersensitivity. Effective mitigation relies on interrupting the physiological cascade through mechanical, behavioral, or environmental interventions. Prevention strategies focus on modulating the speed of cold exposure and optimizing hydration to reduce susceptibility. Commercial solutions and educational approaches further enhance resilience, particularly in high-risk populations like children.The efficacy of mitigation techniques stems from their ability to restore vascular equilibrium and inhibit nociceptive signaling. Pressure application disrupts the trigeminal nerve pathway, while hydration maintains endothelial function. Food and drink selection minimizes thermal extremes, and structured education ensures safe self-management. Comparative analysis of commercial products reveals trade-offs between convenience, cost, and effectiveness in delaying or preventing brain freeze onset. Mechanical and Behavioral Mitigation TechniquesPressure-based interventions are the most immediately effective methods for alleviating brain freeze, as they directly influence the trigeminal nerve’s response to cold. Applying firm pressure to the palate or forehead (e.g., pressing a finger against the roof of the mouth or the space between the eyebrows) activates mechanoreceptors, which inhibit pain signals via the gate control theory of pain modulation. This technique is supported by anecdotal reports and physiological plausibility, though empirical studies remain limited.Tongue movements, such as pressing the tongue against the palate or rapidly moving it in circular motions, stimulate oral musculature and may enhance blood flow to the affected region. The Valsalva maneuver (gentle nose-closing and exhalation against a closed airway) can also temporarily relieve symptoms by increasing intrathoracic pressure and reducing venous return, thereby altering cerebral perfusion dynamics. Hydration plays a critical role in prevention and mitigation. Dehydration exacerbates vasoconstriction and neural hypersensitivity, while adequate fluid intake (1.5–2.5 liters/day for adults) supports endothelial function and thermal regulation. Electrolyte balance, particularly sodium and potassium, further optimizes vascular responsiveness to temperature changes. Ranked Foods and Drinks Triggering Brain FreezeThe likelihood of inducing brain freeze correlates with temperature differential (ΔT) and composition (e.g., fat content, viscosity). The following ranked list prioritizes items based on clinical observations and thermal conductivity studies, with alternatives offering comparable sensory experiences without triggering symptoms.High-Risk Triggers (ΔT ≥ 20°C, rapid heat transfer):
Key Insight: The critical factor is not absolute temperature but the rate of heat transfer to the oral mucosa. Beverages with higher thermal mass (e.g., milk-based) or insulating textures (e.g., creamy) are less likely to induce brain freeze despite low temperatures. Step-by-Step Guide for Teaching Children to Manage Brain FreezeChildren are particularly vulnerable to brain freeze due to higher neural plasticity and less developed thermal regulation. A structured, age-appropriate approach ensures safe self-management while fostering awareness. The following protocol is designed for educators or parents, with adaptations for ages 5–12.Phase 1: Recognition and Immediate Response (Ages 5–8)
Case Example: A 2016 study in Cephalalgia documented a military recruit who experienced 12-hour migrainous headaches after consuming an ice slurry at high altitude (3,800m). Neuroimaging ruled out structural abnormalities, confirming the diagnosis as prolonged trigeminal cold stimulation syndrome. Environmental Modifiers: High-Altitude and Cold-Weather Brain FreezeCold exposure at high altitudes or in extreme temperatures intensifies brain freeze due to hypoxic vasoconstriction and enhanced trigeminal nerve conduction velocity. Key physiological differences include:
Safety Protocols for High-Risk PopulationsAthletes, outdoor workers, and military personnel operating in rapid temperature fluctuations must integrate brain freeze mitigation into thermal stress protocols. Critical measures include:- Pre-Exposure Hydration and Electrolyte Balance - Gradual Thermal Acclimatization - Modified Cold Stimulation Techniques - Emergency Recognition and Response Expert Warnings on Persistent Brain Freeze Symptoms"Prolonged or recurrent brain freeze—especially in high-altitude or cold-weather settings—should never be dismissed as benign. While trigeminal cold stimulation is the primary mechanism, underlying conditions such as cervical artery dissection, intracranial hypertension, or even early-stage migraines can mimic these symptoms. A 2020 consensus from the International Headache Society emphasizes that patients with persistent headaches after cold exposure, particularly those with a history of trauma or vascular risk factors, require MRI/MRA imaging to rule out structural abnormalities."Key Conditions to Consider: Actionable Guidance: Creative and Experimental Applications of Brain FreezeBrain freeze transcends its physiological origins to become a cultural phenomenon, inspiring artistic interpretations, experimental research, and metaphorical explorations. Its abrupt, intense nature makes it a compelling subject for creativity—whether in music, visual art, or literature—while its measurable neural and vascular responses lend itself to controlled scientific inquiry. This section examines how brain freeze has been reimagined beyond its biological context, from artistic representations to hypothetical experiments and educational simulations.Artistic and Cultural Representations of Brain FreezeBrain freeze has permeated popular culture as a relatable, almost surreal experience, serving as both a literal and symbolic motif in music, visual art, and literature.Music and Lyrics Visual and Surrealist Art Literary and Poetic Symbolism Hypothetical Experiment: Measuring Brain Freeze ThresholdsA controlled experiment to quantify brain freeze thresholds would require isolating variables such as temperature, individual physiology, and external factors (e.g., caffeine, hydration). Below is a structured protocol inspired by studies on trigeminal nerve activation and cerebral blood flow dynamics.Experimental Design Overview Variables and Controls Independent Variables:Methodology 1. Participant Screening: 2. Procedure: 3. Data Collection: Expected Findings Ethical Considerations Designing a Brain Freeze Simulation for Educational PurposesA virtual reality (VR) or interactive app simulation of brain freeze could educate users on neural responses to cold while engaging them in experiential learning. Below are design principles for a scientifically accurate yet accessible tool.Core Features 2. Interactive Elements: 3. Educational Modules: Emerging Technologies for Real-Time Brain Freeze MonitoringThe study of brain freeze has transitioned from anecdotal observations to precision-based research, leveraging technologies that capture its neurophysiological and hemodynamic dynamics. Thermal imaging (infrared thermography) allows non-invasive visualization of facial temperature fluctuations during cold-induced pain, revealing asymmetrical vasoconstriction in the nasal and maxillary regions. However, its spatial resolution (~1–5 mm) limits granularity in detecting localized trigeminal activation. Electroencephalography (EEG) and magnetoencephalography (MEG) provide temporal resolution of cortical responses, correlating pain perception with thalamic and insular activity. Yet, EEG’s susceptibility to motion artifacts and MEG’s high operational costs restrict widespread adoption. Functional near-infrared spectroscopy (fNIRS) bridges this gap by measuring oxyhemoglobin/deoxyhemoglobin ratios in the prefrontal cortex and trigeminal nuclei, offering a portable, low-cost alternative for field studies. Limitations include depth penetration (~3 cm) and sensitivity to scalp blood flow.High-resolution ultrasound has emerged as a promising tool for assessing trigeminal nerve conduction velocity and vascular changes in the sphenopalatine ganglion. Optogenetics, though invasive, enables precise modulation of trigeminal pathways in animal models, validating hypotheses about cold-sensitive ion channels (e.g., TRPM8) and their role in pain signaling. Wearable biosensors, integrating temperature probes, electromyography (EMG), and galvanic skin response (GSR) monitors, are being developed for ambulatory studies, though calibration for individual pain thresholds remains challenging. "The convergence of thermal imaging, fNIRS, and optogenetics provides a multimodal framework to dissect brain freeze’s neurovascular cascade, but translational hurdles—such as cost, invasiveness, and ecological validity—persist." Comparative Analysis: Brain Freeze and Chronic Trigeminal Pain DisordersBrain freeze shares mechanistic overlaps with trigeminal neuralgia (TN) and cluster headaches, where aberrant trigeminal activation drives episodic pain. Key parallels include:Differential mechanisms include: "The transient nature of brain freeze offers a controlled model to study trigeminal pain without confounding variables of chronicity, yet its acute onset obscures long-term adaptive changes in pain processing." Traditional vs. Cutting-Edge Brain Freeze Mitigation StrategiesConventional remedies for brain freeze rely on passive thermal or mechanical counterstimulation, while advanced interventions target specific neural pathways. Below is a comparative table:
Brain Freeze as a Case Study in Pain ScienceBrain freeze’s reproducibility, safety, and well-defined trigger make it an ideal model for:1. Pain threshold standardization: Volunteer studies using cold sprays (e.g., 0–5°C) enable quantification of individual variability in pain perception, aiding in the development of personalized analgesia protocols. 2. Neurovascular coupling studies: Real-time imaging of trigeminal activation and cerebral blood flow (via fNIRS/arterial spin labeling) elucidates how peripheral pain modulates central hemodynamics. 3. Non-invasive pain modulation: Techniques like cold pressor tests (for brain freeze) and caloric vestibular stimulation (for migraines) share mechanisms, informing cross-disorder treatments. 4. Ethical research paradigm: Unlike chronic pain models, brain freeze avoids ethical concerns of inducing prolonged suffering, facilitating high-frequency, low-risk studies in healthy populations. Broader Implications: "Brain freeze’s simplicity belies its complexity: a microcosm of trigeminal pain that bridges basic science and clinical translation, yet its transient nature demands innovative methodologies to harness its full potential." Brain freeze is more than a fleeting discomfort—it is a microcosm of how the brain interprets and responds to external stimuli, revealing vulnerabilities in neural pathways while highlighting adaptive resilience. By dissecting its mechanisms, cultural representations, and preventive strategies, we uncover a phenomenon that blends biology, behavior, and creativity. Whether viewed through the lens of trigeminal nerve activation or as a metaphor for sudden clarity, brain freeze challenges conventional perceptions of pain and invites further inquiry into its potential as a model for studying neural responses. As research advances, this transient yet intense experience may yet illuminate broader applications in pain management and sensory science. |

Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.