HIV Ruam Kulit Manifestations and Management Strategies
Table of Contents
- Medical Overview of Ruam Kulit (Skin Rashes) in HIV Patients: Pathophysiology and Clinical Manifestations
- Classification of HIV-Related Dermatoses and Their Clinical Features
- Diagnostic Criteria for Distinguishing HIV-Related Rashes from Non-HIV Dermatoses
- Pathophysiology and Immune System Links in HIV-Associated Skin Rashes (Ruam Kulit)
- Immune Dysfunction in HIV and Its Role in Skin Lesion Pathogenesis
- Viral Load and ART Status as Modulators of Skin Manifestations
- Coinfections and Their Dermatologic Impact
- Flowchart: Progression from HIV Infection to Skin Manifestations
- Diagnostic Approaches and Differential Diagnosis in HIV-Associated Skin Rashes (Ruam Kulit)
- Step-by-Step Diagnostic Process for Evaluating Ruam Kulit in HIV Patients
- Decision-Tree for Differentiating HIV-Related Rashes from Non-HIV Causes
- Treatment Protocols and Management Strategies for HIV-Associated Skin Rashes (Ruam Kulit)
- Pharmacological Interventions for HIV-Associated Skin Rashes
- Comparison of Conventional vs. Alternative Therapies for HIV-Associated Dermatoses
- Patient-Centered Care Plan for HIV-Associated Skin Rashes
- Patient Education and Quality of Life Impact in HIV-Associated Skin Rashes (Ruam Kulit)
- Infographic-Style Description: Daily Life Disruptions from Ruam Kulit
- Visual Element 1: Physical Symptoms and Pain
- Visual Element 2: Emotional and Social Consequences
- Visual Element 3: Treatment Adherence Barriers
- Key Counseling Points for Healthcare Providers
- Symptom-Tracking Template for Patients
HIV-associated skin manifestations known as ruam kulit represent a critical intersection of dermatology and immunology, often serving as early indicators of immune dysfunction or progression in infected individuals. These conditions range from common inflammatory dermatoses to opportunistic infections, each reflecting distinct pathophysiological pathways tied to viral load, CD4 depletion, and antiretroviral therapy response. Beyond clinical significance, ruam kulit profoundly impacts patient quality of life, influencing adherence to treatment regimens and psychosocial well-being. This exploration synthesizes medical evidence, diagnostic frameworks, and evidence-based interventions to equip healthcare providers with actionable insights for comprehensive patient care.
The spectrum of HIV-related dermatoses encompasses diverse presentations, from localized erythematous plaques to systemic eruptions, each demanding precise differentiation from non-HIV etiologies. Advances in antiretroviral therapy have transformed dermatological landscapes, yet residual challenges persist, particularly in resource-limited settings where opportunistic infections remain prevalent. By dissecting the interplay between immune dysfunction and cutaneous symptoms, this analysis bridges clinical observation with therapeutic decision-making, emphasizing proactive management to mitigate morbidity and improve long-term outcomes.
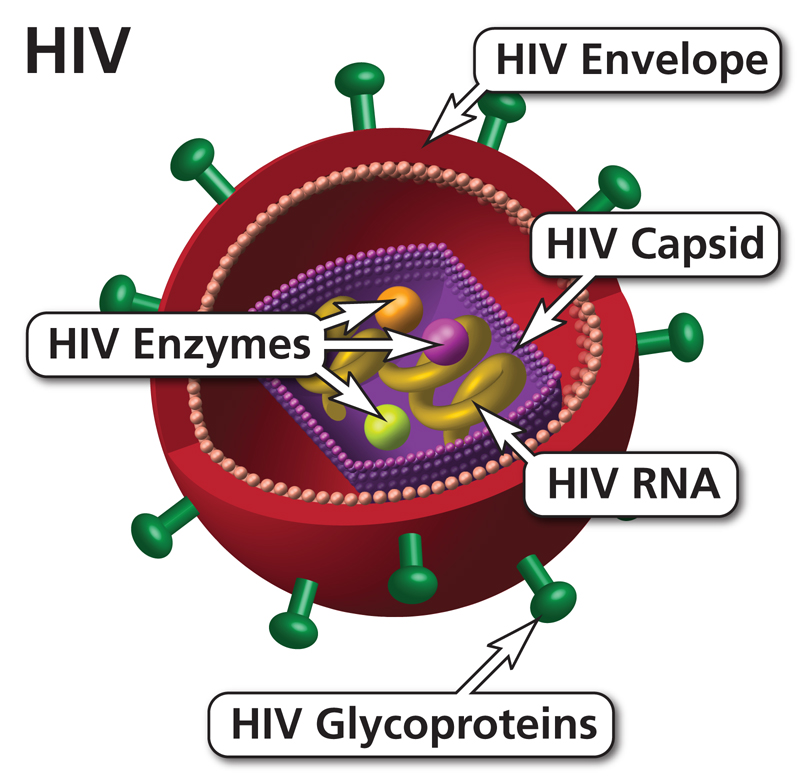
Medical Overview of Ruam Kulit (Skin Rashes) in HIV Patients: Pathophysiology and Clinical Manifestations
HIV-associated dermatological manifestations, commonly referred to as ruam kulit (skin rashes), represent a spectrum of inflammatory, infectious, neoplastic, and reactive conditions influenced by immune dysfunction. These rashes often serve as early indicators of HIV infection, progression to AIDS, or adverse reactions to antiretroviral therapy (ART). The pathogenesis involves immune dysregulation, opportunistic infections, malignancies, and drug hypersensitivity, with manifestations varying by HIV stage. Primary symptoms include pruritic or non-pruritic maculopapular eruptions, while secondary complications may involve systemic involvement or resistance to standard therapies.The clinical presentation of HIV-related dermatoses differs significantly from non-HIV dermatological conditions due to T-cell depletion, particularly CD4+ lymphocyte counts below 200 cells/µL, which predisposes individuals to atypical or severe forms of dermatoses. Below is a structured breakdown of key dermatological entities, their triggers, visual characteristics, and correlation with HIV progression.
Classification of HIV-Related Dermatoses and Their Clinical Features
HIV-associated skin diseases are categorized into primary infections, secondary opportunistic infections, inflammatory dermatoses, and neoplastic conditions. Each category exhibits distinct morphological features that aid in differential diagnosis. The following table summarizes the most common dermatoses, their triggers, visual hallmarks, and associated HIV stages.| Dermatosis Type | Common Triggers | Visual Features | Associated HIV Stage |
|---|---|---|---|
| Seborrheic Dermatitis |
|
|
Early HIV (CD4 200–500 cells/µL), chronic in untreated patients |
| Psoriasis |
|
|
All stages; exacerbations correlate with low CD4 (<200 cells/µL) or IRIS |
| Kaposi’s Sarcoma (KS) |
|
|
Late-stage HIV (CD4 < 200 cells/µL); aggressive in untreated patients |
| Fungal Infections (e.g., Tinea, Candidiasis) |
|
|
Early to late-stage; candidiasis often CD4 < 400 cells/µL |
| Drug Reactions (e.g., ART-Associated) |
|
|
Early ART initiation (within 6 weeks); SJS/DRESS may occur at any stage |
| Bacterial Infections (e.g., Staphylococcus, Streptococcus) |
|
|
All stages; severity increases with immunosuppression |
Diagnostic Criteria for Distinguishing HIV-Related Rashes from Non-HIV Dermatoses
Accurate diagnosis of HIV-associated dermatoses requires a multifactorial approach, integrating clinical presentation, laboratory findings, and HIV staging. The following criteria help differentiate HIV-related rashes from non-HIV conditions, emphasizing atypical features, systemic associations, and response to therapy.HIV-related dermatoses often exhibit the following distinguishing characteristics:
-
Atypical Distribution or Morphology:
- Extensive or generalized eruptions (e.g., seborrheic dermatitis beyond typical seborrheic areas)
- Unilateral or asymmetric lesions (e.g., Kaposi’s sarcoma)
- Confluent or exfoliative dermatoses (e.g., psoriasis erythroderma)
-
Associated Systemic Symptoms:
- Fever, night
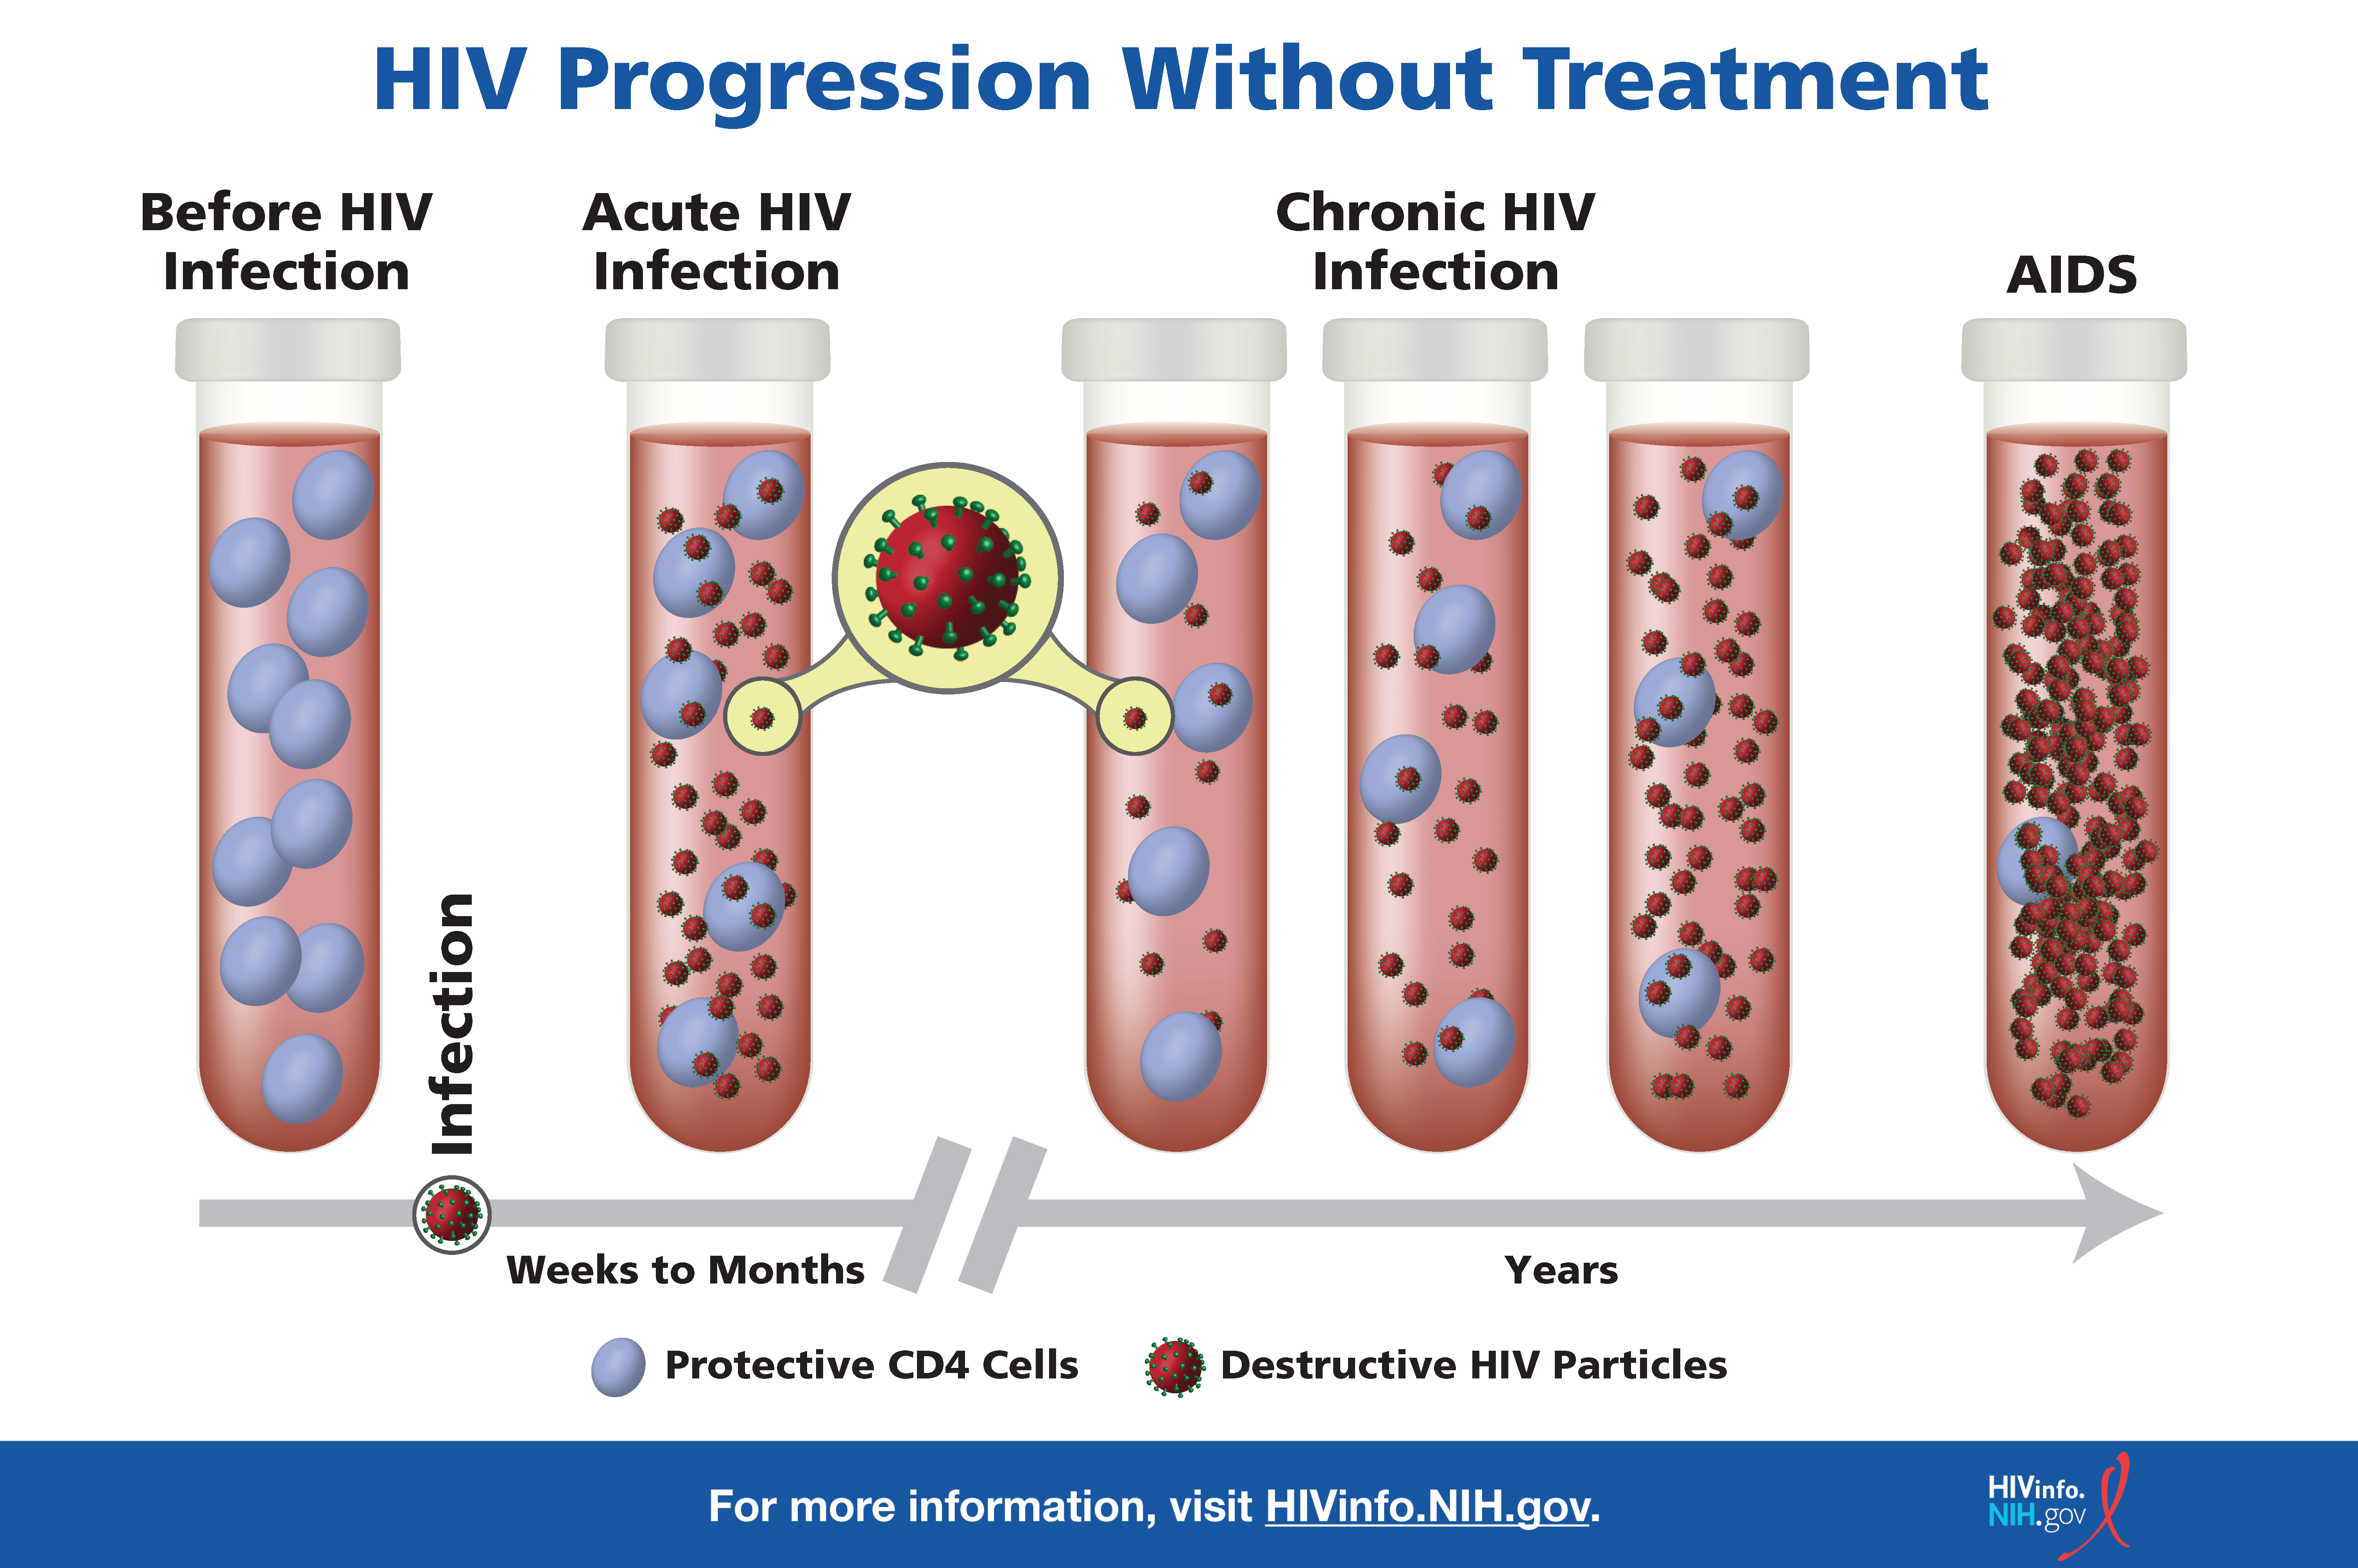
Pathophysiology and Immune System Links in HIV-Associated Skin Rashes (Ruam Kulit)
HIV-associated skin manifestations (ruam kulit) arise from a complex interplay between immune dysregulation, direct viral effects, and secondary infections or malignancies. The progression of HIV infection disrupts immune homeostasis, particularly through CD4+ T-cell depletion, immune activation, and functional exhaustion of immune cells, creating a permissive environment for dermatologic pathologies. Viral load dynamics, ART efficacy, and coinfections further modulate skin lesion presentation, severity, and response to treatment. Understanding these mechanisms is critical for differential diagnosis and targeted therapeutic intervention.
Immune Dysfunction in HIV and Its Role in Skin Lesion Pathogenesis
The progressive decline in CD4+ T-cell counts in HIV infection directly correlates with the emergence of skin rashes, as these cells are essential for Th1/Th2 balance, antigen presentation, and cytokine regulation. Key immune disruptions include:- Loss of Th1-mediated immunity: Impaired interferon-γ (IFN-γ) production weakens cellular responses against intracellular pathogens (e.g., Mycobacterium tuberculosis, HSV), leading to persistent or atypical infections that manifest dermatologically (e.g., disseminated herpes zoster, TB cutaneous lesions).
- Th2 skewing and eosinophilia: Elevated IL-4/IL-5 promotes atopic-like dermatitis and pruritic papular eruptions, common in early HIV stages.
- B-cell dysfunction: Hypogammaglobulinemia increases susceptibility to bacterial superinfections (e.g., Staphylococcus aureus), while autoantibody production may contribute to vasculitic rashes (e.g., leukocytoclastic vasculitis).
- Natural killer (NK) cell exhaustion: Reduced cytotoxic activity fails to control viral reactivation (e.g., CMV, EBV), exacerbating purpuric or necrotic lesions.
Critical Thresholds:
- CD4+ <200 cells/µL: High risk for opportunistic infections (e.g., cryptococcal dermatitis, molluscum contagiosum).
- CD4+ <50 cells/µL: Predisposition to malignancies (e.g., Kaposi sarcoma, B-cell lymphoma with cutaneous involvement).
- Direct HIV-related rashes: Prurigo nodularis, seborrheic dermatitis, and HIV-associated pruritic papular eruptions (HPP) due to cytokine storm (TNF-α, IL-1β).
- Accelerated coinfection progression: Rapid dissemination of HSV (eczema herpeticum), VZV (disseminated zoster), or HPV (condyloma acuminata, bowenoid papulosis).
- Early-stage HIV (CD4+ >500): Erythema multiforme-like reactions, psoriasis exacerbation, or pityriasis rosea-like eruptions.
- Late-stage HIV (CD4+ <200): Atypical presentations of common rashes (e.g., TB cutaneous lesions mimicking pyoderma gangrenosum).
- Immune reconstitution inflammatory syndrome (IRIS): Paradoxical worsening of pre-existing infections (e.g., TB IRIS presenting as erythema nodosum) or unmasking of latent infections (e.g., CMV retinitis with cutaneous vasculitis).
- Drug hypersensitivity: Nevirapine-induced Stevens-Johnson syndrome (SJS) or abacavir hypersensitivity syndrome (maculopapular rash).
Viral Load and ART Status as Modulators of Skin Manifestations
Viral load serves as a biomarker for immune activation and correlates with the severity and type of skin lesions. ART initiation and adherence significantly alter dermatologic presentations:- High viral load (>100,000 copies/mL):
- ART-naïve patients:
ART-Induced Skin Reactions:
- Fever, night
-
Herpesviridae family:
- HSV-1/HSV-2: Chronic ulcers, eczema herpeticum (in atopic dermatitis), or disseminated herpes (CD4+ <100).
- VZV: Disseminated zoster (CD4+ <200) with hemorrhagic crusting or gangrenous lesions.
- HHV-8: Kaposi sarcoma (purple macules/plaques → nodular, ulcerative) linked to latent infection reactivation in immunosuppression.
-
Papillomaviridae (HPV):
- High-risk HPV (16/18): Bowenoid papulosis (verrucous, pigmented lesions), invasive cervical/anal cancer with cutaneous metastases.
- Low-risk HPV (6/11): Giant condylomata acuminata (Buschke-Löwenstein tumors) in late-stage HIV.
-
Mycobacteria:
- TB: Lupus vulgaris (atrophic plaques), erythema nodosum, or scrofuloderma (CD4+ <100).
- MAC (Mycobacterium avium complex): Cutaneous nodules or erythema multiforme-like eruptions.
-
Fungi:
- Cryptococcus neoformans: Molluscum-like papules or acneiform eruptions (disseminated disease).
- Histoplasma capsulatum: Papulonecrotic lesions or erythema multiforme.
-
Bacteria:
- S. aureus: Folliculitis, ecthyma gangrenosum (pseudomonas in neutropenia), or toxic shock syndrome (diffuse erythema).
- Treponema pallidum: Secondary syphilis with palmar/plantar rash (CD4+ <350) or gummatous lesions.
- HIV disease stage: Document CD4 count, viral load, and history of antiretroviral therapy (ART) adherence. Low CD4 (<200 cells/µL) increases susceptibility to opportunistic infections (OIs) such as Pneumocystis jirovecii pneumonia (PJP)-related rashes or Mycobacterium avium complex (MAC) skin lesions.
- Medication review: Identify recent ART initiation, dose adjustments, or concomitant medications (e.g., trimethoprim-sulfamethoxazole, nevirapine, abacavir). Drug-induced rashes (e.g., Stevens-Johnson syndrome, fixed drug eruption) may emerge within 1–3 weeks of exposure.
- Travel and exposure history: Assess for zoonotic infections (e.g., leishmaniasis), vector-borne diseases (e.g., scrub typhus), or occupational hazards (e.g., contact dermatitis from disinfectants in healthcare workers).
- Systemic symptoms: Fever, weight loss, night sweats, or lymphadenopathy suggest systemic OIs (e.g., disseminated histoplasmosis, cryptococcosis) with cutaneous manifestations.
- Morphology and distribution: Note the pattern (e.g., maculopapular, vesicular, pustular, ulcerative) and anatomical sites. For example:
- Generalized pruritic maculopapular rash → Drug eruption (e.g., nevirapine hypersensitivity) or viral exanthems (e.g., HIV seroconversion illness).
- Facial malar rash with photosensitivity → Systemic lupus erythematosus (SLE) flare.
- Painful genital ulcers → Herpes simplex virus (HSV) or syphilis.
- Mucosal involvement: Oral ulcers (e.g., aphthous stomatitis, candidiasis), conjunctivitis, or genital lesions narrow the differential to viral (HSV, CMV), fungal (Candida), or autoimmune (pemphigus) causes.
- Lymphadenopathy: Generalized or localized lymphadenopathy may accompany OIs (e.g., Toxoplasma gondii, MAC) or lymphoproliferative disorders (e.g., lymphoma).
- Complete blood count (CBC): Eosinophilia (>5%) suggests parasitic infections (e.g., strongyloidiasis) or drug hypersensitivity. Thrombocytopenia may indicate disseminated infection (e.g., Mycobacterium tuberculosis).
- Liver function tests (LFTs): Elevated transaminases or bilirubin may reflect drug toxicity (e.g., nevirapine-induced hepatitis) or hepatic OIs (e.g., cryptosporidiosis).
- Renal function tests (RFTs): Creatinine elevation in patients on tenofovir or trimethoprim-sulfamethoxazole may indicate drug-induced interstitial nephritis or acute kidney injury.
- CD4 count and viral load: Correlate with risk of OIs. For example:
- CD4 <100 cells/µL → High risk for Cryptococcus neoformans, Histoplasma capsulatum, or Pneumocystis jirovecii.
- Viral load >100,000 copies/mL → Active viral replication may exacerbate immune-mediated rashes (e.g., psoriasis, seborrheic dermatitis).
- HIV drug resistance testing: If ART failure is suspected, resistance assays guide regimen adjustments.
- Skin scrapings/KOH prep: Detect fungal elements (e.g., Malassezia in seborrheic dermatitis, Candida in intertrigo).
- Tzanck smear: Rapid diagnosis of HSV or varicella-zoster virus (VZV) via multinucleated giant cells.
- Punch biopsy: Indicated for atypical presentations (e.g., violaceous plaques → Kaposi sarcoma; interface dermatitis → drug reaction or lupus).
- Histopathology: Features such as spongiosis (eczema), vasculitis (leukocytoclastic angiitis), or granulomas (sarcoidosis, tuberculosis) guide diagnosis.
- Direct immunofluorescence (DIF): Detects immune deposits in autoimmune blistering diseases (e.g., pemphigus, bullous pemphigoid).
- PCR or culture: For bacterial (e.g., Staphylococcus aureus in folliculitis), viral (e.g., HSV, HPV), or fungal (e.g., Cryptococcus) pathogens.
- Chest X-ray/CT: Evaluates for pulmonary OIs (e.g., PJP, tuberculosis) with cutaneous dissemination.
- Abdominal/pelvic ultrasound: Detects visceral leishmaniasis or lymphoma in patients with nodular rashes.
- Skin ultrasound: Assesses depth of lesions (e.g., superficial vs. deep infections) or identifies subcutaneous abscesses.
- Autoimmune serology: ANA, anti-dsDNA, anti-SSA/SSB for lupus; anti-desmoglein for pemphigus.
- Infectious disease serology: VDRL/RPR for syphilis; HIV serostatus confirmation if undiagnosed.
- Allergy testing: Patch testing for contact dermatitis; intradermal testing for drug hypersensitivity (e.g., abacavir).
- Green branches: High-priority investigations.
- Red branches: Urgent referral required.
- Blue branches: Empiric treatment pending confirmation.
-
Step 1: Assess Rash Morphology and Distribution
-
Generalized pruritic maculopapular rash
-
Onset within 1–3 weeks of new medication
- Drug eruption (e.g., nevirapine, abacavir) → Green: Discontinue suspect drug; skin biopsy if severe (e.g., SJS/TEN).
- HIV seroconversion illness → Blue: Supportive care; monitor CD4/viral load.
-
Chronic, relapsing course
- Psoriasis or seborrheic dermatitis → Green: CD4 count; treat with topical steroids/ART optimization.
- Atopic dermatitis → Green: IgE levels; avoid triggers (e.g., Malassezia in seborrheic dermatitis).
-
Onset within 1–3 weeks of new medication
-
Localized papulosquamous lesions (e.g., scalp, face)
- Scaly, greasy plaques → Green: KOH prep for Malassezia; treat with ketoconazole cream.
- Violaceous nodules/plaques → Red: Skin biopsy for Kaposi sarcoma (HHV-8); refer to oncology.
-
Ulcerative or necrotic lesions
-
Painful genital ulcers
- HSV-2 (most common) → Green: PCR swab; acyclovir.
- Syphilis (painless, indurated) →
Treatment Protocols and Management Strategies for HIV-Associated Skin Rashes (Ruam Kulit)
HIV-associated skin rashes (ruam kulit) require a multidisciplinary approach, integrating antiretroviral therapy (ART) optimization, targeted pharmacological interventions, and supportive dermatological care. Management must address both the underlying immunodeficiency and specific dermatoses, while considering drug interactions, adverse effects, and patient adherence. Pharmacological strategies range from systemic therapies (e.g., antifungals, antivirals, immunomodulators) to topical agents (e.g., corticosteroids, retinoids), with emerging roles for phototherapy and complementary therapies. Dosage adjustments, ART modifications, and psychosocial support are critical to improving outcomes and quality of life.
Pharmacological Interventions for HIV-Associated Skin Rashes
Systemic and topical therapies are selected based on the etiology, severity, and immune status of the patient. Key considerations include:
- ART adjustments to restore immune function (CD4 count >200 cells/µL) and suppress viral replication.
- Antifungal/antiviral agents for opportunistic infections (e.g., Candida, Herpes simplex, Varicella-zoster).
- Topical corticosteroids for inflammatory dermatoses (e.g., seborrheic dermatitis, psoriasis).
- Retinoids and immunomodulators for recalcitrant conditions (e.g., Kaposi’s sarcoma, lichen planus).
Blockade of pro-inflammatory pathways (e.g., TNF-α inhibitors for psoriasis) may be considered in refractory cases, though immunosuppression risks must be weighed against benefits. Probiotics and prebiotics are under investigation for gut-skin axis modulation in HIV-associated dermatoses.
Comparison of Conventional vs. Alternative Therapies for HIV-Associated Dermatoses
The efficacy and safety of conventional pharmacotherapies versus alternative modalities (e.g., phototherapy, herbal remedies) vary by condition. Below is a comparative analysis:
Key Consideration:Treatment Efficacy Data Potential Risks Topical Corticosteroids (e.g., Clobetasol, Hydrocortisone) - Rapid symptom relief for eczema, psoriasis, and allergic contact dermatitis (response within 1–2 weeks).
- Meta-analysis shows ~70% improvement in HIV-associated seborrheic dermatitis with mid-potency steroids (e.g., fluocinolone).
- Systemic absorption risk in large-surface-area applications (Cushing’s syndrome, adrenal suppression).
- Skin atrophy, striae, and telangiectasia with prolonged use.
- Masking of infections (e.g., fungal superinfections).
- Contraindicated in active tuberculosis or untreated viral infections.
Phototherapy (Narrowband UVB, PUVA) - Effective for psoriasis (70–80% clearance) and atopic dermatitis in HIV patients with CD4 >200 cells/µL.
- Reduces photochemotherapy-induced immunosuppression compared to oral PUVA.
- Adjunctive use with biologics (e.g., TNF-α inhibitors) enhances response in refractory cases.
- Increased non-melanoma skin cancer risk (especially with PUVA).
- Photosensitivity and premature aging with chronic exposure.
- Limited access in resource-limited settings.
Herbal Remedies (Aloe Vera, Turmeric, Neem) - Aloe vera gel (1% aloin) shows ~50% reduction in pruritus in HIV-associated eczema (small studies).
- Curcumin (turmeric) may modulate NF-κB pathways in inflammatory dermatoses (preclinical evidence).
- Neem oil exhibits antifungal activity against Malassezia (seborrheic dermatitis).
- Lack of standardized dosing and rigorous clinical trials in HIV populations.
- Potential drug interactions (e.g., turmeric with ART via CYP3A4 inhibition).
- Risk of allergenic reactions (e.g., neem-induced contact dermatitis).
Systemic Antifungals (Fluconazole, Itraconazole) - Fluconazole (400 mg/week) achieves ~90% cure rate for Candida infections in HIV.
- Itraconazole (200 mg/day) effective for dermatophytosis (e.g., Trichophyton rubrum).
- Prophylactic use reduces oral/esophageal candidiasis in CD4 <200 cells/µL.
- Hepatotoxicity (itraconazole > fluconazole).
- Drug-drug interactions (e.g., itraconazole + protease inhibitors → QT prolongation).
- Resistance emergence with prolonged use.
Alternative therapies should complement, not replace, evidence-based conventional treatments. Herbal remedies may offer adjunctive benefits but require individualized monitoring for safety and efficacy.
Patient-Centered Care Plan for HIV-Associated Skin Rashes
A holistic management approach integrates dermatological, immunological, and psychological support. Below is a structured care plan for a hypothetical 35-year-old HIV-positive male with severe seborrheic dermatitis (CD4 = 180 cells/µL, viral load <50 copies/mL):
-
Immunological Optimization
- ART reinforcement: Ensure adherence to tenofovir/emtricitabine + dolutegravir to maintain viral suppression and immune recovery.
- Vitamin D supplementation (50,000 IU/week) if deficient, as hypovitaminosis D exacerbates inflammatory dermatoses.
- Probiotic therapy (Lactobacillus rhamnosus 10^9 CFU/day) to modulate gut-skin axis inflammation.
-
Dermatological Management
- Topical therapy:
- Ketoconazole 2% shampoo (2x/week) for Malassezia control.
- Mometasone furoate 0.1% cream (BID for 4 weeks) for inflammation.
- Systemic adjunct:
- Fluconazole 150 mg/week (4 weeks) if fungal culture confirms Candida.
- Phototherapy: Narrowband UVB (3x/week) if topical steroids insufficient after 6 weeks.
- Topical therapy:
-
Psychosocial and Adherence Support
- Cognitive-be
Patient Education and Quality of Life Impact in HIV-Associated Skin Rashes (Ruam Kulit)
HIV-associated skin rashes (ruam kulit) significantly impair patients’ physical and emotional well-being, often leading to stigma, social isolation, and reduced adherence to antiretroviral therapy (ART). Effective patient education and psychosocial support are critical to mitigating these challenges, improving treatment compliance, and enhancing overall quality of life. This section outlines strategies for communicating diagnosis, managing symptoms, and addressing the broader psychosocial needs of patients living with HIV and chronic skin manifestations.
Infographic-Style Description: Daily Life Disruptions from Ruam Kulit
HIV-associated skin rashes disrupt daily functioning through physical discomfort, psychological distress, and social stigma. Below is a structured visual description for an infographic that highlights key areas of impact, designed to raise awareness among patients and caregivers.
Visual Element 1: Physical Symptoms and Pain
Description: A central illustration of a human torso with highlighted rash-prone areas (e.g., face, arms, torso) accompanied by icons of itching, burning, and pain. Text overlay explains:
- Chronic itching (pruritus) disrupts sleep, leading to fatigue and reduced productivity.
- Painful lesions (e.g., herpes zoster, seborrheic dermatitis) limit mobility and personal hygiene practices.
- Secondary infections (e.g., bacterial superinfections) from scratching may require additional medical interventions.
Note: Include a thermometer icon to indicate fever or systemic inflammation associated with severe rashes.
Visual Element 2: Emotional and Social Consequences
Description: A split-screen illustration showing:
- Left side: A person covering their face/arms due to embarrassment, with icons for anxiety, depression, and social withdrawal.
- Right side: A support network (e.g., friends, family, healthcare providers) offering encouragement, with icons for communication and mental health resources.
Key messages:
"Stigma from visible rashes may deter patients from seeking care or disclosing their HIV status, worsening mental health outcomes."
Visual Element 3: Treatment Adherence Barriers
Description: A flowchart with obstacles (e.g., forgetfulness, side effects of ART, cost of skincare products) leading to a "Break in Treatment" box, followed by a "Relapse Risk" warning. Contrast this with a "Consistent Care" path showing proper skincare, ART adherence, and follow-up visits.
Data point: Include a statistic: "Patients with uncontrolled skin rashes are 30% less likely to maintain viral suppression due to ART interruptions." (Source: Adapted from WHO 2021 guidelines on HIV and dermatological comorbidities.)
Key Counseling Points for Healthcare Providers
Effective communication between healthcare providers and patients is essential for managing ruam kulit and improving long-term outcomes. The following counseling points address medical adherence, skincare, emotional support, and practical coping strategies.
Patients with HIV-associated skin rashes often experience information overload and may struggle to prioritize self-care amid competing health concerns. Providers should:
-
Explain the link between HIV progression and skin manifestations.
"Skin rashes in HIV patients may indicate immune dysfunction (e.g., CD4 <200 cells/µL) or opportunistic infections (e.g., fungal, viral). Early treatment of rashes can improve immune recovery and ART efficacy."
-
Clarify misconceptions about contagion and stigma.
Many patients fear transmitting their condition through skin contact. Emphasize:
- Most HIV-associated rashes (e.g., seborrheic dermatitis, psoriasis) are not contagious.
- ART reduces viral load, minimizing transmission risk even with visible lesions.
- Encourage wearing lightweight, breathable clothing to reduce discomfort while maintaining dignity.
-
Provide tailored skincare instructions.
Routine skincare can alleviate symptoms but may be complicated by ART side effects (e.g., xerosis from efavirenz). Recommend:
- Gentle cleansers (e.g., fragrance-free syndet bars) to avoid stripping natural oils.
- Moisturizers with ceramides or urea (e.g., 5–10% urea cream for dry, scaly rashes).
- Avoid hot water, harsh soaps, and exfoliants that exacerbate irritation.
- For fungal rashes (e.g., candidiasis), prescribe topical antifungals (e.g., clotrimazole) and explain proper application.
-
Address pain management and itch relief.
Chronic itching and pain can lead to sleep deprivation and reduced quality of life. Suggest:
- Topical corticosteroids (e.g., hydrocortisone 1%) for inflammatory rashes, with tapering schedules to avoid atrophy.
- Oral antihistamines (e.g., hydroxyzine) for nocturnal pruritus, cautioning against sedative effects.
- Cool compresses or lukewarm oatmeal baths (colloidal oatmeal) for immediate relief.
- Refer to pain clinics if neuropathic pain (e.g., from herpes zoster) persists.
-
Reinforce ART adherence and immune monitoring.
Skin rashes often improve with CD4 recovery and viral suppression. Counsel patients on:
- The importance of consistent ART dosing, even if rashes temporarily worsen (e.g., during immune reconstitution inflammatory syndrome, IRIS).
- Regular CD4 counts and viral load tests to track immune response.
- Reporting new or worsening symptoms (e.g., fever, pus, spreading lesions) promptly.
-
Offer emotional and practical support.
Patients may experience depression, shame, or caregiver burden. Provide resources such as:
- Psychosocial counseling (e.g., cognitive behavioral therapy for stigma-related distress).
- Peer support groups (e.g., HIV-positive patient networks like The Body or local NGO programs).
- Financial assistance programs for ART or skincare products (e.g., patient assistance programs from manufacturers).
- Cultural sensitivity training for providers to address language barriers or traditional beliefs about HIV.
Symptom-Tracking Template for Patients
Monitoring rash severity, triggers, and treatment responses empowers patients to communicate effectively with healthcare providers and adjust self-care strategies. Below is a fillable table template designed for patient use, incorporating visual analog scales (VAS) for subjective symptoms and space for provider notes.
Date Rash Location(s) Severity (1–10) Type of Rash Triggers/Symptoms Treatment Used Response (Improved/Stable/Worse) Provider Notes Understanding ruam kulit in HIV patients transcends symptom recognition, demanding an integrated approach that addresses biological, psychological, and systemic dimensions of care. From the diagnostic nuances of distinguishing Kaposi’s sarcoma from drug-induced exanthems to the tailored pharmacological and psychosocial interventions required for patient stabilization, the management of these conditions underscores the necessity of multidisciplinary collaboration. As research continues to elucidate the complex interplay between HIV pathogenesis and dermatological manifestations, clinicians must remain vigilant in adapting therapeutic strategies to evolving viral dynamics and patient-specific needs. Ultimately, the successful management of ruam kulit not only alleviates physical discomfort but also reinforces trust in healthcare systems, fostering adherence and resilience in affected populations.
- Cognitive-be
-
Painful genital ulcers
-
Generalized pruritic maculopapular rash
Coinfections and Their Dermatologic Impact
Secondary infections and malignancies exacerbate or modify skin lesions in HIV, often presenting with atypical or aggressive features. Key pathogens include:Flowchart: Progression from HIV Infection to Skin Manifestations
The following hierarchical progression illustrates key immune checkpoints leading to dermatologic complications:1. HIV Transmission & Acute Infection
1.1. Immune Activation
- Viral replication → TNF-α, IL-6 spike → seborrheic dermatitis, psoriasis-like plaques.
- CD4+ decline begins (peak viremia → transient rash in ~10–20% of acute HIV).
2. Chronic HIV (CD4+ 200–500)
2.1. Th2 Skewing & Eosinophilia
- Pruritic papular eruptions (HPP), atopic dermatitis, papular urticaria.
- Coinfections emerge: HSV reactivation, HPV warts, TB exposure.
2.2. ART Initiation Risks
- Drug hypersensitivity (e.g., nevirapine SJS, abacavir rash).
- IRIS if latent infections (e.g., TB cutaneous flare).
3. Advanced HIV (CD4+ <200)
3.1. Opportunistic Infections Dominate
- Disseminated HSV/VZV (necrotic ulcers, hemorrhagic crusts).
- MAC/TB cutaneous lesions (nodules, abscesses).
- HHV-8/Kaposi sarcoma (purple plaques
Diagnostic Approaches and Differential Diagnosis in HIV-Associated Skin Rashes (Ruam Kulit)
HIV-associated skin rashes (ruam kulit) present with diverse etiologies, ranging from opportunistic infections to immune dysregulation and drug reactions. Accurate diagnosis requires a systematic evaluation integrating clinical history, laboratory investigations, and dermatological assessment. Misdiagnosis may lead to delayed treatment, progression of underlying conditions, or unnecessary exposure to toxic therapies. This section outlines a structured diagnostic workflow, differential diagnostic strategies, and case-based insights to guide clinicians in distinguishing HIV-related dermatoses from non-HIV mimics.
Step-by-Step Diagnostic Process for Evaluating Ruam Kulit in HIV Patients
A methodical approach ensures comprehensive assessment while minimizing invasive procedures. The process begins with a detailed history, followed by targeted physical examination, and concludes with confirmatory laboratory or imaging studies.
1. Clinical History and Risk Assessment
2. Physical Examination
3. Laboratory Investigations
A. Routine Blood Tests
B. HIV-Specific Markers
C. Skin Biopsy and Microbiological Studies
D. Imaging Studies
4. Serological and Specialized Tests
Decision-Tree for Differentiating HIV-Related Rashes from Non-HIV Causes
The following algorithm prioritizes clinical features, risk factors, and diagnostic yield to streamline evaluation. Branches are organized by primary presentation (morphology/systemic symptoms) and HIV-specific risk factors.Decision-Tree Key:
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.