Eye Goop Booger Science Culture and Care Guide
Table of Contents
- Anatomical and Physiological Origins of Eye Discharge
- Mechanisms of Discharge Formation in Healthy and Pathological States
- Comparison of Eye Discharge in Common Ocular Conditions
- Designing an Infographic: Layers of Eye Discharge
- Cultural and Social Perceptions of Eye Boogers
- Cultural Taboos and Superstitions Surrounding Eye Boogers
- Historical References Linking Eye Discharge to Health, Divination, and Rituals
- Evolution of Perceptions: A Timeline from Humoral Theory to Modern Hygiene
- Hygiene and Removal Techniques for Eye Discharge (Boogers)
- Step-by-Step Instructions for Safe Removal
- Comparison of Removal Solutions: Efficacy and Safety
- Tools and Devices for Removal: Features and Proper Usage
- Medical Conditions Associated with Eye Discharge and Their Clinical Manifestations
- Five Medical Conditions Characterized by Prominent Eye Discharge
- Diagnostic Flowchart for Differentiating Causes of Eye Discharge
- Comparative Analysis of Acute vs. Chronic Eye Discharge
Eye discharge, commonly referred to as eye goop or boogers, serves as a critical yet often overlooked indicator of ocular and systemic health. Originating from specialized glands and cellular activity within the eye, this substance varies in composition—ranging from protective mucus to inflammatory pus—each type reflecting distinct physiological or pathological processes. Beyond its medical significance, eye discharge carries layers of cultural symbolism, from ancient superstitions to modern media portrayals, shaping societal perceptions of hygiene, discomfort, and even humor. Understanding its biological foundations, removal techniques, and associated conditions not only demystifies a universally familiar yet frequently misunderstood phenomenon but also underscores the importance of proper eye care in maintaining overall well-being.
The interplay between anatomy and pathology reveals how eye discharge functions as both a shield and a warning system. For instance, the meibomian glands secrete lipids that prevent evaporation, while the conjunctiva and lacrimal glands produce aqueous and mucin layers essential for lubrication and defense. Disruptions in these processes—whether due to infection, allergies, or environmental irritants—alter the discharge’s appearance, texture, and odor, often serving as early clues for underlying health issues. Meanwhile, cultural narratives surrounding eye boogers span millennia, from Ayurvedic practices linking discharge to dosha imbalances to medieval humoral theories associating it with bodily imbalances. Today, these perceptions persist in memes, children’s media, and even clinical consultations, blending science with societal attitudes toward bodily fluids.
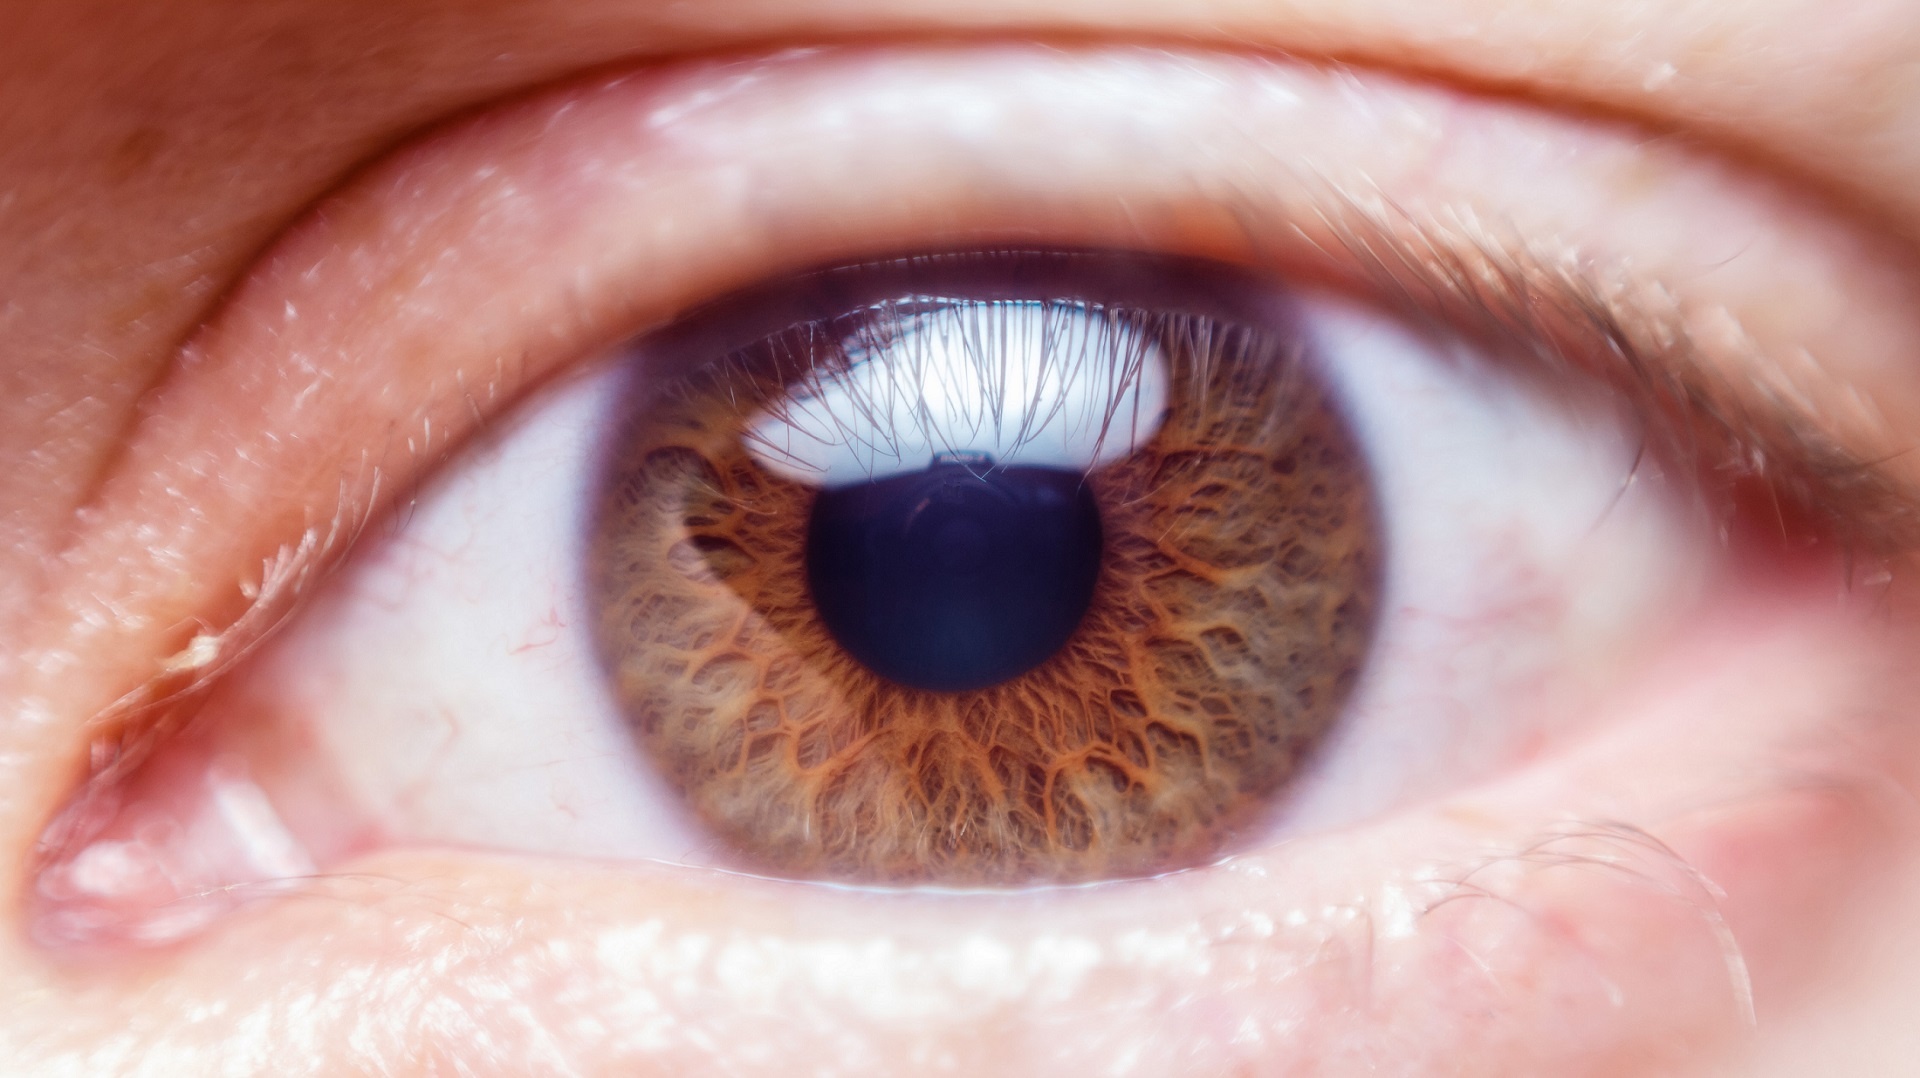
Anatomical and Physiological Origins of Eye Discharge
Eye discharge, commonly referred to as "eye goop" or "boogers," originates from multiple anatomical structures within the ocular surface and adnexal regions. The primary contributors include the meibomian glands, conjunctiva, lacrimal glands, and goblet cells, each playing a distinct role in tear film composition and immune defense. The meibomian glands, located in the tarsal plates of the eyelids, secrete lipids that form the outermost layer of the tear film, preventing evaporation. The conjunctiva, a mucous membrane covering the sclera and inner eyelids, houses goblet cells that produce mucin, a glycoprotein essential for tear film adhesion and microbial trapping. The lacrimal glands, situated in the upper outer orbit, produce the aqueous layer, rich in electrolytes, immunoglobulins (e.g., IgA), and antimicrobial peptides (e.g., lysozyme). Disruptions in these structures—whether due to infection, inflammation, or environmental stressors—lead to altered tear film dynamics, resulting in visible discharge variations.The chemical composition of eye discharge reflects its dual function: maintaining ocular surface hydration and acting as a first-line immune barrier. Mucin (primarily MUC5AC and MUC1) provides viscosity and traps pathogens, while lipids (e.g., wax esters, cholesterol) from meibomian glands stabilize the tear film. Proteins such as lysozyme, lactoferrin, and defensins exhibit antimicrobial activity, while cellular debris (e.g., neutrophils, eosinophils, or epithelial cells) indicates inflammatory or allergic responses. The balance of these components ensures clarity and sterility under normal conditions; deviations signal pathological processes.
Mechanisms of Discharge Formation in Healthy and Pathological States
The formation of eye discharge is governed by tear film turnover and immune cell recruitment. In healthy eyes, the tear film undergoes continuous renewal, with excess fluid and debris drained via the nasolacrimal duct. Mucin-rich discharge may appear as clear, stringy strands upon awakening, primarily composed of dried mucin and cellular remnants. Pathological discharge arises from:The texture and color of discharge correlate with underlying mechanisms:
Comparison of Eye Discharge in Common Ocular Conditions
The following table contrasts the clinical, microscopic, and biochemical features of eye discharge across four conditions, emphasizing diagnostic distinctions:| Feature | Normal Eye Discharge | Bacterial Conjunctivitis | Viral Conjunctivitis | Allergic Reaction |
|---|---|---|---|---|
| Primary Composition | Mucin (MUC5AC), lipids, lysozyme, minimal cellular debris. | Neutrophils (50–90%), bacterial DNA, pus (neutrophil extracellular traps). | Lymphocytes (CD4+, CD8+), viral particles (e.g., adenovirus), minimal neutrophils. | Eosinophils (20–50%), IgE, mast cell granules (histamine, tryptase). |
| Color/Textural Appearance | Clear, thin, or slightly viscous; may form fine crusts overnight. | Yellow-green, thick, purulent; adheres to lashes as crusty boogers. | Watery, stringy mucus; minimal crusting unless secondary bacterial infection. | Thick, grayish-white, stringy; forms dense crusts with serum exudate. |
| Microscopic Findings | Occasional squamous epithelial cells; no inflammatory cells. | Numerous neutrophils, Gram-positive/negative bacteria (e.g., Streptococcus pneumoniae, Haemophilus influenzae). | Lymphocytic infiltration, inclusion bodies (e.g., Cowdry A bodies in HSV). | Eosinophils with Charcot-Leyden crystals, mast cells, elevated IgE. |
| Associated Symptoms | None or mild grittiness; resolves with blinking. | Redness, pain, purulent discharge, swollen eyelids, foreign body sensation. | Watery discharge, photophobia, preauricular lymphadenopathy, follicular conjunctiva. | Itching, chemosis, lid swelling, stringy discharge, no pain. |
| Key Diagnostic Markers | Normal tear film break-up time (TBUT), Schirmer test ≥5 mm. | Positive Gram stain/culture, elevated CRP/IL-6 in severe cases. | PCR detection of viral DNA/RNA, negative bacterial cultures. | Elevated serum IgE, positive skin prick test, eosinophil count >5%. |
Designing an Infographic: Layers of Eye Discharge
An effective infographic illustrating the stratified structure of eye discharge should prioritize clarity and anatomical accuracy. The following elements are critical for visual representation:1. Cross-Sectional Diagram of the Eye
2. Layered Breakdown of Discharge
3. Annotated Microscopic Insets
4. Color-Coding System
5. Pathological Variations
Example Annotation

Cultural and Social Perceptions of Eye Boogers
Eye discharge, commonly referred to as "eye boogers," occupies a unique intersection between biological reality and cultural symbolism. Across civilizations, perceptions of ocular secretions have ranged from medical diagnoses to omens of divine intervention, reflecting broader societal values around health, purity, and spirituality. While modern science demystifies their origins, historical and contemporary interpretations reveal how eye boogers have been embedded in rituals, folklore, and even humor, shaping collective attitudes toward bodily functions and hygiene.The cultural significance of eye boogers extends beyond mere physiological curiosity, serving as a lens to examine societal attitudes toward illness, cleanliness, and supernatural beliefs. From ancient medical texts to viral internet trends, their portrayal evolves alongside technological and hygienic advancements, yet their symbolic weight persists in both reverence and ridicule.
Cultural Taboos and Superstitions Surrounding Eye Boogers
Eye discharge has long been associated with supernatural or moral implications in various cultures, often tied to concepts of bad luck, divine messages, or spiritual contamination. These beliefs frequently stem from pre-scientific understandings of disease and bodily fluids, where eye secretions were interpreted as signs of curses, prophecies, or moral failings.- Bad Luck and Omens in Western Folklore
In medieval Europe, excessive eye discharge was sometimes linked to the "Evil Eye" (malocchio), a malevolent gaze believed to cause misfortune, illness, or even death. Victims of the Evil Eye might exhibit symptoms like redness or discharge, which were interpreted as physical manifestations of hexes. Similarly, in 19th-century American folk medicine, persistent eye boogers were occasionally blamed on "witchcraft" or "cursed" objects, requiring rituals like spitting over the left shoulder or wearing protective charms (e.g., blue beads or iron nails).
"The Evil Eye is a curse resulting from the casting of an envious or malicious glance at a person or object, believed to bring bad luck or injury." — Folklorist Thomas E. Emerson, "The Evil Eye in the New World" (1966)
"The eye is the window to the soul; its discharges may reveal the soul’s distress or the spirits’ whispers." — Adapted from Zulu oral traditions, recorded by D.D.T. Jabavu (1920s)
- Hygiene Taboos in Islamic and Jewish Traditions
In Islamic hygiene practices, eye discharge was classified under hadath (minor ritual impurity), necessitating wudu (ablution) before prayers. The Hadith (sayings of Prophet Muhammad) caution against touching the eyes excessively, as it was believed to invite ayb (shame or sin). Similarly, Jewish law (Halakha) treated eye boogers as a form of tumah (spiritual impurity), with the Mishnah (Talmudic text) advising against sharing towels or eye medications to avoid spreading "uncleanliness." Ritual baths (mikvah) were sometimes recommended for severe cases, symbolizing purification.
Historical References Linking Eye Discharge to Health, Divination, and Rituals
Ancient medical systems often treated eye boogers as diagnostic tools or spiritual markers, blending empirical observation with metaphysical beliefs. These references highlight how ocular secretions were integral to broader frameworks of healing and divination.- Ancient Egypt: Eye Discharge as a Divine Sign
The Ebers Papyrus (c. 1550 BCE), one of the oldest known medical texts, describes eye discharge ("tears of the eye") as a symptom of "worm infestation" or "heat in the head," treatable with honey, milk, and castor oil. However, in temple medicine, persistent boogers were also interpreted as messages from Horus or Thoth, gods associated with vision and wisdom. Priests performing "Eye of Horus" rituals (e.g., wedjat ceremonies) used eye salves containing malachite or lapis lazuli, which may have had antimicrobial properties but were also believed to ward off evil spirits. The Book of the Dead mentions eye discharge as a sign of "the soul’s journey" through the underworld, where Anubis weighed the heart against the feather of Ma’at; cloudy eyes symbolized moral imbalance.
- Ayurveda: Dosha Imbalance and Ritual Therapy
In Ayurvedic medicine (India, c. 1500 BCE–500 CE), eye boogers were classified under Netra Roga (eye diseases) and linked to imbalances in the doshas (bioenergies):
- Traditional Chinese Medicine: Five-Element Theory
TCM associated eye discharge with the Liver Meridian, which governs vision and emotional balance. Excessive boogers were seen as signs of:
Evolution of Perceptions: A Timeline from Humoral Theory to Modern Hygiene
The understanding of eye boogers has shifted from supernatural explanations to scientific hygiene practices, mirroring broader medical and cultural revolutions. Below is a responsive timeline outlining key transitions:| Era | Dominant Theory | Cultural/Social Context | ||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Ancient (3000 BCE–500 CE) | <
| Solution Type | Efficacy (1–5 Scale) | Safety Considerations | Pros and Cons |
|---|---|---|---|
| Commercial Saline Solutions(e.g., Systane, Refresh Plus) | 5 (for mucous/crust) |
|
Pros:
|
| Commercial Eye Wipes(e.g., Johnson’s Baby Wipes, DuraSite) | 4 (for crusty discharge) |
|
Pros:
|
| Homemade Warm Compress(Clean washcloth dipped in warm water) | 4 (for mild crusting) |
|
Pros:
|
| Breastmilk (Infants Only)(Pasteurized, cooled, and diluted 1:1 with water) | 3 (for newborns with mild discharge) |
|
Pros:
|
Tools and Devices for Removal: Features and Proper Usage
Selecting the appropriate tool reduces the risk of injury and improves effectiveness. Below is a breakdown of common devices, their mechanisms, and best practices.1. Cotton Swabs (Q-Tips)
2. Microfiber Cloths
Medical Conditions Associated with Eye Discharge and Their Clinical Manifestations
Eye discharge, commonly referred to as "eye boogers," serves as a critical clinical sign in diagnosing underlying ocular and systemic conditions. While often benign, persistent or atypical discharge may indicate infectious, inflammatory, or allergic etiologies requiring targeted intervention. Below, five prominent conditions are examined, alongside diagnostic frameworks and treatment protocols to guide clinical assessment.Five Medical Conditions Characterized by Prominent Eye Discharge
The following conditions exhibit eye discharge as a primary or secondary symptom, with distinct pathological mechanisms and clinical presentations:-
Blepharitis:
A chronic inflammatory disorder of the eyelid margins, often linked to seborrheic dermatitis, staphylococcal infection, or meibomian gland dysfunction. Key features include:- Thick, greasy, or crusty discharge (often yellowish) adhering to lashes, particularly upon waking.
- Erythematous, swollen, or scaly eyelid margins with possible madarosis (lash loss).
- Associated symptoms: burning, itching, foreign body sensation, and recurrent chalazion formation.
- Chronic cases may develop secondary infections (e.g., hordeolum) or meibomian gland dysfunction.
-
Bacterial Conjunctivitis:
An acute or chronic infection of the conjunctiva, primarily caused by Staphylococcus aureus, Streptococcus pneumoniae, or Haemophilus influenzae. Distinguishing features include:- Purulent discharge (thick, yellow-green, or white), often with matting of eyelids upon awakening.
- Conjunctival hyperemia (redness) and chemosis (swelling), with possible preauricular lymphadenopathy.
- Acute onset with rapid progression; chronic cases may present with intermittent exacerbations.
- Risk factors: poor hygiene, contact lens use, or underlying immunodeficiency.
-
Dacryocystitis:
An infection or inflammation of the lacrimal sac, typically due to obstruction of the nasolacrimal duct. Clinical hallmarks include:- Purulent or mucopurulent discharge from the medial canthus, often with swelling and tenderness over the lacrimal sac.
- Systemic symptoms in acute cases: fever, malaise, and regional lymphadenopathy.
- Chronic dacryocystitis may present with intermittent discharge and recurrent infections.
- Associated with nasolacrimal duct stenosis, trauma, or sinusitis.
-
Trachoma:
A chronic follicular conjunctivitis caused by Chlamydia trachomatis (serovars A-C), leading to blindness if untreated. Key diagnostic features:- Mucopurulent discharge with conjunctival follicles (early stage) progressing to pannus formation (vascularization of the cornea).
- Trichiasis (inguinal lashes) and corneal opacities in advanced stages.
- Endemic in regions with poor sanitation and limited access to healthcare.
- Transmission via direct contact or contaminated fomites (e.g., shared towels).
-
Foreign Body Irritation:
Mechanical trauma from particulate matter (e.g., dust, metal shavings, or plant debris) triggers a reflexive discharge response. Clinical presentation:- Watery or mucoid discharge with conjunctival injection, exacerbated by blinking or eye movement.
- Foreign body sensation, photophobia, and tearing; may develop secondary bacterial infection if untreated.
- Visible foreign body on slit-lamp examination (e.g., rust ring in metallic cases).
- Occupational hazards: welders (metal particles), chemists (powdered chemicals), or agricultural workers (organic debris).
Diagnostic Flowchart for Differentiating Causes of Eye Discharge
The following table provides a structured approach to classifying eye discharge based on color, consistency, and accompanying symptoms. This framework aids in distinguishing between bacterial, viral, fungal, and allergic etiologies:| Symptom/Feature | Likely Etiology |
|---|---|
| Discharge Color: Purulent (yellow-green, thick) | Bacterial: S. aureus, H. influenzae (conjunctivitis); Fungal: Aspergillus (keratitis) |
| Discharge Color: Clear or watery | Viral: Adenovirus (pharyngoconjunctival fever); Allergic: Seasonal rhinoconjunctivitis |
| Discharge Color: Mucoid (white, stringy) | Chronic Inflammation: Blepharitis, dry eye syndrome; Viral: Herpes simplex keratitis (early stage) |
| Discharge Consistency: Thick, crusty (eyelid matting) | Bacterial: S. aureus blepharitis; Chlamydial: Trachoma (follicular conjunctivitis) |
| Discharge Consistency: Thin, watery with itching | Allergic: Pollen, dust mites; Viral: Enterovirus (acute hemorrhagic conjunctivitis) |
| Accompanying Symptoms: Fever, lymphadenopathy | Bacterial: Dacryocystitis, orbital cellulitis; Viral: Herpes zoster ophthalmicus |
| Accompanying Symptoms: Photophobia, corneal involvement | Viral: Herpes simplex/varicella; Fungal: Fusarium keratitis (contact lens-related) |
| Chronic Discharge with Scarring | Chlamydial: Trachoma (advanced); Autoimmune: Stevens-Johnson syndrome |
Note: Overlapping features (e.g., viral vs. allergic discharge) may require microbiological testing (e.g., PCR, cultures) or response to empirical therapy for definitive diagnosis.
Comparative Analysis of Acute vs. Chronic Eye Discharge
The presentation of eye discharge varies significantly between acute and chronic infections, reflecting underlying pathological processes. Below are illustrative descriptions of key differences:-
Acute Infections:
- Odor: Foul-smelling discharge (e.g., Pseudomonas aeruginosa keratitis) or odorless in viral cases.
- Volume: Profuse, often leading to eyelid crusting and matting upon waking (e.g., bacterial conjunctivitis).
- Texture: Thick, tenacious pus (bacterial) or watery mucus (viral); may contain blood in traumatic or necrotizing infections.
- Associated Features: Rapid onset (<24–48 hours), severe discomfort, and systemic symptoms (e.g., fever in dacryocystitis).
-
Chronic Infections:
- Odor: Mild or absent; may develop a stale odor in stagnant cases (e.g., untreated blepharitis).
- Volume: Intermittent, with periods of remission; often minimal
From the microscopic composition of eye discharge to its role in ancient rituals and modern hygiene practices, the study of eye goop boogers bridges biology, culture, and medicine. Recognizing the distinctions between normal secretions and pathological signs—such as the yellow-green pus of bacterial conjunctivitis or the stringy mucus of allergic reactions—empowers individuals to address ocular discomfort promptly and accurately. Equally important is the awareness of cultural and psychological dimensions, where eye discharge may evoke discomfort, humor, or even superstition, highlighting the need for balanced education that respects both scientific facts and societal perceptions. By integrating anatomical knowledge, safe removal techniques, and condition-specific insights, this exploration not only clarifies a common yet complex topic but also reinforces the broader message: eye health is a delicate balance of natural defenses and informed care, worthy of attention at every stage.

Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.