Ebola Virus Symptomen Key Clinical Features Explained
Table of Contents
- Clinical Presentation and Stages of Ebola Virus Disease Progression
- Initial Symptom Onset and Early Indicators
- Acute Phase Progression: Gastrointestinal and Systemic Manifestations
- Advanced Stage: Hemorrhagic and Neurological Complications
- Differentiating Ebola from Other Viral Hemorrhagic Fevers
- Pathophysiology of Ebola Virus Disease: Immune Dysregulation and Organ-Specific Damage
- Mechanisms of Immune Evasion and Dysregulation via Viral Proteins
- Endothelial Damage and Coagulation Cascade Disruption
- Organ-Specific Damage and Systemic Progression
- Diagnostic Challenges and Symptom Overlap with Ebola Virus Disease
- Common Misdiagnosed Conditions and Distinctive Ebola Symptoms
- Priority-Ordered Checklist for Ebola Suspicion in High-Risk Regions
- Limitations of Early Symptom-Based Diagnosis and Laboratory Confirmation
- Comparative Analysis of Symptom Clusters: Sudan vs. Zaire Ebolavirus Strains
- Symptom Management and Supportive Care Protocols in Ebola Virus Disease
- Hydration Strategies for Severe Diarrhea and Vomiting
- Pain Management for Musculoskeletal Symptoms Without Exacerbating Coagulopathy
- Antipyretic Protocols and Risks of Acetaminophen vs. NSAIDs
- Decision-Tree for Triage Based on Symptom Severity and Resource Availability
The Ebola virus remains one of the most lethal pathogens in modern medicine, with its symptoms presenting a complex interplay of systemic dysfunction that distinguishes it from other viral hemorrhagic fevers. Clinical manifestations range from nonspecific early indicators—such as abrupt fever, profound fatigue, and myalgia—to life-threatening complications like coagulopathy and multiorgan failure, all emerging within a critical 2-21-day incubation period. Understanding these progression patterns is essential for early intervention, as delayed recognition exacerbates transmission risks and mortality rates, which can exceed 50% in untreated cases.
Beyond symptom identification, the pathophysiology of Ebola reveals a sophisticated viral strategy: the glycoprotein disrupts immune signaling, while endothelial damage triggers vascular leakage and hemorrhagic manifestations. These mechanisms underscore the urgency of differential diagnosis, particularly in regions where overlapping conditions like malaria or typhoid obscure initial presentations. This analysis bridges clinical observation with molecular insights, equipping healthcare providers with actionable frameworks for symptom management, diagnostic precision, and supportive care in high-risk environments.
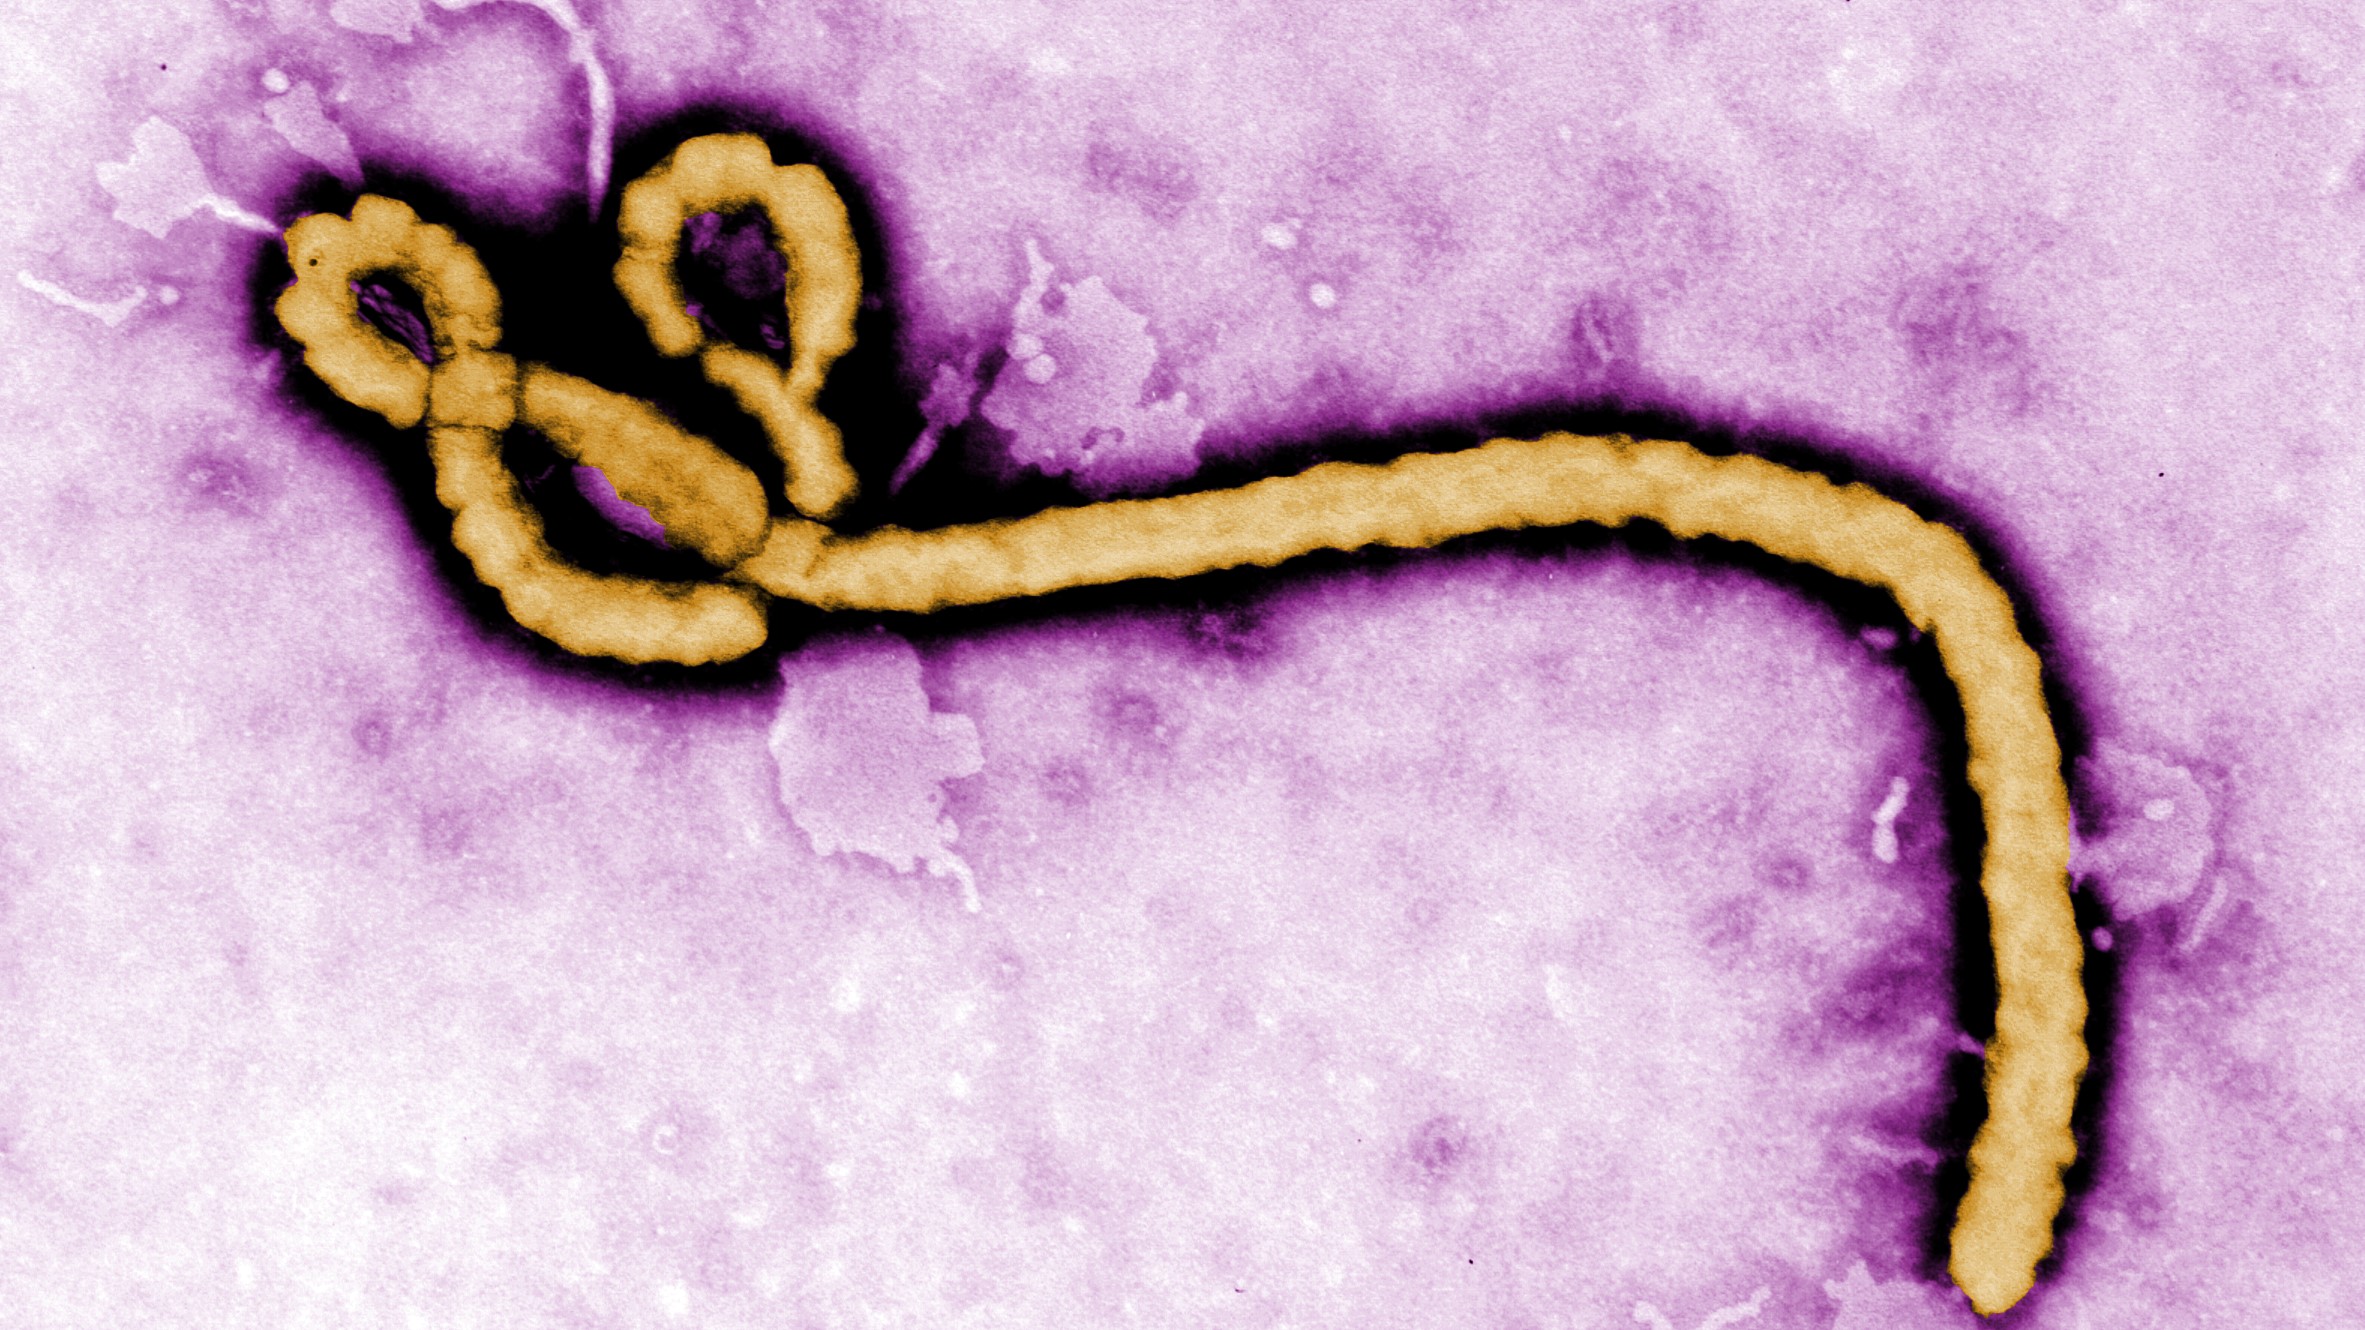
Clinical Presentation and Stages of Ebola Virus Disease Progression
Ebola Virus Disease (EVD) presents with a highly variable but characteristic progression, ranging from asymptomatic or mild cases to severe, often fatal systemic illness. The incubation period—defined as the time between exposure and symptom onset—typically spans 2 to 21 days, with an average of 8 to 10 days. Early symptoms are non-specific, mimicking other viral infections, but their rapid evolution and severity distinguish EVD from common febrile illnesses. Understanding the staged progression is critical for early diagnosis, infection control, and clinical management, as delayed recognition exacerbates transmission risks and mortality.
The disease evolves through distinct phases, beginning with viral entry and systemic dissemination, followed by immune dysregulation and organ dysfunction, and culminating in hemorrhagic or neurological complications in severe cases. Below, the clinical trajectory is dissected into its key stages, supported by mechanistic insights and comparative symptomology to differentiate EVD from other viral hemorrhagic fevers (VHFs).
Initial Symptom Onset and Early Indicators
The prodromal phase of EVD is marked by acute, non-specific symptoms that emerge abruptly after the incubation period. These early manifestations reflect the virus’s initial replication in mononuclear phagocytes and dendritic cells, triggering a systemic inflammatory response. Key features include:- Fever (≥38.3°C), often the first and most consistent symptom, accompanied by chills and diaphoresis.
Mechanism: The Ebola virus (EBOV) enters via mucosal surfaces or skin breaks, replicates in regional lymph nodes, and disseminates via viremia, inducing a pro-inflammatory cytokine storm (e.g., elevated TNF-α, IL-6, IFN-γ). This immune hyperactivation disrupts endothelial integrity, predisposing to later hemorrhagic manifestations.
Clinical Note: Early symptoms overlap with dengue, malaria, or typhoid fever, necessitating differential diagnosis through epidemiological context (e.g., recent exposure in an outbreak zone) and laboratory confirmation (RT-PCR, antigen tests).
Acute Phase Progression: Gastrointestinal and Systemic Manifestations
Within 3 to 5 days of symptom onset, patients enter the acute phase, characterized by gastrointestinal (GI) disturbances and multiorgan dysfunction. These symptoms arise from viral replication in hepatocytes, macrophages, and endothelial cells, leading to liver necrosis, coagulopathy, and capillary leakage.Key features include:
- Vomiting and diarrhea, often watery or bloody, due to intestinal epithelial damage and malabsorption from viral cytopathic effects.
Mechanism:
Critical Differentiator:
Unlike Marburg virus disease (MVD), which often presents with more pronounced early GI bleeding, EVD typically exhibits delayed hemorrhagic signs (days 5–7) and a higher frequency of neurological involvement.
Advanced Stage: Hemorrhagic and Neurological Complications
In severe, untreated cases, EVD progresses to hemorrhagic diathesis and neurological deterioration, reflecting end-stage organ failure. This phase occurs 7–14 days post-onset and is associated with mortality rates exceeding 50% (historically up to 90% in early outbreaks).Key manifestations include:
- Internal and external bleeding:
Mechanism:
Comparative Table: EVD Symptom Progression
| Symptom | Stage of Progression | Mechanism | Severity Level |
|---|---|---|---|
| Fever, myalgia, headache | Early (Days 2–5) | Viral replication in monocytes, cytokine storm (TNF-α, IL-6) | Mild to Moderate |
| Vomiting, diarrhea | Middle (Days 5–7) | Enterocyte infection, immune-mediated intestinal damage | Moderate to Severe |
| Hepatic dysfunction | Middle (Days 5–9) | Hepatocyte necrosis, cholestasis (EBOV glycoprotein-mediated) | Severe |
| Petechiae, mucosal bleed | Late (Days 7–14) | Thrombocytopenia, DIC, endothelial leakage | Severe |
| Neurological symptoms | Late (Days 7–14) | Meningoencephalitis, metabolic encephalopathy, direct viral neurotropism | Severe |
| Massive GI hemorrhage | End-stage | Ulceration, coagulopathy, consumptive thrombocytopenia | Critical |
Differentiating Ebola from Other Viral Hemorrhagic Fevers
While EVD shares clinical overlaps with Marburg, Lassa, and Crimean-Congo hemorrhagic fevers (CCHF), distinct features aid diagnosis:Critical Differentiating Symptoms of EVD:Laboratory Distinctions:
Delayed hemorrhagic onset (typically days 5–7, vs. Marburg’s earlier bleeding). High frequency of neurological complications (seizures, coma) compared to Lassa fever’s (sensorineural hearing loss). Prominent GI symptoms (vomiting/diarrhea) with less frequent early bleeding than CCHF (which often presents with hemorrhagic bullae). Epidemiological link: EVD outbreaks are human-to-human transmission-driven, unlike rodent-borne Lassa or tick-borne CCHF.
Visual Clue: EVD patients often develop a maculopapular rash (days 5–7), whereas dengue rash is retrograde (starts on limbs) and Marburg rash is petechial from onset.
Pathophysiology of Ebola Virus Disease: Immune Dysregulation and Organ-Specific Damage
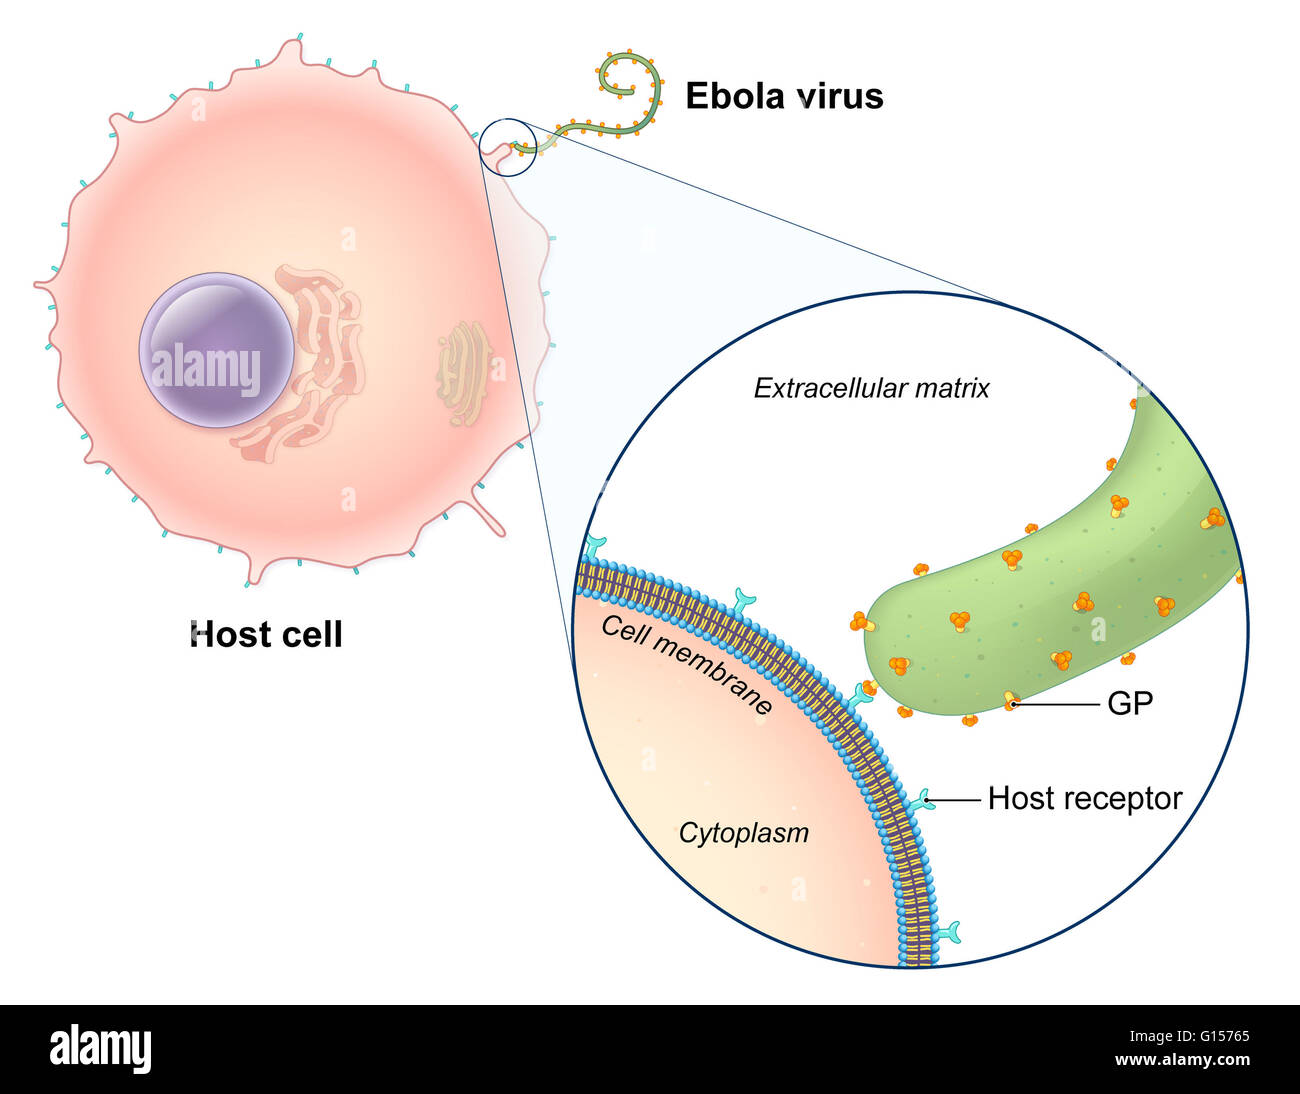
The Ebola virus (EBOV) triggers a cascade of pathological events through its structural proteins, primarily the glycoprotein (GP) and viral proteins such as VP40, VP35, and VP30, which collectively disrupt host immune signaling, endothelial integrity, and organ homeostasis. These disruptions manifest clinically as lymphopenia, immunosuppression, vascular leakage, coagulopathy, and multiorgan dysfunction, reflecting the virus’s ability to evade innate immunity while inducing hyperinflammatory responses. The interplay between viral replication, cytokine storm, and endothelial damage drives progressive organ failure, with liver and kidney dysfunction emerging as critical determinants of mortality.Mechanisms of Immune Evasion and Dysregulation via Viral Proteins
The Ebola virus employs multiple strategies to subvert host immune defenses, primarily through its glycoprotein (GP) and non-structural proteins (e.g., VP35, VP40). These proteins interfere with key immune pathways, including interferon (IFN) signaling, complement activation, and adaptive immune cell function, leading to immunosuppression and delayed viral clearance.Key Immune-Evasion Mechanisms:Consequences of Immune Dysregulation:
VP35 inhibits IFN-α/β production by binding to RIG-I/MDA5 and STING, preventing downstream IRF3/7 activation and NF-κB signaling. GP downregulates MHC-I expression on infected cells, reducing CD8+ T-cell recognition. VP40 disrupts endosomal trafficking of TLR7/9, impairing dendritic cell activation and antigen presentation. sGP (soluble GP) acts as a decoy receptor, binding neutralizing antibodies and complement factor C1q, evading humoral immunity.
Endothelial Damage and Coagulation Cascade Disruption
Ebola virus directly infects endothelial cells and monocytes, triggering vascular leakage, edema, and disseminated intravascular coagulation (DIC). The virus’s GP and VP40 contribute to tissue factor (TF) expression, activating the extrinsic coagulation pathway, while complement activation and cytokine-mediated endothelial dysfunction further destabilize hemostasis.Step-by-Step Pathogenesis of Vascular and Coagulation Dysfunction:
1. Endothelial Cell Infection and Activation
2. Disruption of Endothelial Barrier Integrity
3. Coagulation Cascade Activation and DIC
4. Hemorrhagic Manifestations
Clinical Correlates of Coagulopathy:
Early phase: Thrombocytopenia, prolonged PT/PTT, elevated D-dimer. Late phase: DIC with widespread bleeding (gum, GI, mucosal) and multiorgan failure.
Organ-Specific Damage and Systemic Progression
Ebola virus-induced hypoperfusion, cytokine storm, and direct cytopathic effects lead to targeted organ dysfunction, with the liver, kidneys, and adrenal glands being particularly vulnerable. The progression follows a sequential pattern driven by viral replication, immune-mediated injury, and secondary complications.Flowchart-Style Progression of Organ Damage:
[Viral Entry & Replication in Monocytes/Endothelial Cells]
↓ (Cytokine Storm: TNF-α, IL-6, IFN-γ)
↓
[Systemic Inflammation → Endothelial Leakage → Hypotension]
↓
┌───────────────────────────────────────────────────────┐
│ Organ-Specific Pathways │
├─────────────────┬─────────────────┬───────────────────┤
│ Liver │ Kidneys │ Adrenal Glands│
├─────────────────┼─────────────────┼───────────────────┤
│ - Hepatocyte infection → apoptosis (via TNF-α/Fas) │
│ - Cholestasis (GP-mediated bile duct damage) │
│ - Jaundice (conjugated hyperbilirubinemia) │
│ - Hepatic necrosis (massive transaminase elevation)│
├─────────────────┼─────────────────┼───────────────────┤
│ - Renal hypoperfusion → ATN (acute tubular necrosis)│
│ - Dehydration (vomiting/diarrhea) → prerenal AKI│
│ - Direct podocyte damage (via immune complexes) │
│ - Oliguric/anuric failure (creatinine >3 mg/dL) │
├─────────────────┼─────────────────┼───────────────────┤
│ - Adrenal hemorrhage (from DIC/thrombosis) │
│ - Cortisol deficiency (hypotension, shock) │
│ - Relative adrenal insufficiency (common in survivors)│
└─────────────────┴─────────────────┴───────────────────┘
↓
[Multiorgan Failure → Septic Shock → Death (if untreated)]
Key Mechanisms in Organ Damage:
-
Liver Dysfunction:
- Direct cytopathic effect: EBOV infects hepatocytes via NPC1, inducing apoptosis (caspase-8 activation).
- Immune-mediated injury: TNF-α and IFN-γ trigger hepatocyte necrosis, while NK cells contribute to liver damage.
- Cholestasis: GP-mediated bile duct epithelial cell death leads to obstructive jaundice.
- Clinical markers: Elevated ALT/AST (>10x ULN), hyperbilirubinemia, coagulopathy (INR >1.5).
-
Kidney Failure:
- Prerenal AKI: Hypovolemia (vomiting/diarrhea, capillary leakage) reduces glomerular filtration.
- Intrinsic AKI: ATN from ischemic injury and direct viral infection of tubular cells.
- Immune complex deposition (anti-EBOV antibodies) causes glomerulonephritis.
- Clinical markers: Oliguria, creatinine >2 mg/dL, proteinuria, hematuria.
-
Adrenal Insufficiency:
- Adrenal hemorrhage (from DIC or direct viral infection) leads to acute adrenal crisis.
- Cortisol deficiency exacerbates hypotension and shock, mimicking septic shock.
- Post-recovery adrenal dysfunction (secondary
- Typhoid Fever: Fever, headache, and relative bradycardia may overlap, but EVD progresses to severe gastrointestinal symptoms (e.g., vomiting blood, watery diarrhea with mucus) and profound weakness within 5–7 days.
- Cholera: Profuse watery diarrhea is seen in both, but EVD diarrhea is often bloody or mucous-containing, accompanied by high fever and systemic collapse rather than isolated dehydration.
- Dengue Fever: Similar febrile phase with myalgia, but EVD lacks retro-orbital pain and rash, instead progressing to organ failure (hepatitis, nephritis).
- Meningitis: Early EVD may mimic bacterial meningitis with fever and altered mental status, but lack of neck stiffness (due to coagulopathy) and hemorrhagic skin lesions differentiate it.
- Sudden-onset high fever (≥38.5°C) with conjunctival injection (red, watery eyes).
- Severe headache and myalgia progressing to prostration within 24–48 hours.
- Gastrointestinal hemorrhage (hematemesis, melena) or watery diarrhea with blood/mucus.
- Unilateral or bilateral periorbital edema (rare in other febrile illnesses).
- Hypotension and tachycardia disproportionate to fever (early sign of vascular leakage).
- Petechial or purpuric rash (late-stage, indicating DIC).
- History of exposure (e.g., contact with EVD cases, consumption of bushmeat, or healthcare worker exposure).
- Epidemiological Context: In non-outbreak settings, a low pre-test probability reduces EVD likelihood, but any fever with hemorrhagic signs in a high-risk region warrants suspicion.
- Strain-Specific Variations: The Sudan ebolavirus strain may present with more pronounced neurological symptoms (e.g., seizures, coma) earlier than the Zaire ebolavirus strain, which often progresses to hepatic and renal failure before neurological involvement.
- False Negatives: Early in illness (<5 days), RT-PCR may yield false negatives due to low viral load; repeat testing at 48–72-hour intervals is critical.
- Non-Specific Early Phase: Fever, myalgia, and headache are shared with ≥20 tropical infections, delaying recognition by 3–7 days—the window when supportive care is most effective.
- Strain-Dependent Presentation: The Bundibugyo ebolavirus strain may cause more pronounced skin lesions early, while Reston ebolavirus (non-pathogenic to humans) lacks hemorrhagic features entirely.
- Immunocompromised Patients: HIV/AIDS or malnutrition may attenuate symptoms, leading to misdiagnosis as sepsis or tuberculosis.
- Gold standard for viral detection (sensitivity: 95–100% after day 5).
- Targets Ebola glycoprotein (GP) or nucleoprotein (NP) genes.
- False negatives occur in <5% of cases if tested too early (<5 days post-symptom onset). 2. Antigen Detection Tests (e.g., Rapid Ebola Antigen Test):
- Point-of-care utility in resource-limited settings (e.g., ReEBOV Antigen Rapid Test by Standard Diagnostics).
- Sensitivity: ~80–90% but decreases with low viral load (<7 days post-onset). 3. Serology (IgM/IgG ELISA):
- Useful for retrospective diagnosis (appears 7–10 days post-symptom onset).
- Not recommended for acute diagnosis due to cross-reactivity with other filoviruses.
- Early Testing (<5 Days): Up to 30% false-negative rate in RT-PCR; repeat testing at 48-hour intervals reduces this to <5%.
- Sample Type: Oral swabs may have lower viral load than whole blood; serum or plasma is preferred.
- Strain-Specific Assays: Some PCR tests are Zaire-specific; Bundibugugyo or Sudan strains may require alternative primers.
- Clinical Correlation: Hemorrhagic manifestations + exposure history should prompt empirical isolation even with negative initial tests.
- Contraindications to ORS: Persistent vomiting, altered mental status, or hemodynamic instability.
- Monitoring Parameters: Serial assessment of weight, skin turgor, capillary refill, and urine specific gravity (1.010–1.030).
- Electrolyte Replacement: Magnesium and phosphate deficits may occur in prolonged diarrhea; supplementation is guided by laboratory values.
- Increased bleeding risk (via platelet inhibition).
- Renal impairment (NSAIDs reduce glomerular filtration rate in hypovolemic patients).
- Potentiation of hepatic dysfunction (common in EVD with elevated transaminases).
- Gabapentinoids (e.g., gabapentin 100–300 mg TID) for neuropathic pain, though efficacy in EVD is anecdotal.
- Topical lidocaine patches for localized muscle pain, avoiding systemic absorption risks.
- Platelet counts <50,000/µL or prolonged PT/INR necessitate opioid dose reduction or alternative analgesia.
- Fresh frozen plasma (FFP) or cryoprecipitate may be required pre-procedure if invasive pain management (e.g., nerve blocks) is needed.
- Mechanism: Inhibits prostaglandin synthesis in the CNS, with minimal anti-inflammatory effects.
- Dosing: 650 mg every 4–6 hours (max 4 g/day) in adults; 10–15 mg/kg every 6 hours (max 90 mg/kg/day) in children.
- Advantages:
- No platelet inhibition (safe in coagulopathy).
- Minimal renal toxicity (critical in hypovolemic patients).
- Risks:
- Hepatotoxicity at high doses or in patients with pre-existing liver dysfunction (common in EVD with ALT/AST >10× ULN).
- Overdose potential in settings with limited monitoring.
- Contraindicated in EVD due to:
- Platelet dysfunction (increased bleeding risk).
- Renal vasoconstriction (worsening oliguria in hypovolemic patients).
- Potentiation of hepatic injury (via inhibition of cyclooxygenase-1 in an already stressed liver).
- Exception: Low-dose aspirin (75–100 mg/day) may be considered for secondary thromboprophylaxis in non-hemorrhagic patients with elevated D-dimer (>1000 ng/mL) and no active bleeding, though evidence is limited.
- Metamizole (Dipyrone): Used in some resource-limited settings due to rapid onset and low bleeding risk, but contraindicated in G6PD deficiency and associated with agranulocytosis.
- Intravenous Paracetamol: Preferred in critically ill patients with poor oral tolerance, administered as 1 g every 6 hours (max 4 g/day).
- Liver enzymes (ALT, AST, bilirubin) every 48 hours in patients on acetaminophen.
- Renal function (creatinine, BUN) with NSAID use (though avoided in EVD).
- No bleeding (e.g., petechiae, mucosal bleeding, hematemesis):
- Mild symptoms (fever, myalgia, diarrhea without dehydration):
- Outpatient management (if safe transport and follow-up are possible).
- Oral rehydration (ORS), acetaminophen, and supportive care.
- Moderate symptoms (fever >39°C, persistent vomiting/diarrhea, tachycardia):
- Inpatient isolation with IV fluids (crystalloid bolus), acetaminophen, and monitoring.
- Consider low-dose opioid if pain refractory to acetaminophen (e.g., hydromorphone 0.2 mg IV).
- Hemorrhagic manifestations (e.g., epistaxis, gum bleeding, melena, hematemesis):
- Severe coagulopathy (platelets <50,000/µL, PT/INR >1.5):
The clinical spectrum of Ebola virus disease underscores the imperative for vigilance in high-risk settings, where symptom overlap with endemic illnesses can delay critical interventions. From the viral glycoprotein’s immune evasion tactics to the cascading organ damage driven by cytokine storms, each phase of progression demands a structured approach—whether through targeted supportive care, rapid laboratory confirmation, or stringent infection control. By synthesizing symptom timelines, pathophysiological pathways, and evidence-based management strategies, this overview provides a foundation for clinicians to navigate the challenges of Ebola diagnosis and treatment. The lessons learned from past outbreaks remain indispensable in mitigating future threats, reinforcing the need for global preparedness and localized surveillance.

Diagnostic Challenges and Symptom Overlap with Ebola Virus Disease
Ebola virus disease (EVD) presents significant diagnostic challenges due to its non-specific early symptoms, which closely mimic those of endemic tropical infections. Misdiagnosis delays critical interventions, exacerbates transmission risks, and reduces survival rates. The overlap with diseases like malaria, typhoid fever, and cholera—common in high-burden regions—further complicates clinical decision-making. This section examines the most frequently misdiagnosed conditions, distinctive Ebola-specific symptoms, and a prioritized diagnostic checklist to improve early detection. It also evaluates the limitations of symptom-based diagnosis and the necessity of laboratory confirmation, including strain-specific variations in clinical presentation.Common Misdiagnosed Conditions and Distinctive Ebola Symptoms
EVD often shares initial symptoms with endemic infections, leading to delayed recognition. The following conditions are frequently misdiagnosed in Ebola outbreaks:- Malaria: High fever, chills, and myalgia are common to both, but EVD lacks the cyclical paroxysms of malaria and may present with conjunctival injection (red eyes) and hemorrhagic manifestations (e.g., petechiae, epistaxis) in later stages.
Distinctive Ebola Symptoms for Differential Diagnosis
The following signs, when present, significantly increase EVD suspicion:
Priority-Ordered Checklist for Ebola Suspicion in High-Risk Regions
The following table provides a structured approach to triaging patients in Ebola-endemic or outbreak settings, prioritized by symptom severity and epidemiological risk.| Symptom | Likelihood of Ebola | Recommended Immediate Action |
|---|---|---|
| Sudden high fever (≥38.5°C) + conjunctival injection + history of exposure | High | Isolate patient in a dedicated Ebola Treatment Unit (ETU); initiate PCR testing (whole blood, serum, or oral swab). |
| Watery diarrhea with blood/mucus + vomiting blood + hypotension | High | Isolate immediately; start IV fluids and blood products if DIC suspected; confirm with RT-PCR. |
| Severe headache + myalgia + relative bradycardia (paradoxical in EVD) | Medium-High | Isolate; rule out malaria (rapid diagnostic test) and typhoid; proceed with Ebola PCR if endemic. |
| Unilateral periorbital edema + petechiae | High | Isolate; do not wait for lab confirmation; assume EVD and treat accordingly. |
| Fever + gastrointestinal symptoms (diarrhea/vomiting) without hemorrhagic signs | Medium | Isolate; test for cholera, typhoid, and EVD simultaneously; prioritize EVD PCR if outbreak declared. |
| Altered mental status + neck stiffness (without rash) | Low-Medium | Lumbar puncture for meningitis; if negative, consider EVD PCR if exposure history exists. |
| Fever + rash (maculopapular) without hemorrhagic features | Low | Rule out dengue/chikungunya; if no exposure history, EVD unlikely but test if in outbreak zone. |
Limitations of Early Symptom-Based Diagnosis and Laboratory Confirmation
Relying solely on clinical symptoms for EVD diagnosis is highly unreliable due to:Laboratory Confirmation Requirements
EVD diagnosis requires laboratory confirmation via:False-Negative Risks and Mitigation Strategies
1. RT-PCR (reverse transcription polymerase chain reaction):
Comparative Analysis of Symptom Clusters: Sudan vs. Zaire Ebolavirus Strains
While both strains cause severe systemic illness, strain-specific clinicalSymptom Management and Supportive Care Protocols in Ebola Virus Disease
Supportive care remains the cornerstone of Ebola Virus Disease (EVD) management, as no licensed antiviral therapy exists for routine clinical use. Evidence-based protocols must address dehydration, systemic inflammation, coagulopathy, and organ dysfunction while minimizing iatrogenic harm. The severity of symptoms—ranging from mild gastrointestinal distress to severe hemorrhagic manifestations—dictates the urgency and intensity of interventions. Resource availability further influences treatment strategies, particularly in low-resource settings where intravenous fluids, laboratory monitoring, and specialized pain management may be limited. This section outlines structured approaches to hydration, analgesia, antipyretic therapy, and triage decision-making, alongside infection control measures critical to preventing nosocomial transmission during high-risk procedures.Hydration Strategies for Severe Diarrhea and Vomiting
Dehydration and electrolyte imbalances are leading causes of morbidity and mortality in EVD, exacerbated by profuse diarrhea (up to 10–15 L/day) and vomiting. Oral rehydration solutions (ORS) are the first-line intervention for mild-to-moderate dehydration, provided the patient retains the ability to swallow and has no persistent vomiting. The World Health Organization (WHO) recommends a solution containing sodium (75 mmol/L), potassium (20 mmol/L), glucose (75 mmol/L), and chloride (65 mmol/L), administered in volumes of 50–100 mL/kg over 4–6 hours for initial repletion, followed by maintenance doses of 10–15 mL/kg per diarrheal stool or emesis.For patients with severe dehydration (tachycardia >120 bpm, orthostatic hypotension, oliguria) or those unable to tolerate oral intake, intravenous (IV) fluid resuscitation is mandatory. Crystalloid solutions (e.g., balanced salt solutions like Plasmalyte or Ringer’s lactate) are preferred over normal saline to avoid hyperchloremic acidosis and metabolic disturbances. Initial bolus administration of 20–30 mL/kg over 30–60 minutes is recommended, with subsequent rates adjusted based on urine output (0.5–1 mL/kg/hour in adults) and central venous pressure (CVP) monitoring if available. Hypokalemia (common due to gastrointestinal losses) requires potassium chloride supplementation (10–20 mEq/L in IV fluids), with caution in patients with renal impairment or oliguria.
Key Considerations:
Pain Management for Musculoskeletal Symptoms Without Exacerbating Coagulopathy
Muscle and joint pain are near-universal in EVD, often preceding fever and gastrointestinal symptoms. Non-opioid analgesics are preferred initially due to the risk of opioid-induced respiratory depression and worsening coagulopathy (via platelet dysfunction). Acetaminophen (paracetamol) is the safest first-line agent, with dosing adjusted for hepatic impairment (common in EVD due to transaminitis). The recommended dose is 650 mg every 6 hours (maximum 4 g/day) in adults, with 10–15 mg/kg every 6 hours in children, avoiding exceeding 90 mg/kg/day.For moderate-to-severe pain unresponsive to acetaminophen, low-dose opioids (e.g., morphine 2–5 mg IV/IM every 4–6 hours or hydromorphone 0.2–0.4 mg IV every 4–6 hours) may be considered, with titration to effect and close monitoring of respiratory rate and oxygen saturation. Nonsteroidal anti-inflammatory drugs (NSAIDs) are contraindicated due to:
Alternative Adjuncts:
Coagulation Monitoring:
Antipyretic Protocols and Risks of Acetaminophen vs. NSAIDs
Fever (>38.3°C) is a hallmark of EVD, driven by pyrogenic cytokines (IL-1, IL-6, TNF-α) and viral replication. Antipyretic therapy aims to reduce thermal stress and improve patient comfort, but drug selection must balance efficacy with safety in the context of hepatic and renal dysfunction.Acetaminophen (Paracetamol):
NSAIDs (e.g., Ibuprofen, Diclofenac):
Alternative Antipyretics (Experimental/Off-Label):
Monitoring:
Decision-Tree for Triage Based on Symptom Severity and Resource Availability
Patient triage in EVD must integrate clinical severity, hemorrhagic risk, and available resources to prioritize interventions and allocate limited supplies. Below is a text-based decision tree for acute management, adapted from WHO and CDC guidelines.Step 1: Assess Hemorrhagic Risk
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.