Acne Dunjacka Explored Origins Traits and Solutions
Table of Contents
- Understanding Acne Dunjacka: Origins and Characteristics
- Linguistic and Cultural Roots of the Term
- Dermatological Traits and Physical Manifestations
- Comparison with Other Acne Types: Key Differentiators
- Triggers and Contributing Factors in Acne Dunjacka
- Environmental and Lifestyle Triggers
- Genetic and Hormonal Influences
- Methodology for Tracking Personal Triggers via Journaling
- Lesser-Known Triggers and Clinical Observations
- Cultural and Social Perceptions of Acne Dunjacka
- Regional Perceptions and Stigma
- Media Representations and Viral Adaptations
- Timeline of Cultural References
- Linguistic Nuances and Translations
- Management and Remedies for Acne Dunjacka
- Traditional and Folk Remedies for Acne Dunjacka
- Modern Skincare Ingredients Ranked by Efficacy for Acne Dunjacka
"Acne Dunjacka" represents a distinctive dermatological phenomenon rooted in cultural narratives and clinical observations, bridging traditional medicine and modern skincare discourse. This condition, characterized by its unique presentation—often manifesting as clustered papules with a reddish-purple hue—has evolved beyond regional terminology into a globally recognized term, particularly within Eastern European and Balkan communities. While its exact origins remain debated, linguistic analyses suggest ties to Slavic dialects or internet-driven slang, reflecting how language adapts to describe evolving health perceptions. Beyond physical manifestations, its triggers span dietary habits, hormonal fluctuations, and environmental exposures, demanding a multifaceted approach to management. Understanding "Acne Dunjacka" requires dissecting its historical context, comparative dermatological distinctions, and the interplay between folklore and scientific validation.
The condition’s complexity lies in its dual identity: a medically observable skin disorder and a culturally embedded phenomenon, often discussed in memes, social media, or regional folklore. Comparative studies reveal its divergence from acne vulgaris or hormonal acne, with visual traits such as localized inflammation on the cheeks or jawline. Meanwhile, its triggers—ranging from high-glycemic diets to occupational dust exposure—highlight the need for personalized tracking methods, such as journaling environmental and lifestyle factors. This exploration synthesizes clinical insights with cultural perceptions, offering a comprehensive framework for those seeking to identify, manage, or study this condition.
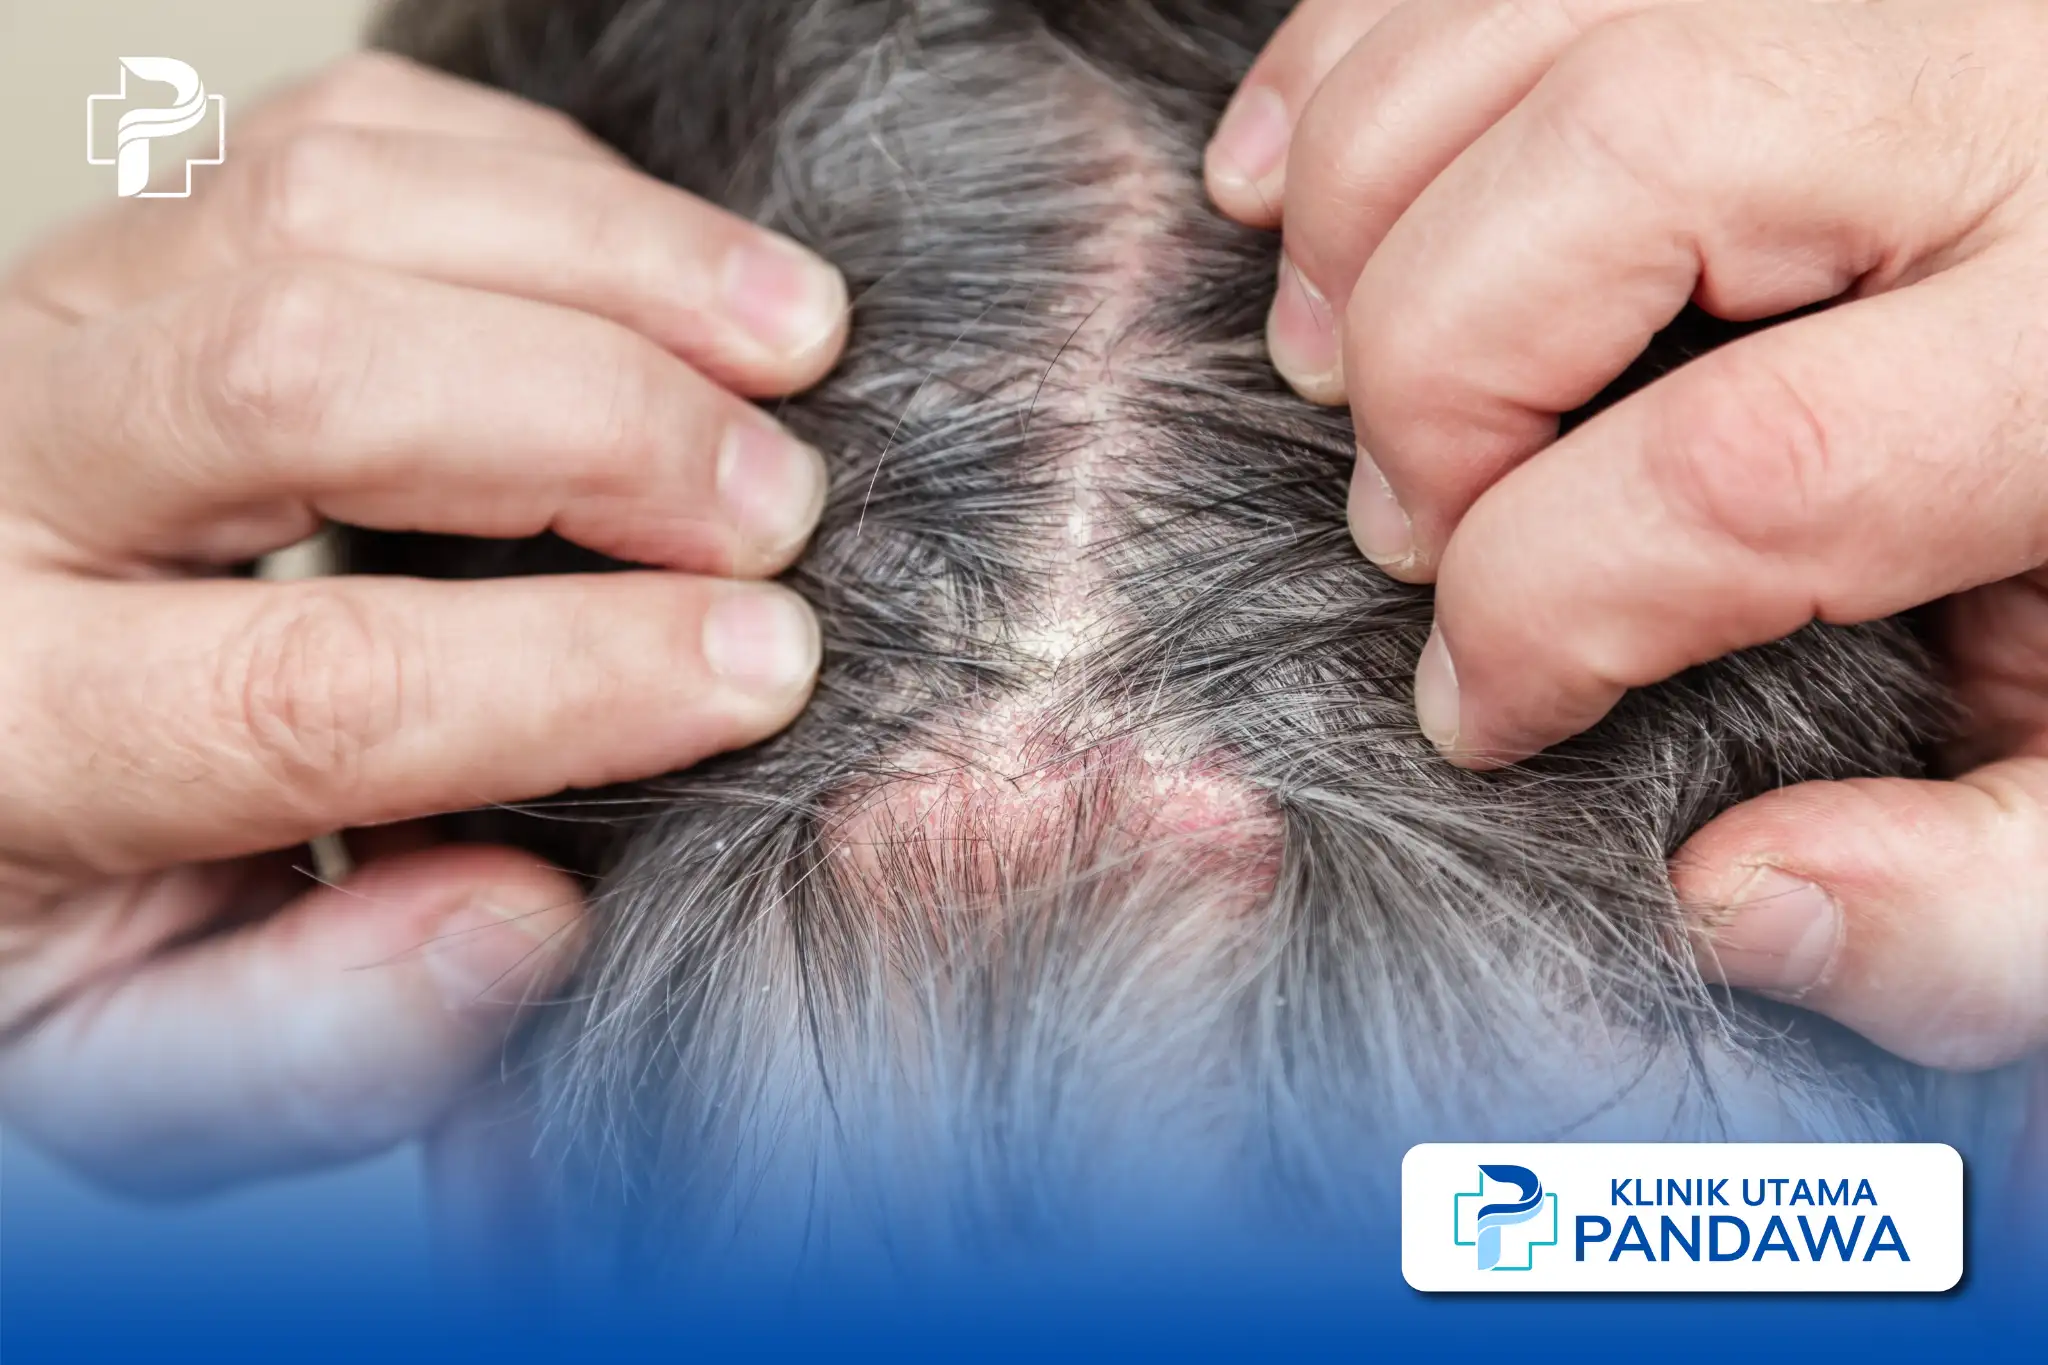
Understanding Acne Dunjacka: Origins and Characteristics
The term "Acne Dunjacka" emerges from a blend of regional linguistic influences, internet subcultures, and dermatological observations, primarily documented in Central and Eastern European online communities. Its origins likely stem from Slavic and Balkan internet slang, where "dunjacka" may derive from colloquial terms for "rough," "uneven," or "inflamed" skin, possibly linked to the verb "dunjati" (to swell or protrude) in some dialects. The term gained traction in forums and social media as a descriptor for a distinct acne phenotype, often discussed alongside humor or frustration over its stubborn resistance to conventional treatments.
While not a formal medical classification, "Acne Dunjacka" reflects a culturally specific perception of acne, distinct from clinically recognized types like acne vulgaris or hormonal acne. Its characteristics are frequently described in visual and tactile terms—small, clustered papules with a reddish-purple or dusky hue, often appearing on the cheeks, jawline, and forehead. Unlike cystic acne, which presents as deep, painful nodules, or hormonal acne (typically larger, inflamed lesions along the jawline), this condition is associated with fine-textured, persistent inflammation that may resemble keratosis pilaris or milia-like eruptions in severity.
Linguistic and Cultural Roots of the Term
The etymology of "Acne Dunjacka" suggests a regional adaptation of dermatological language, where internet communities repurposed slang to describe a shared skincare challenge. Key linguistic influences include:"Acne Dunjacka" functions as a folksonomy—a user-generated label for a dermatological phenomenon lacking a clinical counterpart. Its persistence highlights how language adapts to fill gaps in medical terminology for niche conditions.
Dermatological Traits and Physical Manifestations
Acne Dunjacka is characterized by subtle yet persistent inflammation, often misidentified as dryness, texture issues, or mild acne vulgaris. Key visual and tactile features include:- Lesion morphology:
- Affected areas:
- Texture and sensation:
Dermatologists note that Acne Dunjacka’s traits overlap with follicular hyperkeratosis or acne cosmetica, but its chronic, non-cystic inflammation sets it apart from standard acne vulgaris.
Comparison with Other Acne Types: Key Differentiators
The following table contrasts Acne Dunjacka with clinically recognized acne subtypes, emphasizing visual and pathological distinctions.| Feature | Acne Dunjacka | Acne Vulgaris | Hormonal Acne |
|---|---|---|---|
| Primary Lesion Type | Fine papules (1–3 mm), microcysts, dusky red/violaceous hue; no comedones. | Comedones (whiteheads/blackheads), papules, pustules, cysts. | Inflamed papules/pustules, often larger and deeper along jawline ("hormonal chin acne"). |
| Common Affected Areas | Cheeks, jawline, forehead (avoiding T-zone). | Forehead, nose, chin, back, chest (T-zone predominant). | Jawline, chin, lower cheeks ("mandibular acne"). |
| Texture and Sensation | Rough, "sandpaper-like," tender but not painful. | Oily, may feel greasy; cysts are painful. | Inflamed but less textured; cysts may form. |
| Response to Treatments | Resistant to benzoyl peroxide; improves with retinoids, chemical peels, or keratolytics (e.g., salicylic acid). | Responds to antibiotics, retinoids, or topicals (e.g., clindamycin). | Often improves with spironolactone, oral contraceptives, or topical dapsone. |
| Associated Triggers | Follicular occlusion, dryness, or subclinical inflammation (e.g., from mild eczema or rosacea). | Excess sebum, Cutibacterium acnes, hormonal fluctuations. | Androgens (testosterone), menstrual cycles, PCOS. |
| Post-Inflammatory Changes | Persistent PIH (brown/gray marks), especially in deeper skin tones. | PIH or scars (atrophic/hypertrophic). | Deep scars or acne keloidalis nuchae (in severe cases). |
While Acne Dunjacka lacks a formal ICD-11 code, its keratinization-driven inflammation aligns with acneiform eruptions or follicular acne, warranting targeted therapies like azelaic acid or low-dose tretinoin.

Triggers and Contributing Factors in Acne Dunjacka
Acne Dunjacka, a chronic inflammatory dermatosis with distinct clinical manifestations, arises from a complex interplay of intrinsic and extrinsic factors. While its pathogenesis shares similarities with common acne vulgaris, its severity and resistance to conventional treatments suggest unique triggers and exacerbating mechanisms. Environmental influences, lifestyle habits, and physiological fluctuations collectively modulate the condition’s progression. Understanding these factors enables targeted interventions and personalized management strategies.The interplay between genetic predisposition, hormonal activity, and external exposures defines the variability in Acne Dunjacka presentation. Hormonal fluctuations—such as those during puberty, menstrual cycles, or polycystic ovary syndrome (PCOS)—stimulate sebaceous gland hyperactivity and keratinocyte proliferation, creating a conducive milieu for Cutibacterium acnes colonization. Concurrently, occupational and environmental stressors, including chemical irritants or microbial biofilms, further disrupt epidermal barrier integrity. Below, the primary triggers are categorized and analyzed, alongside practical methodologies for identifying individual susceptibilities.
Environmental and Lifestyle Triggers
Environmental and behavioral factors significantly influence the onset and exacerbation of Acne Dunjacka. High-glycemic diets, for instance, elevate insulin and insulin-like growth factor-1 (IGF-1) levels, promoting sebum production and inflammation via the mTOR pathway. Dairy consumption, particularly skim milk, has been linked to increased IGF-1 bioavailability, correlating with worsened comedonal and inflammatory lesions in susceptible individuals. Stress, mediated through cortisol-induced sebaceous gland stimulation and altered immune responses, exacerbates lesion formation, while seasonal variations—such as increased humidity or UV exposure—disrupt microbial balance and barrier function.Occupational exposures pose additional risks. Prolonged contact with dust, oils, or cosmetics containing comedogenic ingredients (e.g., coconut oil, cocoa butter) clogs follicular openings, while hard water (high in calcium and magnesium) may exacerbate dryness and irritation. Lesser-recognized triggers, such as prolonged smartphone use (leading to microtrauma and bacterial transfer) or synthetic fabric materials (e.g., polyester, which traps moisture and bacteria), contribute to localized inflammation.
Genetic and Hormonal Influences
Genetic predisposition underpins the differential severity of Acne Dunjacka, with studies identifying polymorphisms in genes regulating sebum production (FGF5), immune responses (TLR2), and follicular keratinization (CDSN). Individuals with a family history of acne exhibit higher baseline sebum excretion rates and impaired follicular desquamation, predisposing them to chronic inflammation. Hormonal fluctuations further amplify these effects: androgens (e.g., testosterone) upregulate lipogenesis in sebocytes, while estrogen fluctuations during the menstrual cycle correlate with premenstrual acne flare-ups in up to 70% of affected women.Endocrine disorders, such as PCOS, exacerbate the condition through hyperandrogenism and insulin resistance, creating a feedback loop of increased sebum production and inflammation. Occupational or recreational exposures to endocrine-disrupting chemicals (e.g., phthalates in plastics, parabens in cosmetics) may mimic hormonal effects, worsening symptoms in genetically predisposed individuals.
Methodology for Tracking Personal Triggers via Journaling
Systematic tracking of potential triggers enables individuals to identify patterns and adjust lifestyle modifications accordingly. Below is a structured journal format for daily recording, designed to capture multifaceted variables influencing Acne Dunjacka:| Date | Diet | Stress Level (1-10) | Skin Condition (Lesion Count/Type) | Environmental Factors |
|---|---|---|---|---|
| YYYY-MM-DD | Foods consumed (e.g., high-glycemic, dairy, processed) | Subjective stress assessment (e.g., work deadlines, sleep quality) | Number/type of lesions (comedones, papules, pustules) | Exposures (e.g., hard water, cosmetics, occupational dust) |
Analysis Tips:
Lesser-Known Triggers and Clinical Observations
Beyond conventional triggers, several underrecognized factors contribute to Acne Dunjacka exacerbation. These include:Supporting Evidence:
- Prolonged Smartphone Use: Studies in dermatology journals highlight a correlation between extended phone contact (e.g., gaming, social media) and "acne mechanica" on the chin and cheeks. The combination of pressure, heat, and bacterial transfer (S. epidermidis, C. acnes) disrupts the skin barrier, particularly in individuals with oily skin.
- Hard Water Exposure: Water with high mineral content (e.g., calcium, magnesium) strips natural oils, leading to compensatory sebum overproduction. Clinical cases report worsened acne in regions with hard water, mitigated by water softeners or distilled water cleansing.
- Synthetic Fabric Materials: Fabrics like polyester and nylon trap sweat and bacteria, creating a humid microenvironment conducive to Malassezia overgrowth and folliculitis. Athletes and individuals wearing tight clothing (e.g., uniforms, leggings) exhibit higher rates of acne in covered areas.
- Sleep Deprivation: Chronic sleep deficiency (<6 hours/night) elevates cortisol and ghrelin (a hunger hormone linked to insulin resistance), exacerbating inflammatory lesions. Polysomnography studies in acne patients reveal correlations between poor sleep quality and lesion severity.
- Air Pollution (PM2.5/PM10): Urban dwellers exposed to particulate matter exhibit increased oxidative stress and C. acnes biofilm formation. Longitudinal studies in cities like Beijing and Delhi show seasonal acne flare-ups coinciding with high pollution indices.

Cultural and Social Perceptions of Acne Dunjacka
The term "Acne Dunjacka" transcends its dermatological origins to become a cultural phenomenon, reflecting societal attitudes toward skin health, masculinity, and humor in Eastern Europe and the Balkans. Its perception varies significantly across regions, shaped by historical stigma, evolving media representations, and linguistic nuances. While in some contexts it is treated as a medical condition, in others, it has been reclaimed as a source of humor, folklore, or even a badge of authenticity. This section examines how the term is interpreted in different cultural landscapes, its adaptation in digital and traditional media, and the role of language in reinforcing or challenging its connotations.Regional Perceptions and Stigma
In Eastern Europe and Balkan cultures, Acne Dunjacka is often associated with adolescence, masculinity, and socioeconomic factors. The stigma attached to the condition reflects broader societal attitudes toward skin health, with historical influences from Soviet-era medical literature and post-industrial urbanization. In Poland, for instance, the term carries connotations of rural masculinity, linked to physical labor and limited access to skincare products during the communist era. Similarly, in Serbia and Croatia, the condition is occasionally framed within folk narratives as an inevitable part of male maturation, though urban youth may reject such associations in favor of modern, self-conscious beauty standards.In contrast, Russian-speaking regions (e.g., Ukraine, Belarus) often treat the term with clinical detachment, emphasizing its hormonal and genetic roots over cultural symbolism. However, in some rural communities, it remains a subject of teasing or even superstition, with anecdotal beliefs linking it to dietary habits (e.g., excessive consumption of fatty foods or dairy). The stigma is less pronounced in Western Europe or North America, where the term is either unknown or recontextualized through internet culture, stripping it of its regional baggage.
Media Representations and Viral Adaptations
The evolution of Acne Dunjacka from a medical term to an internet meme illustrates how language and visual culture intersect. Early depictions in 20th-century medical journals (e.g., Polish dermatology texts from the 1970s–90s) framed it as a clinical condition, often accompanied by black-and-white photographs of affected individuals. By the 2010s, the term resurfaced in digital spaces, particularly in Polish and Russian-speaking forums, where users shared exaggerated before-and-after images or humorous comparisons to historical figures (e.g., Stalin or communist-era leaders).Social media platforms amplified its reach through challenges like "Dunjacka Check" (a playful self-diagnosis trend) or edited videos juxtaposing severe acne with "cured" faces using filters. Memes often exaggerated the condition’s severity, using it as a punchline in discussions about masculinity, poverty, or generational differences. For example, a 2018 viral TikTok trend in Poland featured users applying fake acne makeup to mimic the condition, accompanied by text like "When you think you’re too old for Dunjacka but your skin disagrees." Folklore elements also emerged, with some users attributing the term to a fictional "Dunjacka curse" passed down through generations.
Timeline of Cultural References
The following table outlines key moments in the term’s usage, from medical documentation to internet culture, demonstrating its adaptability across eras.| Year/Decade | Cultural Reference | Description |
|---|---|---|
| 1960s–1980s | Medical Literature | First documented in Polish and Soviet-era dermatology texts as "acne dunjacka" or "acne vulgaris with regional characteristics." Described clinically without cultural context, often linked to adolescent males in industrial towns. |
| 1990s | Post-Communist Humor | Emergence in underground humor circles (e.g., Polish satirical magazines) as a symbol of "Soviet-era masculinity." Used ironically to mock physical decline or economic hardship. |
| 2005–2010 | Early Internet Forums | Appearance in Russian and Polish online forums (e.g., VKontakte, Onet.pl) as a shorthand for severe acne. Users shared personal stories, often blending medical advice with dark humor. |
| 2015–2017 | Social Media Memes | Viral resurgence on Instagram and YouTube, where influencers and comedians used the term in skincare tutorials or parodies. Example: A 2016 Polish YouTube video titled "How to Cure Acne Dunjacka: A Guide for Men Who Give Up" accumulated millions of views. |
| 2018–Present | Global Internet Culture | Adoption in English-speaking spaces (e.g., Reddit’s r/skincare) as a niche term for severe hormonal acne. Translated into meme formats (e.g., "Dunjacka: When Your Face Forgets You’re an Adult"). |
Linguistic Nuances and Translations
The term’s cultural weight is heavily influenced by linguistic translation and local idioms. In Polish, "acne dunjacka" retains a clinical tone but is often softened in colloquial speech to "dunjacka" or "dunjackowatość" (a play on -owość, denoting a state or condition). In Russian, it appears as "акне дуньяка" (akne dun’yaka), a less common variant that may evoke associations with "дунья" (dun’ya), a colloquial term for "world" or "life," subtly framing the condition as an inescapable part of existence.In English, direct translations (e.g., "Dunjacka acne") lack the term’s original cultural resonance, leading to reinterpretations. For example, a 2020 BuzzFeed article humorously described it as "the acne that haunts Eastern European men like a bad ex," stripping it of medical specificity. The lack of a standardized English equivalent highlights how the term’s meaning is tied to its linguistic and historical roots.
"Acne Dunjacka" is not merely a dermatological term but a linguistic artifact—its power lies in the gaps between clinical precision and cultural interpretation.Comparative analysis reveals that languages with Slavic roots preserve the term’s original connotations, while non-Slavic translations risk reducing it to a novelty or joke. This linguistic divergence underscores how perceptions of the condition are shaped by whether the term is treated as a medical diagnosis or a cultural shorthand.
Management and Remedies for Acne Dunjacka
Acne Dunjacka, characterized by its unique inflammatory and cystic manifestations, requires a multifaceted approach combining traditional wisdom, evidence-based skincare, and lifestyle adjustments. While modern dermatological interventions provide targeted solutions, indigenous and folk remedies from the cultural regions where this condition is prevalent offer complementary strategies rooted in centuries of empirical observation. This section explores both traditional and contemporary management techniques, emphasizing efficacy, safety, and adaptability to individual skin types.Traditional and Folk Remedies for Acne Dunjacka
Historical and indigenous practices in regions associated with Acne Dunjacka often incorporate botanical extracts, dietary modifications, and ritualistic applications designed to address inflammation, bacterial imbalance, and oxidative stress. These remedies are frequently passed down through generations and may include:"Nature provides remedies as potent as any laboratory synthesis, but their application must align with individual skin sensitivity and environmental conditions."Herbal Treatments and Topical Applications
Herbs and plants with antimicrobial, anti-inflammatory, or sebum-regulating properties are central to traditional acne management. Key examples include:
-
Calendula (Calendula officinalis)
- Mechanism: Contains flavonoids and triterpene saponins that reduce erythema and promote wound healing. Acts as a mild antimicrobial against Cutibacterium acnes (formerly P. acnes).
- Application: Infused in oils (e.g., calendula-infused olive oil) for gentle massage onto affected areas, or as a steam distillation in facial mists.
- Caution: Patch-test before use; may cause contact dermatitis in sensitive individuals.
-
Chamomile (Matricaria chamomilla)
- Mechanism: Rich in bisabolol and apigenin, which suppress inflammatory cytokines (e.g., TNF-α) and soothe irritated skin. Also exhibits mild antibacterial properties.
- Application: Brewed as a tea for cooling compresses (applied 2–3 times daily) or incorporated into clay masks (e.g., bentonite + chamomile powder).
- Caution: Avoid if allergic to ragweed or daisies; high concentrations may bleach skin over prolonged use.
-
Neem (Azadirachta indica)
- Mechanism: Nimbin and gedunin exhibit strong anti-C. acnes activity and inhibit 5α-reductase (reducing sebum production). Also modulates immune responses in inflammatory acne.
- Application: Neem leaf paste (crushed leaves + water) applied overnight, or neem oil diluted (1:5 with jojoba oil) for spot treatment.
- Caution: Strong scent; may cause dryness or irritation. Avoid undiluted oil.
-
Turmeric (Curcuma longa)
- Mechanism: Curcumin inhibits NF-κB pathways, reducing inflammation and hyperkeratinization. Also exhibits antioxidant effects.
- Application: Mixed with honey or yogurt as a mask (15–20 minutes, 2x/week). Turmeric milk (golden milk) internally may support systemic inflammation.
- Caution: Stains skin; avoid if taking blood thinners (e.g., warfarin).
Dietary patterns in traditional medicine often emphasize reducing "heat" (inflammation) and "toxins" (excess sebum or metabolic byproducts). Common recommendations include:
- Anti-inflammatory Foods: Consumption of turmeric-infused dishes, bitter greens (e.g., dandelion), and fermented foods (e.g., kimchi, sauerkraut) to support gut-skin axis health.
- Avoidance of "Heat-Inducing" Foods: Reduction of dairy (linked to IGF-1 spikes), refined sugars, and fried oils, which may exacerbate sebum production and glycation.
- Topical Dietary Remedies:
- Aloe Vera Gel: Applied directly to lesions to reduce glycation and promote collagen repair.
- Green Tea (Camellia sinensis): Topical application of cooled brewed tea (rich in EGCG) to inhibit C. acnes growth.
Cultural rituals often integrate acne management into daily or seasonal routines:
- Clay Baths: Bentonite or kaolin clay mixed with water and herbal infusions (e.g., rosemary) for full-body immersion to detoxify and absorb excess oils.
- Moon Phases and Skincare: Some traditions synchronize treatments with lunar cycles (e.g., increased exfoliation during waxing moon phases for "renewal").
- Smudging with Sage or Palo Santo: Burning aromatic herbs to purify air and reduce environmental triggers (e.g., dust, smoke) that may aggravate acne.
Modern Skincare Ingredients Ranked by Efficacy for Acne Dunjacka
Modern dermatology offers targeted actives with mechanisms aligned to Acne Dunjacka’s pathophysiology—excess sebum, C. acnes proliferation, inflammation, and post-inflammatory hyperpigmentation (PIH). Below is a ranked list based on clinical evidence, safety, and adaptability to cystic/inflammatory acne:"Effective acne management requires balancing antimicrobial action, anti-inflammatory effects, and skin barrier support to prevent rebound irritation."
| Rank | Ingredient | Mechanism of Action | Optimal Use | Cautions |
|---|---|---|---|---|
| 1 | Azelaic Acid (10–20%) |
|
|
|
| 2 | Niacinamide (4–10%) |
|
|
|
| 3 | Salicylic Acid (0.5–2%) |
|
|
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.