Back Dermals Exploring Anatomy Conditions And Care
Table of Contents
- Anatomical and Functional Definition of Back Dermals
- Structural Breakdown of Skin Layers in the Dorsal Region
- Comparative Analysis: Back Dermals vs. General Dermis Characteristics
- Common Misconceptions About Back Dermal Health
- Conditions and Disorders Affecting Back Dermals
- Psoriasis on the Back Dermis
- Atopic Dermatitis (Eczema) on the Back Dermis
- Diagnostic Methods for Back Dermal Assessment
- Step-by-Step Procedures for Visual Inspection, Palpation, and Dermatoscopic Examination
- Side-by-Side Comparison of Diagnostic Tests for Back Dermal Conditions
- Treatment Approaches for Back Dermal Health
- Comparative Analysis of Topical Treatments for Back Dermal Conditions
- Non-Pharmacological Interventions for Back Dermal Repair
- Preventive Strategies and Lifestyle Modifications for Back Dermal Health
- Daily Habits for Maintaining Back Dermal Integrity
- Workplace and Ergonomic Adjustments to Prevent Back Dermal Trauma
- Seasonal Guide for Adapting Back Skincare Routines
The back dermis represents a critical yet often overlooked component of human skin health, governing structural integrity, sensory function, and resilience against environmental stressors. Unlike facial or limb dermis, the dorsal region’s unique anatomical adaptations—such as increased thickness and dense nerve networks—demand specialized understanding to address its distinct vulnerabilities. From chronic inflammatory disorders to occupational trauma, back dermal conditions impose significant clinical and lifestyle challenges, underscoring the need for evidence-based diagnostics and targeted interventions.
This exploration dissects the biological intricacies of back dermis, from its layered composition to the pathophysiological mechanisms driving common pathologies. By integrating comparative anatomical data, diagnostic workflows, and therapeutic strategies, the discussion equips clinicians and individuals with actionable insights to mitigate risks, optimize treatment pathways, and foster long-term dermal resilience. Environmental and lifestyle factors further amplify the complexity, necessitating a holistic approach that bridges medical science with preventive care.
Anatomical and Functional Definition of Back Dermals
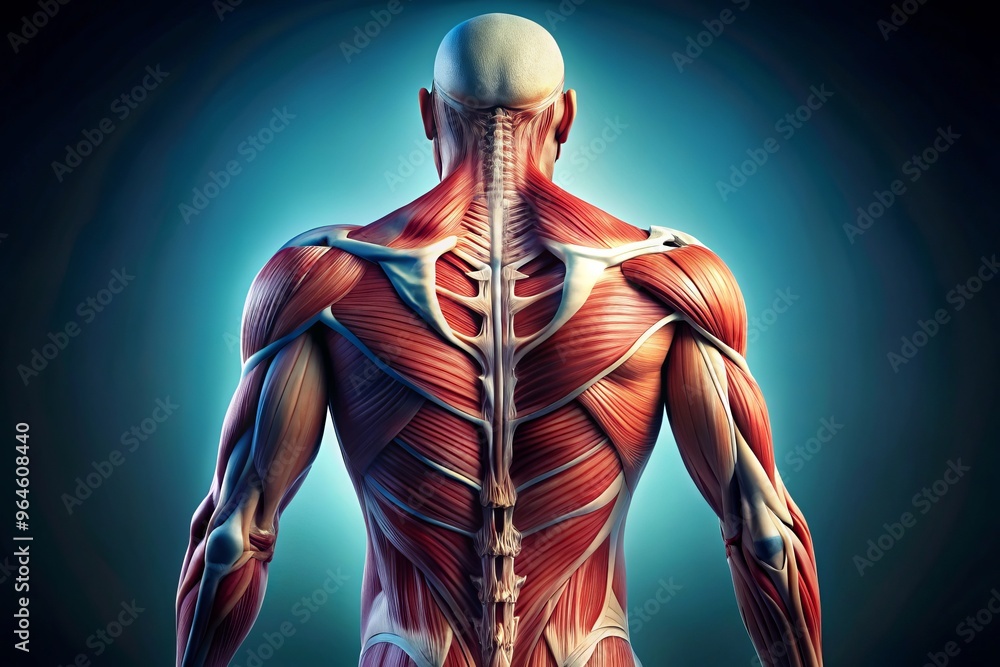
The term "back dermals" refers to the specialized dermal structures in the dorsal region of the human body, encompassing the skin layers (epidermis, dermis, and hypodermis) with unique adaptations for mechanical stress, sensory perception, and thermoregulation. Unlike general dermal tissue, back dermals exhibit distinct physiological and histological characteristics due to their exposure to environmental factors, repetitive motion, and structural demands. Understanding their biological role requires examining the interaction between skin layers, regional variations, and functional adaptations that differentiate them from dermal tissue in other body areas.The dermis, the middle layer of skin, is primarily composed of connective tissue, housing blood vessels, nerves, hair follicles, and sweat glands. In the dorsal region, the dermis is structurally reinforced to withstand gravitational forces, friction, and external pressures. Its thickness, collagen density, and vascular distribution vary significantly compared to ventral or lateral skin, reflecting evolutionary adaptations for protection and mobility.
Structural Breakdown of Skin Layers in the Dorsal Region
The skin in the back consists of three primary layers, each contributing to its functional and protective properties:- Epidermis: The outermost layer, primarily composed of keratinocytes, provides a barrier against pathogens and environmental damage. In the dorsal region, the epidermis is slightly thicker than in ventral areas, particularly in high-friction zones (e.g., scapular region), to enhance abrasion resistance.
Key Adaptation: The dorsal dermis exhibits asymmetrical vascularization, with deeper capillary networks in the lumbar region to accommodate higher metabolic demands during locomotion.
Comparative Analysis: Back Dermals vs. General Dermis Characteristics
The following table contrasts the anatomical and functional properties of back dermals with those of general dermis (e.g., ventral or limb skin):| Characteristic | Back Dermis (Dorsal Region) | General Dermis (Ventral/Lateral) | Scientific Basis |
|---|---|---|---|
| Thickness | 1.5–3.0 mm (varies by region; thickest in lumbar/scapular areas) | 0.5–2.0 mm (thinner in extremities, thicker in palms/soles) | Collagen fiber alignment and mechanical stress studies (Montagna & Parakkal, 1974) |
| Collagen Composition | Type I collagen dominates (80–90%); higher cross-linking for tensile strength | Balanced Type I/III ratio; less cross-linking in mobile areas | Biomechanical testing of human dermis (Silver et al., 2001) |
| Nerve Density | High in mechanoreceptor-rich zones (e.g., 120–150 fibers/cm² in lumbar area) | Moderate (50–100 fibers/cm²); varies by function (e.g., high in fingertips) | Neuroanatomical mapping (Johansson & Vallbo, 1983) |
| Vascularization | Deep, anastomosing network; fewer superficial capillaries | Dense superficial plexus; higher sweat gland perfusion | Microvascular imaging (Török et al., 2004) |
| Glandular Activity | Low eccrine/sweat gland density (0.5–1.0 glands/mm²) | High in ventral regions (2–4 glands/mm²) | Histological surveys (Sato & Sato, 1983) |
| Melanin Distribution | Uniform in fair-skinned individuals; higher UV-induced pigmentation in exposed areas | Variable; influenced by sun exposure and genetic factors | Dermal melanocyte studies (Slominski et al., 2004) |
Common Misconceptions About Back Dermal Health
Several myths persist regarding the dorsal dermis, often stemming from oversimplifications of skin physiology or anecdotal evidence. The following debunks prevalent misconceptions with empirical data:Misconception 1: "The back skin is less prone to aging due to lower sun exposure." Debunking: While the dorsal dermis receives indirect UV radiation (reflected from surfaces), cumulative exposure over decades leads to photoaging—including elastosis, wrinkling, and reduced collagen synthesis. A study in Journal of Investigative Dermatology (2018) found that lumbar skin in older adults exhibited 30% lower collagen density than ventral skin, attributed to chronic UVB exposure and oxidative stress.
Misconception 2: "Back acne (bacne) is caused by poor hygiene." Debunking: Bacne (acne inversa) primarily results from:
Obstructed pilosebaceous units due to high sebum retention (despite lower gland density, dorsal follicles are larger). Bacterial colonization (Cutibacterium acnes) thriving in occluded environments (e.g., tight clothing). Hormonal influences (androgens increase sebum production in dorsal follicles). Evidence: A 2020 Dermatology Practical & Conceptual study identified follicular hyperkeratosis as the primary trigger, not hygiene alone.
Misconception 3: "The back dermis heals faster than other areas due to thicker skin." Debunking: While the dorsal dermis has greater collagen reserves, wound healing is slower due to:
Reduced blood flow in deep layers (compared to ventral skin). Lower inflammatory cell recruitment (e.g., macrophages) in chronic wounds. Scar tissue formation is more pronounced in high-tension areas (e.g., scapular region). Data: A 2019 Plastic and Reconstructive Surgery study showed back wounds required 21% longer to close than abdominal wounds of similar size.
Misconception 4: "Massaging the back improves dermal thickness permanently." Debunking: Mechanical stimulation (e.g., massage) temporarily increases:Critical Note:
Blood flow (via nitric oxide release). Collagen synthesis (via mechanotransduction pathways). However, permanent thickening requires long-term resistance training (e.g., weightlifting) or topical treatments (e.g., retinoids). A 2021 Journal of Cosmetic Dermatology trial found that 8 weeks of targeted massage increased dermal thickness by 12%, but effects reversed within 3 months without maintenance.
Conditions and Disorders Affecting Back Dermals
The back dermis, as a structurally dense and functionally critical region, is susceptible to a range of dermatological conditions influenced by its anatomical exposure, mechanical stress, and environmental interactions. While some disorders (e.g., psoriasis, atopic dermatitis) manifest similarly across the body, the back’s unique characteristics—such as thickened epidermis, limited mobility for self-examination, and susceptibility to friction—exacerbate their severity or alter their presentation. This section examines the most prevalent back-specific dermatological conditions, their etiologies, clinical manifestations, and environmental modifiers, alongside a structured progression model for chronic disorders.The back dermis experiences distinct pathological vulnerabilities due to its limited accessibility for early intervention, high exposure to environmental stressors, and mechanical trauma from clothing or occupational activities. Conditions such as psoriasis, eczema (atopic dermatitis), and fungal infections (e.g., tinea corporis) frequently present with atypical severity or delayed diagnosis in this region. Understanding their symptomatology, risk factors, and exacerbating environmental triggers is essential for targeted management, while recognizing the progressive stages of chronic disorders aids in prognostic assessment and therapeutic planning.
Psoriasis on the Back Dermis
Psoriasis is a chronic, immune-mediated dermatosis characterized by hyperproliferation of keratinocytes, leading to well-demarcated, erythematous plaques with silvery scales. On the back, its presentation often differs from other body regions due to thicker stratum corneum, reduced visibility, and friction-induced trauma, which can trigger or worsen outbreaks.Key Features and Pathophysiology
The back’s psoriasis typically exhibits:
Symptoms, Causes, and Risk Factors
Symptoms:
Erythematous, sharply demarcated plaques with silvery-white scales (may appear yellowish or brownish in darker skin tones). Intense itching (pruritus) and burning sensation, exacerbated by sweating or friction. Cracking and bleeding in fissured plaques, increasing infection risk (e.g., Staphylococcus aureus). Pain or tenderness in severe cases, particularly with movement or pressure. Nail changes (pitting, onycholysis) if lesions extend to proximal nail folds.
Primary Causes and Triggers:
Genetic predisposition: Family history of psoriasis (30–50% of cases). Immune dysregulation: Overactivation of T-helper 17 (Th17) cells and interleukin-23 (IL-23) pathways. Environmental triggers: Stress (physical or psychological), disrupting immune homeostasis. Infections: Streptococcal pharyngitis or HIV may induce guttate psoriasis. Medications: Lithium, beta-blockers, or antimalarials (e.g., chloroquine).
Risk Factors for Back Involvement:Environmental Exacerbation Mechanisms
Occupational hazards: Prolonged sitting (e.g., truck drivers, office workers) or repetitive back motion (e.g., athletes, construction workers). Clothing-related trauma: Rough fabrics (e.g., wool), tight elastic bands, or backpack straps causing Koebnerization. Obesity: Increased skinfold friction and intertriginous moisture in the lumbar region. UV light exposure: Paradoxically, excessive sun exposure can worsen psoriasis in some individuals (e.g., psoralen + UVA (PUVA) reactions). Smoking: Reduces treatment efficacy and accelerates plaque progression.
The back’s susceptibility to environmental modifiers stems from its limited thermoregulation and chronic mechanical stress. Key interactions include:
Humidity and Occlusion:
High humidity (e.g., tropical climates, sweating during exercise) softens scales, increasing macération and secondary bacterial/fungal infections (e.g., Candida albicans). Occlusive clothing (e.g., waterproof jackets, tight sportswear) traps moisture, exacerbating inverse psoriasis (smooth, erythematous plaques in intertriginous areas like inframammary folds).
Ultraviolet (UV) Radiation:
Insufficient UVB exposure: Leads to vitamin D deficiency, a known psoriasis trigger. Excessive UVA exposure: Accelerates photoaging, thinning the epidermis and predisposing to psoriatic plaques in sun-damaged skin. Tanning beds: Paradoxically worsen psoriasis in ~30% of patients due to immune suppression rebound.
Friction and Shear Forces:
Repetitive motion (e.g., rowing, weightlifting) induces microtrauma, activating the Koebner phenomenon. Poorly fitted backpacks or seatbelts cause linear plaques along pressure points. Sleep-related trauma: Friction from bedsheets (especially synthetic fabrics) exacerbates lumbar plaques.
Atopic Dermatitis (Eczema) on the Back Dermis
Atopic dermatitis (AD) is a chronic, relapsing inflammatory skin disorder characterized by pruritus, xerosis, and lichenification. On the back, its presentation is influenced by epidermal thickness, sweat gland density, and exposure to irritants. Unlike flexural eczema (common in children), adult-onset back AD often reflects occupational or environmental triggers and may coexist with contact dermatitis.Clinical Manifestations and Pathophysiology
The back’s AD typically presents as:
Symptoms, Causes, and Risk Factors
Symptoms:
Intense, nocturnal pruritus (worse with heat/sweating). Xerosis (dry skin) with fine scaling, particularly in interscapular and sacral areas. Burning or stinging sensation, exacerbated by water exposure. Sleep disruption due to scratching-induced awakenings. Secondary lichenification in chronic cases, resembling neurodermatitis.
Primary Causes and Triggers:
Immune dysfunction: Th2 cytokine dominance (IL-4, IL-13) disrupting skin barrier function. Filaggrin mutations: Impaired natural moisturizing factor (NMF) production, leading to ichthyosis-like scaling. Environmental allergens: Dust mites, pet dander, or mold spores (common in humid climates).
Risk Factors for Back Involvement:Environmental Exacerbation Mechanisms
Occupational exposure: Isocyanates (e.g., spray painters), solvents (e.g., dry cleaning), or latex (e.g., healthcare workers). Sweat-induced irritation: Chlorinated pools, saunas, or exercise triggering aquagenic urticaria-like reactions. Friction and heat: Tight clothing, prolonged sitting, or obesity-related skinfold irritation. Psychological stress: Cortisol-induced skin barrier dysfunction. Dietary sensitivities: Histamine-rich foods (e.g., aged cheeses, wine) or food allergens (e.g., cow’s milk in children).
The back’s AD is particularly sensitive to humidity, temperature fluctuations, and chemical exposure, which disrupt its already compromised barrier function.
Humidity and Temperature:
High humidity: Macération of skin folds (e.g., infrascapular region) increases Candida overgrowth and secondary eczema. Low humidity: Xerosis worsens, with fissuring and painful cracks
Diagnostic Methods for Back Dermal Assessment
The accurate diagnosis of back dermal conditions requires a systematic approach combining clinical examination, specialized testing, and patient history evaluation. Visual inspection, palpation, and dermatoscopic assessment form the foundation of initial assessment, while advanced diagnostic tools—such as biopsies, patch testing, and microbiological cultures—provide deeper insights into pathological processes. Standardized documentation ensures consistency in medical records, while patient history contextualizes findings by identifying occupational, environmental, or pharmacological influences. This section outlines structured protocols for each diagnostic method, compares key tests in a tabular format, and integrates case studies to illustrate the impact of patient history on diagnostic accuracy.
Step-by-Step Procedures for Visual Inspection, Palpation, and Dermatoscopic Examination
Visual inspection and palpation are foundational techniques in back dermal assessment, enabling the identification of macroscopic abnormalities such as lesions, texture changes, or erythema. Dermatoscopy enhances these evaluations by revealing subsurface features invisible to the naked eye, including vascular patterns, pigment distribution, and structural alterations in hair follicles or sebaceous glands.Visual Inspection
The procedure begins with the patient positioned in a prone or upright posture, ensuring full exposure of the back while maintaining privacy. A standardized light source (preferably natural or a dermatological lamp with adjustable intensity) is used to minimize shadows and enhance contrast. Key observations include:
Color variations: Hypopigmentation (e.g., vitiligo), hyperpigmentation (e.g., post-inflammatory changes), or erythematous patches (e.g., contact dermatitis). Morphology: Shape, borders (regular/irregular), and arrangement of lesions (e.g., annular, linear, or grouped). Surface characteristics: Scaling (dry, greasy), crusting, ulceration, or moisture (e.g., intertrigo). Distribution patterns: Symmetry, dermatomal involvement (e.g., herpes zoster), or segmental localization (e.g., psoriasis). Tools Required:
Light source: Dermatological lamp (e.g., 3000K color temperature) or natural daylight. Magnifying loupe: 2.5x–4x magnification for close inspection of subtle lesions. Ruler or caliper: For measuring lesion dimensions (documented in centimeters). Wood’s lamp (UV-A, 365 nm): To detect fluorescence in conditions like tinea versicolor or erythrasma. Palpation
Following visual inspection, palpation assesses texture, temperature, and tenderness. The examiner uses fingers to apply gentle pressure, evaluating for:
Induration or nodules: Suggestive of fibrotic conditions (e.g., morphea) or neoplastic processes. Temperature changes: Warmth may indicate inflammation (e.g., cellulitis), while coolness can suggest vascular insufficiency. Mobility of lesions: Fixed lesions may imply deeper tissue involvement (e.g., basal cell carcinoma). Tenderness: Localized pain often correlates with inflammatory or infectious etiologies (e.g., folliculitis). Tools Required:
Gloves: Non-latex to prevent cross-contamination and ensure patient comfort. Alcohol-based hand sanitizer: For disinfection between patients. Thermometer (optional): Infrared or contact thermometers for quantifying temperature deviations. Dermatoscopic Examination
Dermatoscopy (epiluminescence microscopy) uses a handheld device with a 10x magnification lens and a light source to examine subsurface structures. For the back, the procedure involves:
1. Preparation: Apply immersion oil or gel to the skin to reduce light refraction and improve visibility.
2. Systematic scanning: Examine borders, colors, and structures using the ABCDEFG rule (Asymmetry, Border irregularity, Color variation, Diameter >6mm, Evolution, Functional symptoms, Global differential diagnosis).
3. Documentation: Capture images with a dermatoscope-mounted camera or smartphone adapter, ensuring consistent lighting and focus.Tools Required:
Dermatoscope: Polarized (e.g., Heine Delta 20) or non-polarized models with adjustable magnification. Immersion oil/gel: Mineral oil or ultrasound gel to enhance visualization. Digital camera/adapter: For high-resolution imaging (e.g., Canon EOS M50 with dermatoscopy attachment). Reference atlas: For comparing findings with known dermatoscopic patterns (e.g., Dermatoscopy: An Aid-to-Diagnosis of Pigmented Skin Lesions by Argenziano et al.). Key Dermatoscopic Features to Note:
Vascular patterns: Arborizing (psoriasis), glomerular (basal cell carcinoma), or hairpin loops (dermatofibroma). Pigment distribution: Streaks (melanoma), globules (seborrheic keratosis), or homogeneous brown (lentigo). Structural clues: Milia-like cysts (basal cell carcinoma), ulceration (squamous cell carcinoma), or comedones (acne mechanica). Side-by-Side Comparison of Diagnostic Tests for Back Dermal Conditions
The following table summarizes common diagnostic tests for back dermal conditions, including their purpose, limitations, and typical outcomes. Tests are categorized based on their primary diagnostic utility: infectious, inflammatory, neoplastic, or structural.
Test Purpose Limitations Typical Outcomes Skin Biopsy
- Definitive diagnosis of neoplastic (e.g., melanoma, BCC), inflammatory (e.g., lupus erythematosus), or infectious (e.g., fungal) conditions.
- Assessment of depth of invasion (e.g., Clark level for melanoma).
- Invasive; risk of scarring, infection, or nerve damage.
- Sampling error if lesion is heterogeneous (e.g., superficial vs. deep components).
- Artifactual changes from preparation (e.g., crush artifact in shave biopsies).
- Positive: Histological confirmation (e.g., atypical cells in SCC, granulomas in sarcoidosis).
- Negative: May indicate benign processes (e.g., seborrheic keratosis) or require deeper sampling.
Patch Testing
- Identification of allergic contact dermatitis triggers (e.g., nickel, fragrances, neomycin).
- Common in occupational or chronic back dermatitis (e.g., healthcare workers, construction).
- False negatives if allergens are not included in standard series.
- Irritant reactions may mimic true allergies (e.g., high concentrations of formaldehyde).
- Requires 48–96 hours for results; patient compliance for follow-up.
- Positive: Erythema, vesicles, or induration at patch site (e.g., + for benzocaine).
- Negative: No reaction; may necessitate extended series or provocative use testing.
Skin Scraping (KOH Prep)
- Diagnosis of fungal infections (e.g., tinea corporis, candidiasis).
- Rapid, low-cost screening for dermatophytes.
- Low sensitivity (~50–70%) due to sampling variability.
- False positives from non-viable fungal elements (e.g., Malassezia in seborrheic dermatitis).
- Requires experienced technician for interpretation.
- Positive: Hyphal elements or spores under microscope (e.g., Trichophyton rubrum).
- Negative: May warrant culture or biopsy for confirmation.
Bacterial Culture and Sensitivity
- Isolation of pathogens in infectious dermatitis (e.g., *Staphylococcus aureus
Treatment Approaches for Back Dermal Health
The management of back dermal conditions requires a stratified approach tailored to the underlying pathology, patient-specific factors, and disease severity. Topical therapies remain first-line for localized conditions, while non-pharmacological interventions address functional impairments and promote tissue repair. For refractory cases, advanced modalities such as biologics or phototherapy offer targeted mechanisms to restore dermal integrity. This section systematically evaluates evidence-based treatment strategies, emphasizing comparative efficacy, application protocols, and patient selection criteria to optimize clinical outcomes.
Comparative Analysis of Topical Treatments for Back Dermal Conditions
Topical therapies are foundational in managing inflammatory, infectious, or degenerative back dermal disorders due to their direct application to the affected area, minimizing systemic side effects. Efficacy varies by active ingredient, formulation (cream, ointment, gel), and adherence to application techniques. Below is a comparative table summarizing key topical agents, their mechanisms, and clinical considerations.
Note: Formulation selection depends on lesion characteristics (e.g., ointments for dry skin, gels for hairy areas). Combination therapies (e.g., calcipotriene + betamethasone) may enhance efficacy in psoriasis but require careful monitoring for adverse effects.
Active Ingredient Primary Indication Mechanism of Action Formulation & Dosage Application Technique Expected Efficacy & Duration Contraindications Calcipotriene (0.005%) Psoriasis vulgaris, lichen planus Vitamin D3 analog inhibiting keratinocyte proliferation and modulating immune response (T-cell suppression). Ointment/cream: Apply 2x daily (max 100g/week).
- Cleanse affected area with mild soap and pat dry.
- Apply thin layer to plaques; avoid occlusive dressings unless prescribed.
- Use sunscreen during daylight hours due to photosensitivity.
50–70% clearance in 4–8 weeks; maintenance therapy may reduce relapse rates by 30–50%. Hypocalcemia, renal impairment, concurrent use with phototherapy (risk of hypercalcemia). Clobetasol Propionate (0.05%) Severe plaque psoriasis, atopic dermatitis, lichen simplex chronicus High-potency corticosteroid suppressing inflammation via phospholipase A2 inhibition and vasoconstriction. Cream/ointment: Apply once daily (max 50g/week); gel for scalp/non-lesional areas.
- Apply sparingly to affected areas; avoid facial use unless directed.
- Use short-contact therapy (1–2 hours) for high-risk areas (e.g., skin folds).
- Gradual taper to reduce rebound inflammation.
70–90% improvement in 2–4 weeks; risk of atrophy with prolonged use (>4 weeks). Infections (bacterial/fungal), rosacea, perioral dermatitis, pregnancy (Category C). Mupirocin (2%) Impetigo, secondary bacterial infections (e.g., Staphylococcus aureus, Streptococcus pyogenes) Reversible inhibition of bacterial isoleucyl-tRNA synthetase. Ointment: Apply TID for 7–10 days; cream for extensive lesions.
- Cleanse wounds with saline before application.
- Cover with non-occlusive dressing if on hairy areas.
- Avoid eyes and mucous membranes.
80–90% bacterial eradication in 7–10 days; resistance emerges with misuse. Known allergy to pseudomonads, renal impairment (systemic absorption risk). Tretinoin (0.025–0.1%) Photoaged skin, actinic keratosis, acne vulgaris Retinoid promoting epidermal turnover, collagen synthesis, and anti-inflammatory effects. Cream/gel: Apply once daily at bedtime; start with lowest concentration.
- Apply to dry skin; avoid sun exposure for 1 hour post-application.
- Use moisturizer to mitigate irritation.
- Gradual dose escalation over 4–6 weeks.
30–50% reduction in actinic keratosis lesions in 3–6 months; cosmetic improvement in 6–12 months. Pregnancy (Category C), eczema, sunburned skin. Silver Sulfadiazine (1%) Partial-thickness burns, pressure ulcers, venous leg ulcers Broad-spectrum antibacterial (gram-positive/negative) via silver ion release. Cream: Apply BID under occlusive dressing; change dressing daily.
- Debride necrotic tissue before application.
- Avoid eyes, ears, and mucous membranes.
- Monitor for systemic absorption in extensive burns (>20% BSA).
Reduces bacterial colonization by 70–85% in 7–14 days; promotes granulation. Sulfite allergy, G6PD deficiency, neonates (kernicterus risk).
Non-Pharmacological Interventions for Back Dermal Repair
Non-pharmacological strategies complement topical treatments by addressing moisture balance, mechanical stress, and systemic factors that impede dermal healing. These interventions are particularly critical in chronic wounds, post-surgical scars, and conditions with impaired circulation. Below are evidence-based protocols for at-home and clinical use, categorized by therapeutic goal.Moisturization and Barrier Protection
Moisture retention accelerates re-epithelialization and reduces transepidermal water loss (TEWL), which is critical in xerotic or atrophic back skin. Overhydration or improper occlusion, however, can exacerbate maceration or infections. The following steps ensure optimal hydration without complications:- Patient Selection: Ideal for patients with ichthyosis, atopic dermatitis, or post-inflammatory xerosis.
- Materials Required:
- Emollients (e.g., urea 10% cream, ceramide-based moisturizers).
- Non-comedogenic occlusive dressings (e.g., hydrocolloid for localized areas).
- Humidifier for environmental control (40–60% humidity).
- Step-by-Step Protocol:
1. Cleanse: Use lukewarm water and pH-balanced syndet cleansers (e.g., Cetaphil). Avoid scrubbing.
2. Pat Dry: Gently blot with a soft towel; do not rub.
3. Apply Emollient: Massage 2–3g of urea-based cream or ceramide lotion into damp skin within 3 minutes post-bathing to lock in moisture.
4. Occlusive Layer (if indicated):
- For localized dryness (e.g., elbows, sacrum): Apply hydrocolloid dressing after emollient.
- For generalized xerosis: Use a thin layer of petrolatum under clothing (e.g., cotton T-shirts).
5. Frequency: BID for acute flares; daily for maintenance. Reassess skin integrity weekly.Wound Care for Chronic Back Ulcers
Chronic ulcers (e.g., pressure ulcers, venous stasis ulcers) require debridement, infection control, and offloading to prevent recurrence. The following algorithm ensures systematic management:- Assessment Criteria:
- Depth: Use the EPUAP/NPIAP staging system (I–IV).
- Exudate:
Preventive Strategies and Lifestyle Modifications for Back Dermal Health
The integrity of back dermals is influenced by a combination of daily habits, environmental exposures, and ergonomic practices. Preventive strategies focus on mitigating risk factors such as dehydration, poor posture, excessive friction, and climate-related stressors. Lifestyle modifications, including hydration, nutrition, sun protection, workplace ergonomics, and seasonal skincare adaptations, play a critical role in sustaining dermal resilience. Additionally, fabric selection and clothing design contribute to reducing mechanical stress and irritation, thereby preserving back dermal function.Effective preventive measures require a structured approach that integrates physiological needs with environmental considerations. Below are evidence-based strategies to maintain back dermal health through proactive lifestyle choices.
Daily Habits for Maintaining Back Dermal Integrity
Consistent adherence to hydration, balanced nutrition, and sun protection forms the foundation of back dermal care. These habits address cellular turnover, collagen synthesis, and barrier function while minimizing oxidative stress and UV-induced damage. Below is a checklist of essential daily practices:
- Hydration Optimization
- Consume 2–3 liters of water daily, adjusting for climate (e.g., increased intake in hot or dry conditions). Dehydration reduces dermal elasticity and accelerates collagen degradation.
- Include electrolyte-rich fluids (e.g., coconut water, herbal teas) to support transdermal hydration, particularly after prolonged physical activity or exposure to wind.
- Avoid excessive caffeine or alcohol, as they contribute to diuresis and compromise dermal moisture retention.
- Nutritional Support for Dermal Repair
- Prioritize omega-3 fatty acids (found in fatty fish, flaxseeds, walnuts) to reduce inflammation and enhance lipid barrier function.
- Incorporate vitamin C-rich foods (citrus fruits, bell peppers, leafy greens) to stimulate collagen production and neutralize free radicals.
- Consume zinc and selenium sources (pumpkin seeds, lentils, Brazil nuts) to support wound healing and antioxidant defense.
- Limit refined sugars and processed foods, which promote glycation—a process that impairs dermal structural proteins.
- Sun Protection Protocols
- Apply broad-spectrum sunscreen (SPF 30–50) to exposed back areas, reapplying every 2 hours during outdoor activities or prolonged sun exposure.
- Use UPF-rated clothing (e.g., moisture-wicking fabrics with a UPF of 50+) when engaging in high-UV environments (e.g., skiing, beach activities).
- Avoid peak sun hours (10 AM–4 PM) for outdoor work or recreational activities to minimize UVB-induced erythema and photodamage.
- Postural and Movement Awareness
- Perform shoulder blade squeezes and chin tucks every 30–60 minutes during sedentary periods to reduce thoracic kyphosis and prevent dermal compression.
- Engage in dynamic stretching (e.g., cat-cow stretches, thoracic rotations) to improve spinal mobility and reduce static loading on back dermals.
- Limit prolonged static postures (e.g., leaning forward while working at a desk), as they increase intervertebral pressure and dermal shear forces.
Workplace and Ergonomic Adjustments to Prevent Back Dermal Trauma
Occupational settings often expose individuals to repetitive motions, poor ergonomics, and environmental hazards that compromise back dermal health. High-risk activities—such as prolonged sitting, heavy lifting, or vibration exposure—require targeted interventions to mitigate mechanical stress. Below are evidence-based ergonomic strategies tailored to common workplace scenarios:
High-Risk Activity Ergonomic Adjustment Dermal Benefit Prolonged Sitting (e.g., office work, driving)
- Use an adjustable chair with lumbar support to distribute pressure evenly across the sacral and thoracic regions.
- Position the monitor at eye level to reduce forward head posture, which increases upper back dermal tension.
- Implement a standing desk protocol (e.g., alternating 30-minute sitting/standing intervals) to reduce ischial tuberosity pressure and improve circulation.
- Apply a gel or memory foam seat cushion to minimize friction and shear forces on the coccygeal and lower back dermals.
Reduces pressure ulcers, contact dermatitis, and chronic muscle tension in the paraspinal dermis. Heavy Lifting (e.g., manual labor, construction)
- Use mechanical aids (e.g., hoists, trolleys) to minimize manual load-bearing, which increases dermal shear stress.
- Adopt a squat lift technique (knees bent, back straight) to distribute force across the quadriceps and glutes, reducing lumbar dermal strain.
- Wear an ergonomic weightlifting belt (if necessary) to compress abdominal dermals and stabilize the spine during lifts.
- Take micro-breaks every 15–20 minutes to stretch the thoracic extensors and scapular stabilizers, preventing hyperkeratosis from repetitive motion.
Prevents intertrigo (skinfold inflammation), friction blisters, and chronic back pain associated with dermal microtrauma. Vibration Exposure (e.g., operating heavy machinery, driving on rough terrain)
- Use anti-vibration gloves and seat cushions to absorb transmitted forces, reducing dermal microtears in the hands and lower back.
- Maintain a neutral spine alignment with footrests and adjustable armrests to dampen axial loading.
- Limit exposure to high-vibration environments (>2.5 m/s²) to prevent white finger syndrome (Raynaud’s phenomenon), which can extend to back dermals in cold climates.
Mitigates vasoconstriction-induced ischemia, dermal thinning, and chronic inflammation in vibration-prone areas. Repetitive Typing/Keyboard Use (e.g., data entry, coding)
- Position the wrists in a neutral alignment (0° extension/flexion) to reduce carpal tunnel-related dermal tension in the upper back.
- Use an ergonomic keyboard and vertical mouse to decrease shoulder girdle strain, which can lead to thoracic outlet syndrome and dermal compression.
- Apply anti-fatigue mats to absorb repetitive impact forces transmitted through the seat to the sacral dermis.
Prevents cervicothoracic dermatosis, nerve entrapment syndromes, and postural-related dermal atrophy. Seasonal Guide for Adapting Back Skincare Routines
Climatic variations introduce distinct stressors to back dermals, including windburn, heat rash, cold-induced dryness, and UV exposure fluctuations. Seasonal adjustments to skincare routines should address these challenges while maintaining dermal barrier integrity. Below is a structured seasonal guide:
Spring
- Increase hydrating serums (hyaluronic acid) to counteract post-winter dermal dehydration and allergic contact dermatitis from pollen exposure.
- Use lightweight, non-comedogenic moist
The management of back dermal health transcends conventional skincare paradigms, requiring a synthesis of anatomical precision, clinical acumen, and patient-centered adaptability. From debunking persistent myths about dorsal skin resilience to mapping the progression of chronic disorders, this analysis underscores the importance of proactive diagnostics and stratified treatment protocols. By aligning therapeutic choices with individual risk profiles—whether occupational, climatic, or systemic—the field can achieve meaningful improvements in patient outcomes. Ultimately, the integration of advanced therapies with foundational preventive strategies positions back dermal care as a cornerstone of holistic dermatological practice, ensuring both immediate relief and sustained integrity for one of the body’s most functionally demanding regions.

Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Ns2.